• Ouhai, Wenzhou, Zhejiang China
  • 24/7 Service

Top-Tier Hospitals

9000+ Beds Combined

World-Renowned Doctors

Transplant Pioneers

Dedicated Care Team

Satisfied Patients
Call Us : +86 18357823575

Author Archives: Global Meds

Da Vinci robot enables successful kidney sparing surgery with high precision

Da Vinci robot enables successful kidney-sparing surgery with high precision

At 20, most young people are running freely and enjoying their youth. But for Tina (pseudonym), a girl from Bangladesh, the past two decades have been spent living with a rare disease called tuberous sclerosis complex (TSC). In the last three weeks, persistent lumbar and abdominal pain disrupted her peaceful life. Examinations revealed a tumor over 7 cm in diameter in her left kidney, located in a perilous position—clinging to the main renal artery and surrounded by abundant collateral vessels.


Tina and her family sought medical help in several countries, but the answers they received were almost identical: the surgery was extremely difficult and the risks were hard to control. Just as the family was falling into anxiety, they turned their eyes to China. Through a recommendation from a local medical service agency, they learned about the International Medical Center (FIMC) of Foshan Fosun Chancheng Hospital.

Section 1: Understanding the Rare Disease TSC – A Genetic Condition That Can Affect the Kidneys

Tuberous sclerosis complex (TSC) is a genetic rare disease that can affect multiple organ systems, with the kidneys being one of the commonly involved organs. Among its manifestations, TSC‑associated renal angiomyolipoma (TSC‑AML) is a major kidney‑related finding in TSC patients. Although renal angiomyolipomas are mostly benign lesions, it does not mean they can be completely ignored. TSC‑associated AML tends to occur at an earlier age, may be multiple or bilateral, and has abundant blood vessels within the tumor. As the tumor enlarges, the risk of spontaneous bleeding also increases.

Section 2: Treatment Decision – Why Not Simple “Interventional Embolization”?

For TSC‑AML patients, interventional embolization is an optional treatment. However, Tina’s lesion had abundant collateral vessels, and simple embolization might not completely block the blood supply, nor guarantee complete tumor absorption; close follow‑up or even secondary intervention would still be required. Moreover, complete resection of the lesion to obtain a pathological diagnosis is essential for definitive diagnosis. Therefore, the Urology Department team at Foshan Fosun Chancheng Hospital (hereinafter referred to as “Foshan Chancheng Hospital”) set a clear treatment goal: to remove the tumor while preserving the affected kidney to the greatest extent possible. However, this surgery was extremely challenging. Partial nephrectomy (kidney‑sparing surgery) requires temporary clamping of the renal artery, precise tumor excision, and suturing of the wound within a limited time. During the clamping period, the kidney is in a state of “warm ischemia”—the shorter this time, the better the protection of renal function. With Tina’s tumor tightly adhering to the main renal artery and surrounded by rich collateral vessels, even a minor mistake in dissection or suturing could lead to massive bleeding or even force conversion to total nephrectomy.

Section 3: The Da Vinci Robot – Precision on a Millimeter Scale

Facing this highly difficult challenge, the urology team at Foshan Chancheng Hospital conducted a detailed preoperative evaluation and ultimately decided to perform a Da Vinci robot‑assisted partial nephrectomy. The Da Vinci robot is not operated autonomously by the machine; instead, the surgeon controls the robotic arms from a console to perform more refined surgical maneuvers. Its advantages include:

•Sharper vision: 3D high‑definition magnified visualization helps the surgeon clearly identify tumor boundaries, renal vessels, and surrounding critical structures.

•Greater dexterity: The robotic arms have multiple degrees of freedom, mimicking and even surpassing the human wrist’s movements in tight spaces, making it suitable for delicate dissection and suturing at complex angles.

•Enhanced stability: The robotic arms filter out natural hand tremors, ensuring each movement is more precise and steady.


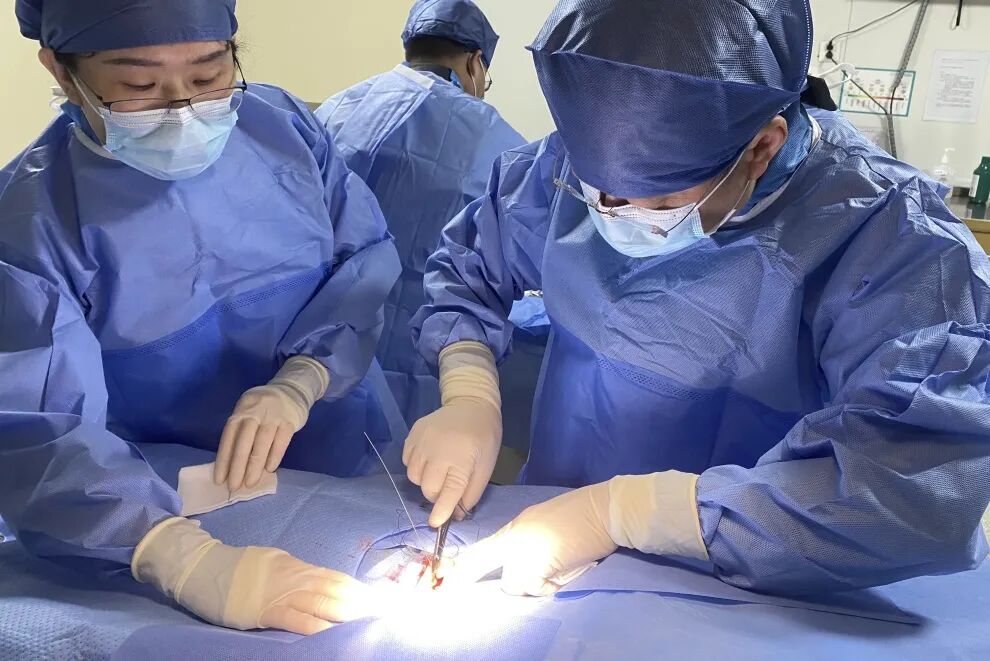
With the assistance of the Da Vinci robot, the team successfully and precisely resected two tumors from Tina, completely preserving her left kidney.

Section 4: “Thank You for Giving Me a Second Life”

On the day of discharge, Tina and her family specially expressed their gratitude to the medical team: “From Dhaka to Foshan, spanning 2,800 kilometers, we thank every doctor and nurse here for giving me a second life.” Her father said with emotion: “The surgery was very successful, and our worries have finally been put to rest. The doctors and nurses treated us like family, with dedicated staff checking on her recovery every day.” Tina’s mother, who felt unwell during the stay, was promptly arranged for an examination through the coordination of FIMC, with quick responses and orderly arrangements. The hospital also arranged diversified meals according to the patient’s cultural customs, making the family feel at home far fr

81-year-old patient with coronary heart disease gets a new lease on life!

81-year-old patient with coronary heart disease gets a new lease on life!

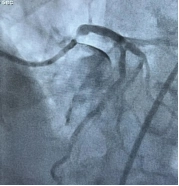
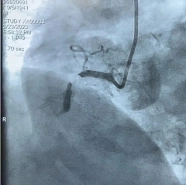
A 81-year-old patient with a history of coronary heart disease for several years was admitted to the Department of Cardiovascular Medicine. Coronary CT performed previously had indicated severe vascular calcification, and the patient had been managed with conservative medical therapy at that time. Two days before presentation, the patient experienced recurrent angina attacks. Electrocardiography showed myocardial ischemia, and myocardial enzymes were elevated. Based on the patient’s typical symptoms and coronary CT findings, the Department of Cardiovascular Medicine diagnosed acute coronary syndrome, and the patient was immediately admitted to the Cardiac Care Unit. On the day of admission, emergency coronary angiography was performed, revealing severe vascular calcification, 95% stenosis at the ostium of the left main coronary artery, and near-total occlusion of the right coronary artery. Considering the clinical history, the culprit vessel was determined to be the right coronary artery. The right coronary artery was opened with the assistance of multiple devices, and one stent was implanted. The chest pain was relieved.

5c714a41a85355abe5224cef92c5e82e6926c490338d2c3e3e080307ddc506dc

Coronary angiography findings: Near-occlusion of the right coronary artery, severe stenosis at the ostium of the left main coronary artery.

After the emergency procedure, the patient no longer experienced chest pain at rest. However, the most important coronary vessel—the left main coronary artery—still had 95% stenosis with severe calcification, raising the question of how to manage it. The Department of Cardiovascular Medicine held a discussion and proposed the following options: 1. Conservative therapy: Since the patient’s symptoms had been relieved, could medical conservative therapy be considered? However, given the severe vascular stenosis and a functional assessment QFR = 0.64 indicating severe ischemia, conservative therapy would carry a high risk of sudden death after discharge. 2. Coronary artery bypass grafting (CABG): The patient had recently suffered myocardial infarction and undergone percutaneous coronary intervention and was currently taking antiplatelet drugs, so surgical intervention would carry a high bleeding risk. In addition, the patient and family considered surgery too invasive and declined CABG. 3. Percutaneous coronary intervention (PCI): The patient had an ostial left main lesion, and intraprocedural risks included hypotension and arrhythmia. Severe vascular calcification might require coronary rotational atherectomy. PCI was recommended to be performed under strong circulatory support. After consultation among the Heart Center, ICU, and Department of Anesthesiology, and after full communication with the patient and family, it was ultimately decided to perform PCI under ECMO (extracorporeal membrane oxygenation) support.

After careful planning, the procedure was performed. The Department of Anesthesiology decided to administer non-intubated general anesthesia to minimize patient discomfort. Two ICU physicians performed arteriovenous catheterization and ECMO initiation. Vascular surgeons assisted in establishing vascular access. Once everything was ready, three physicians from the coronary heart disease team of the Department of Cardiovascular Medicine performed the interventional procedure. The procedure was even more difficult than anticipated. The patient’s left coronary ostium was low, and with concomitant stenosis, multiple types and sizes of guiding catheters could not be properly engaged; ultimately, a JL4 catheter was barely engaged. Intravascular ultrasound (IVUS) revealed severe left main stenosis with nearly 300 degrees of calcification. During balloon pre-dilation, the patient’s blood pressure dropped and severe angina occurred, with blood pressure falling to as low as 60/30 mmHg. At this critical moment, the ECMO team rapidly adjusted ECMO parameters, and the cardiovascular medicine team, after rapid positioning, successfully implanted one stent. The patient’s symptoms gradually resolved, and blood pressure recovered. After multiple balloon post-dilations, intravascular ultrasound confirmed accurate stent positioning and satisfactory expansion. Final angiography showed complete resolution of the left main stenosis. ECMO was successfully weaned after the procedure, and the patient returned safely to the ward.

Procedure: ECMO initiation and percutaneous coronary intervention.

This complex coronary intervention was completed jointly by the Department of Cardiovascular Medicine, ICU, Department of Interventional Vascular Surgery, Department of Anesthesiology, and the Interventional Procedure Room, providing the patient with a safer, more minimally invasive, and more comfortable treatment strategy. This demonstrates the advantages of multidisciplinary team (MDT) diagnosis and treatment in managing complex and critically ill cases and will bring benefits to more similar patients.

What is ECMO?

ECMO stands for extracorporeal membrane oxygenation, also known as an artificial heart-lung machine. It works by draining blood from the body through blood vessels into an extracorporeal heart-lung machine for pressurization and oxygenation, and then pumping it back into the body. It can provide temporary cardiopulmonary support for patients with severe cardiopulmonary failure, buying precious time for the rescue of critically ill patients. This device became widely known to the public over the past 3 years and saved many patients with severe COVID-19. It is currently mainly indicated for patients with cardiac arrest, acute severe heart failure, and acute severe respiratory failure.

Intravenous infusion of cell therapy is a safe and effective treatment for vitiligo.

Vitiligo is an acquired, chronic, and recurrent skin disorder characterized by patchy depigmentation. It is caused by the destruction of epidermal melanocytes.

Vitiligo can be disfiguring, often leading to varying degrees of psychosocial distress and a decline in patients’ quality of life. Currently, the etiology of vitiligo has not been fully elucidated, and effective treatment options remain limited. Therefore, there is an urgent need to find an effective therapeutic approach for vitiligo.

Research on the pathogenesis of vitiligo indicates that immune mechanisms, along with other pathogenic factors, play a crucial role in the onset and progression of the disease; this significance has been confirmed by numerous studies.

1701510163554841

1. The Clinical Challenge: Up to 80% of Patients Lack Effective Treatment

Clinical data reveals that 80% of vitiligo patients do not receive effective treatment, and the ineffective rate of various therapies for vitiligo patients is as high as 50%.

While vitiligo does not affect the body’s physical health or physiological functions, its visual impact places a tremendous emotional and mental burden on patients.

2. The Breakthrough: Unique Advantages of Mesenchymal Stem Cells (MSCs)

Mesenchymal Stem Cells (MSCs) have garnered significant attention due to their unique biological properties, including:

  • Immunomodulatory properties

  • Promotion of tissue regeneration

  • Low post-transplantation rejection rates

Latest Clinical Evidence:

A recent study in India involving cell transplantation therapy for vitiligo patients showed that transplantation efficiency can be predicted by the infiltration of CD8+ T cell activity around the lesions. Meanwhile, the results demonstrated that these cells could significantly inhibit the skin-homing activity of CD8+ T lymphocytes, suggesting the great potential of cell therapy in improving the transplantation efficiency and efficacy for vitiligo.1701510194945832

3. Restoring Skin Tone: Clinical Practice of Stem Cell Therapy

Clinical researchers at Noble Clinic in Bangalore, India, pointed out that with recent advances in biotechnology and the emergence of new technologies such as cell transplantation surgery and stem cell therapy, it is now possible for the majority of patients to restore their skin tone.

Researchers explained that stem cells are injected intravenously into the body, which helps stabilize the spread of vitiligo and promotes pigmentation over time. This is because these cells possess superior immunosuppressive and immunomodulatory properties.

Most vitiligo patients suffer from autoimmune diseases, in which the patient’s immune system malfunctions and produces autoantibodies—proteins that destroy color-producing cells in the skin called melanocytes. Once these cells are killed, pigmentation does not occur, and the skin turns white. The intervention of stem cell therapy precisely blocks this destructive process from its immunological root.

4. Policy Empowerment: Accelerating Innovation in the “Lecheng Medical Pilot Zone”

As a “special zone” for medical innovation in China, the Boao Lecheng International Medical Tourism Pilot Zone enjoys core policy advantages such as “special licensed medical treatment, special research, and special operation.” Here, cutting-edge technologies like mesenchymal stem cell therapy can leverage the pilot policies granted by the state to accelerate clinical translation and application. This allows domestic patients to access internationally advanced cell therapy technologies without traveling abroad, bringing true “new hope” to the clinical treatment of vitiligo.

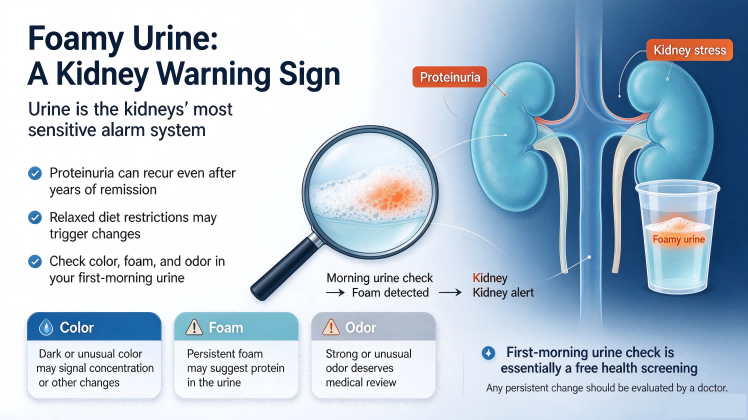
Foamy Urine: A Kidney Warning Sign

Foamy Urine: A Kidney Warning Sign

Foamy Urine: A Kidney Warning Sign

“How did you find out?” Dr. Wang Tiemin, the expert and hospital director, asked the patient and family members before him.

Outside, the rain was pouring relentlessly, stirring up veil after veil of mist. In the consultation room sat a returning patient. After several years without a follow-up visit since recovery, the once slightly soft and youthful face had grown angular and defined.

When the patient first came to the hospital in early 2018, he was tangled in worry and distress over “urinary protein.” After systematic treatment integrating Chinese and Western medicine, his urinary protein turned negative, and 24-hour urinary protein dropped to the normal range. He continued taking herbal medicine for consolidation, and follow-up reviews kept the condition stable.

Meanwhile, the weight of the word “kidney disease” gradually faded. At first, it was a boulder lodged in the hearts of the patient and his family; as the treatment took full effect, it was worn down into pebbles, then gravel, until it became a weightless speck of dust — no weight in the heart, invisible to the eye. When the suffering lost its weight and its shape, everything returned to how it was before.

After Stabilization, Dietary Restrictions Were Fully Loosened

As the condition stabilized, the patient’s diet opened up completely. According to what was learned, high-salt, high-sugar, and high-fat meals, ice-filled coffee and cold drinks, beef and mutton that easily provoke the immune system — foods once strictly avoided — had become ordinary daily fare. The kidney-damaging components and metabolic burdens in these meals accumulated in the body once again, slowly overwhelming the metabolic balance restored by medication.

“Just the past couple of days I saw foam in his urine. I said, no, we need to get this checked.” The patient’s father was the first to notice the abnormality.

Foamy Urine, in Medical Terms, Is “Proteinuria”

If the everyday phenomenon of “foam in urine” is translated into medical terminology, it is “proteinuria.” Protein leaking from the kidneys changes the surface tension of urine — much like adding egg white or dish soap to water — causing large amounts of foam that does not easily dissipate. This is an abnormal signal mentioned by many patients at their first visit, and it covers a very wide range of conditions.

There are many types of kidney disease — IgA nephropathy, membranous nephropathy, hypertensive nephropathy. Why is proteinuria the first to appear in all of them?

Because what is most fragile is always the first to give way. For the kidney, the most fragile part is the filtration barrier. It blocks proteins based on molecular size and charge; structurally, it is like an extremely “fine sieve.”

Because it is so fine, any slight damage from inflammatory reactions or metabolic attack will impair the structure of the filtration barrier. In primary nephritides such as IgA nephropathy and membranous nephropathy, the deposition of immune complexes directly damages the basement membrane or podocytes, causing “holes in the sieve” of the filtration barrier and allowing protein to leak out. Likewise, metabolic attack from high glucose toxicity directly injures podocytes — which can barely regenerate — and once damaged, the negative charge barrier on the “sieve” disappears, also leading to protein leakage.

Therefore, proteinuria is the earliest and most sensitive marker of glomerular injury, and foamy urine has become the most common kidney disease signal.

Urine Self-Check: A Free Checkup

This also shows how keenly urine reflects abnormalities in the body. From a health-warning perspective, a self-check of urine is equivalent to a free checkup. Morning urine in particular — stored in the bladder for 6–8 hours, undisturbed by food and activity, and concentrated overnight — can amplify abnormal signals to the greatest extent.

It is recommended to self-check from the following 3 aspects:

1. Look at Color

  • Normal: pale yellow or amber.

  • Dark tea-colored or soy-sauce-colored: be alert to liver/gallbladder problems or muscle breakdown.

  • Meat-washing-water-colored or red: may indicate stones, infection, or kidney problems.

  • Rice-water-like milky white: watch for lymphatic or urinary tract infection.

2. Look at Foam

If the foam is fine and dense and does not dissipate after ten-plus minutes, it suggests urinary protein may be elevated — a typical sign of kidney injury.

3. Smell the Odor

  • Slight ammonia odor: normal.

  • Rotting-apple odor: be alert to diabetic ketoacidosis.

  • Foul odor: may indicate severe urinary tract infection.

When to Seek Medical Attention

If the above abnormalities persist for more than 3 days, or are accompanied by edema, fatigue, or lower back pain, please seek medical attention promptly for a urinalysis + kidney function test.

If it is only occasional dark color or strong odor, it is most likely due to drinking too little water or staying up late — drink two more glasses of water today, check again tomorrow, and there is no need for excessive anxiety.

The premise of a free checkup is proactive awareness. Only when you know the “signals” in your heart can you match them to the right “seat” — or rule them out directly.

Headache

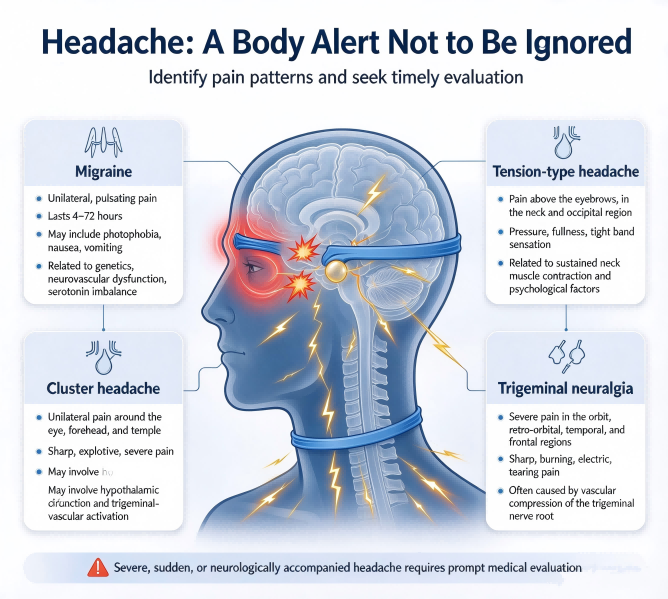
Headache: A Body Alarm That Should Not Be Ignored

Headache: A Body Alarm That Should Not Be Ignored

Nearly everyone has experienced a headache at some point, but many people dismiss it—assuming it will pass on its own or that “a painkiller will do.” In fact, severe headaches can be a warning sign of serious illness, and enduring them or self-medicating may delay treatment.

The following introduces common conditions that present primarily with headache.


I. Primary Headaches: The “Top Troublemaker” of Chronic Recurring Episodes

Primary headaches are those with no clear organic lesion or systemic disease causing them.

1. Migraine

Prevalence: Lifetime prevalence of about 18%, more common in women than men.

Features:

  • Often occurs on one side of the head, with unilateral, pulsating or throbbing characteristics

  • Typically lasts 4–72 hours, and may be accompanied by photophobia, nausea, vomiting, and other discomfort

  • Some patients experience blurred vision and other symptoms, which can severely affect daily work and life

Causes: Related to genetics, neurovascular dysfunction (such as activation of the trigeminovascular system), and imbalance of brain neurotransmitters (such as serotonin).

2. Tension-Type Headache

Incidence: The most common headache type in adults, slightly more common in women.

Features:

  • Slow onset, gradually increasing in severity, and may last for days or years

  • Pain is located above both brow ridges, in the neck, and in both occipital regions, often appearing after emotional stress, excitement, fatigue, or staying up late

  • Often presents as dull pain, like wearing a hat on the head, with a sense of pressure, fullness, tightness, or band-like constriction; may also present as heaviness in the head and shoulders

Causes: Sustained contraction of head and neck muscles (such as prolonged tension or strain) stimulates nerve endings within the muscles to cause pain; psychological factors (such as anxiety and depression) may also play a role.

3. Cluster Headache

Rarity: Male incidence is about 5–6 times that of females, with onset mostly between ages 20 and 40.

Features:

  • Mostly acute-onset severe unilateral headache, with recurrent episodes

  • Pain is mostly located in the unilateral orbit, supraorbital area, retrobulbar area, and temple

  • Presents as sharp, explosive, non-pulsating severe or extremely severe pain

Causes: May be related to abnormal hypothalamic circadian function, activation of the trigeminovascular system, histamine release, or genetic factors; the specific mechanism remains unclear.

4. Trigeminal Neuralgia

Predominant Population: Middle-aged and elderly people aged 48–59, slightly more common in women.

Features:

  • The most intense pain is concentrated in the orbit, retrobulbar area, temporal region, and frontal region, sometimes involving the occipital region, maxilla, neck, ear, and teeth, and occasionally radiating to the ipsilateral shoulder and arm

  • The pain is extremely severe, often presenting as stabbing, burning, throbbing, sharp, electric-shock-like, tearing, or drilling pain

Causes: Most cases involve vascular compression of the trigeminal nerve root (such as displacement of the superior cerebellar artery); a minority are caused by tumors, inflammation, or demyelinating lesions of the nerve.


II. Secondary Headaches: Caused by Identifiable Diseases

1. Headaches Caused by Intracranial Lesions

① Subarachnoid Hemorrhage

A very serious, sudden-onset severe headache, partly caused by increased intracranial pressure, presenting as localized or generalized headache, and may be accompanied by other central nervous system symptoms or signs, such as severe nausea, vomiting, impaired consciousness, and meningeal irritation signs (such as neck stiffness).

② Intracerebral Hemorrhage

Sudden severe headache, vomiting, impaired consciousness, and focal neurological deficits (such as hemiplegia and aphasia), mostly caused by vascular rupture due to hypertension or vascular disease; CT can quickly confirm the diagnosis. The condition is dangerous and progresses rapidly, requiring emergency reduction of intracranial pressure and blood pressure control; some cases require surgical removal of the hematoma to save life.

③ Cerebral Venous Sinus Thrombosis

A rare cerebrovascular disease, mainly presenting with headache, papilledema, and focal neurological deficits, often caused by increased intracranial pressure due to impaired venous return. Causes are diverse, including infection, hypercoagulable states, and trauma. Imaging examinations (such as MR venography) are key to diagnosis.

④ Intracranial Space-Occupying Lesions

  • Headache features: Sudden severe headache (peaking within seconds), lasting from minutes to hours, most obvious in the morning, may be aggravated by coughing, sneezing, and other actions, mostly located in the bilateral frontal region

  • Accompanying symptoms: Often accompanied by nausea and vomiting; altered consciousness or falls may occur

⑤ Reversible Cerebral Vasoconstriction Syndrome

Often triggered by exercise, emotional stress, coughing, etc., presenting as sudden “thunderclap” severe pain lasting from minutes to hours, which may recur and gradually worsen. About 20% of patients develop stroke (ischemic or hemorrhagic), with the postpartum period being a high-risk stage; in most patients, cerebral vasospasm resolves spontaneously within weeks without sequelae.

2. Headaches Caused by Systemic Diseases

① Hypertensive Headache

  • When intracranial vascular pressure rises sharply, headache, dizziness, nausea, and other symptoms may occur

  • Pain is mostly concentrated in the occipital and temporal regions; sometimes the head feels heavy with a sense of pressure

  • After blood pressure stabilizes, headache symptoms usually gradually disappear

② Low Intracranial Pressure Headache

  • Often moderate bilateral symmetric dull or distending pain, characterized by being obvious in sitting or standing positions and quickly relieved in the lying position

  • Patients may have nausea, vomiting, neck pain, dizziness, diplopia, blurred vision, and other manifestations; severe cases may develop cerebellar tonsillar herniation, subdural or epidural hemorrhage, and other conditions

3. Cervicogenic Headache

Pain Characteristics:

  • Clear location: Unilateral occipital or frontotemporal dull pain (occasionally bilateral), often radiating to the vertex and orbit

  • Triggering mechanism: Neck movement (such as rotation and flexion) and prolonged fixed posture (such as desk work) can aggravate the pain

  • Accompanying symptoms: Neck stiffness and shoulder-back soreness; some patients have dizziness, photophobia, or tinnitus (easily misdiagnosed as migraine)

Physical Examination and Diagnostic Markers:

  • Cervical tenderness: Obvious tenderness at the C1-C3 paravertebral area or the exit of the occipital nerve

  • Nerve block test: Headache relief after diagnostic cervical nerve block is one of the gold standards for diagnosis

Causes:

  • Cervical lesions: Disc herniation and joint degeneration (commonly at C1-C3)

  • Nerve compression: Greater/lesser occipital nerves compressed by muscle spasm or fibrous tissue

  • Secondary factors: Trauma (such as whiplash injury), long-term poor posture, or inflammation


III. Other Types of Headache

1. Sinus Headache

Features:

  • Headache is mostly dull or distending pain, accompanied by nasal congestion, rhinorrhea, and facial tenderness (such as in the forehead, around the orbit, or at the cheekbone)

  • Pain may worsen when bending over, coughing, or straining

  • Headache may be more obvious in the morning and gradually lessens over time

Causes: Inflammation of the sinuses (such as the frontal and maxillary sinuses) due to infection (viral or bacterial), allergies, or nasal polyps leads to retention of sinus secretions and increased pressure, stimulating nerves and causing headache.

2. Headache Caused by Otitis Media

Features:

  • Headache is often located around the affected ear or in the temporal region, presenting as continuous distending or throbbing pain, and may be accompanied by ear pain, tinnitus, and hearing loss

  • Pain may worsen when pressing the tragus or pulling the auricle

Causes: Middle ear infection (such as bacterial or viral infection) leads to middle ear effusion and increased pressure; inflammation stimulates ear nerves and spreads to the head, causing headache. It commonly occurs after upper respiratory tract infections such as colds and sinusitis.

3. Headache Caused by Glaucoma

Features:

  • Headache is mostly severe distending pain around the orbit and in the frontal region, and may be accompanied by nausea, vomiting, blurred vision, and halos (colored rings around lights)

  • Unilateral or bilateral episodes, easily induced at night or in dark environments

Causes: In glaucoma patients, impaired aqueous humor circulation leads to increased intraocular pressure; the high pressure stimulates intraocular nerves and surrounding tissues and is referred to the head, causing headache.

4. Medication Overuse Headache

Features:

  • Headache is chronic, bilateral mild-to-moderate distending pain or tightness, occurring daily or frequently; the original headache may be temporarily relieved by medication but worsens after discontinuation (rebound headache)

Causes: Long-term excessive use of analgesic drugs reduces central nervous system sensitivity to the drugs, paradoxically inducing or aggravating headache and forming a vicious cycle.

5. Postherpetic Neuralgia

Features:

  • Headache presents as unilateral paroxysmal stabbing, burning, or electric-shock-like pain, located in the area of previous herpes zoster rash (such as the head, face, forehead, and scalp)

  • Pain may last for months to years and recur after the rash has healed; touching the skin or mild stimulation can trigger it

Causes: After varicella-zoster virus infection, the virus latently resides in nerve ganglia; upon reactivation, it damages nerves, leading to abnormal nerve function and causing persistent neuropathic pain.


IV. Which Headaches Require Immediate Medical Attention?

  • Sudden severe headache with vomiting, confusion, or limb weakness

  • Headache accompanied by high fever and neck stiffness (beware of intracranial infection)

  • Sudden vision loss, speech impairment, or unsteady gait

  • Headache noticeably worsened by coughing or straining (beware of increased intracranial pressure)

  • New persistent headache after age 50

  • Sudden headache in pregnant or postpartum women


Knee Joint Treatment

Knee Joint Injuries: How Can Stem Cell Repair Help Cartilage “Experience a Rebirth”?

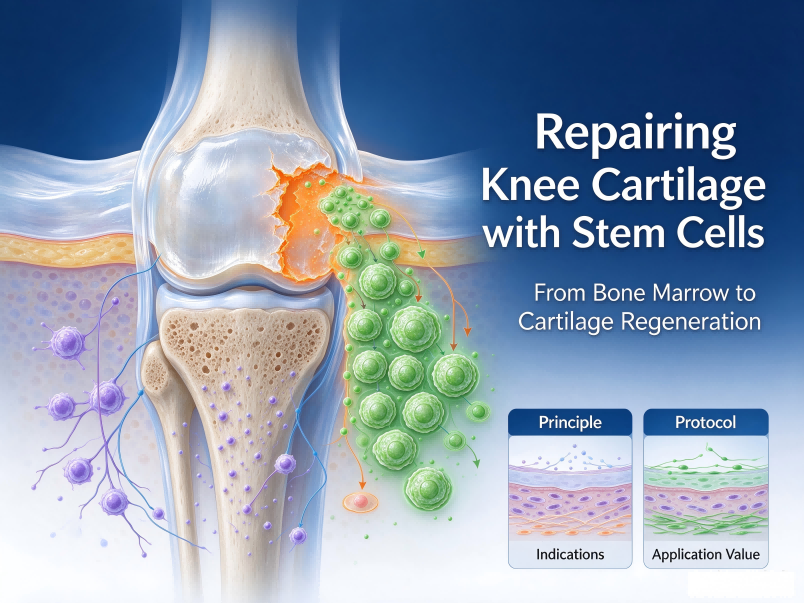
Knee Cartilage Repair: How Stem Cells Bring “New Life” to Damaged Joints

Introduction: The knee is one of the most weight-bearing and frequently used joints in the human body. Once injured, it often brings long-term pain and limited mobility. Traditional repair methods are slow to recover from and have limited efficacy. However, with the development of regenerative medicine, stem cell therapy is bringing new hope to patients with knee injuries.


How Stem Cells Repair Damaged Knees

Bone marrow stem cells possess unique self-replication and regenerative capabilities, allowing them to play a reparative role in damaged areas. Specifically, bone marrow stem cells can rapidly enhance local immunity, help clear necrotic and damaged cells, and then rely on their innate regenerative ability to repair damaged knee tissues. This process regulates the local immune balance of the knee, gradually restoring the injured joint to a healthy state.

The key to this process lies in “precision.” Through precise injections, stem cells are directed to focus on repairing the affected area. This maximizes the concentration of repair power at the site of injury and enhances the efficiency of the treatment.


Customized Treatment Protocol

Stem cell therapy for knee repair typically follows a customized personal treatment plan. The general process is as follows:

  • Professional Medical Consultation: Before treatment, a professional physician evaluates the current condition of the knee injury and arranges a personalized treatment plan accordingly.

  • First Three Months (Unilateral Knee Injections): Administer one injection per month, precisely injecting stem cells into the affected knee.

  • Following Three Months (Contralateral Knee Injections): Continue with one injection per month, applying the same precise injections to the other knee.

The entire treatment course lasts for half a year. Through continuous, phased stem cell injections, it helps to gradually repair damaged cartilage and improve the overall function of the knee.


Conclusion

Knee injuries no longer have to rely solely on traditional surgery and prolonged rest. Stem cell therapy, based on the body’s own regenerative capabilities and combined with precise injection techniques and customized treatment plans, offers a new path for repairing knee cartilage damage. For those suffering from knee problems, this is undoubtedly a rehabilitation direction worth understanding and exploring.

Laryngopharyngeal cancer

A “Three-Function Defense” in Hypopharyngeal Cancer: BNCT Opens a New Path for Recurrent Patients

The throat (pharyngolarynx) serves as a critical junction for three vital functions: breathing, swallowing, and vocalization. Anatomically, it is a confined space situated in close proximity to the carotid arteries, the thyroid gland, and the entrance to the esophagus. Hypopharyngeal cancer—most commonly squamous cell carcinoma—is often insidious; symptoms frequently appear late, meaning that by the time of diagnosis, the tumor has often already invaded surrounding structures. Among head and neck cancers, it carries a poor prognosis and a high risk of functional impairment. For a long time, the central dilemma in treating hypopharyngeal cancer has remained acute: how to achieve a radical cure while preserving the essential, yet seemingly mundane, functions of speaking, eating, and breathing?

Within standardized clinical practice, early-stage hypopharyngeal cancer can be effectively controlled through surgery or radical radiotherapy, with a reasonable chance of preserving function. However, once the disease reaches a locally advanced stage—or recurs following initial surgery or radiotherapy—treatment options become severely constrained.

Balancing radical tumor eradication with functional preservation is exceptionally difficult. Total laryngectomy or total pharyngolaryngectomy can ensure clear surgical margins, but at the cost of the permanent loss of natural speech, leaving the patient dependent on a permanent neck stoma for breathing. Furthermore, there is virtually no room for re-irradiation; the mucosal lining and cartilage of the throat have a limited tolerance for radiation, and a second course of conventional radiotherapy carries a significantly higher risk of complications, such as cartilage necrosis or severe stricture. Meanwhile, tumor progression poses a direct threat to the body’s vital pathways: airway obstruction leads to respiratory distress, while impaired swallowing prevents food intake. The condition can deteriorate rapidly, leading to a swift collapse of the patient’s overall physical state.

Boron Neutron Capture Therapy (BNCT) offers a novel approach to targeting tumors located in these “functionally critical” zones, thanks to its unique binary, targeted mechanism. In China, BNCT is currently approved for the treatment of unresectable, locally advanced, or recurrent head and neck malignancies. Unlike conventional radiotherapy, BNCT enables the precise, localized destruction of tumor cells. A boron-containing agent is administered intravenously, accumulating specifically within the tumor cells while leaving healthy tissue largely unaffected. Subsequently, the area is exposed to a neutron beam, which triggers a targeted nuclear reaction exclusively within the cancer cells. The range of the destructive particles produced by BNCT is limited to approximately the diameter of a single cell, with energy release confined entirely within the lesion. This allows for the protection of critical structures—such as laryngeal cartilage, the recurrent laryngeal nerve, the esophageal mucosa, and adjacent major blood vessels. In real-world clinical practice in China, patients with refractory laryngeal tumors—who had experienced recurrences despite multiple prior surgeries, radiation therapy, or chemotherapy—have shown significant, visible shrinkage of their lesions just 40 hours after BNCT, accompanied by a marked reduction in the sensation of a foreign object in the throat. Follow-up examinations two weeks later revealed further regression of the lesions and improved patency of the laryngeal cavity (based on individual case records; outcomes may vary).

BNCT is subject to strict clinical criteria. For early-stage hypopharyngeal cancer that can be completely resected or treated with curative-intent radiation, standard treatment protocols remain the preferred choice. Patients with unresectable tumors or late-stage recurrences should consult with specialists at an oncology hospital as soon as possible to determine their eligibility for BNCT. Candidates for BNCT must undergo a comprehensive multidisciplinary evaluation—incorporating pathological classification, imaging-based staging, and a review of their prior treatment history—before a tailored treatment plan can be established.

Advancements in cancer treatment are intended to fill gaps in conventional medicine, not to overturn existing diagnostic and therapeutic systems. For patients with recurrent or refractory hypopharyngeal cancer who have exhausted conventional treatment options, BNCT offers a new path forward: utilizing precision technology to combat stubborn disease, while employing a minimally invasive approach to preserve the vital functions of breathing, swallowing, and speech. Individuals with a long history of smoking or alcohol consumption, or those experiencing hoarseness that persists for more than two weeks, should undergo a laryngoscopic examination promptly. Patients who have already experienced a recurrence—or who have been told that “no further treatment is possible”—should avoid a “wait-and-see” approach; instead, they should seek a formal, professional evaluation, as every potential window for treatment is precious.

Jiahui Completes First International CAR-T Treatment

First Foreign CAR-T Patient Discharged in China

Since CAR-T therapy was approved for marketing in China, the Shanghai Jiahui International Cancer Center has worked with domestic and international partners to actively build an international CAR-T diagnosis and treatment platform in areas such as clinical experience sharing, academic exchange, and blood cancer education. At the same time, the multidisciplinary treatment team at Jiahui International Cancer Center has kept pace with international advanced standards and carried out a series of explorations in the clinical practice of new concepts and new technologies, hoping to bring new hope of cure to more patients with hematologic malignancies. The first foreign patient in China to receive axicabtagene ciloleucel CAR-T therapy was discharged smoothly three weeks after CAR-T cell infusion. On the day of discharge, the Jiahui medical and nursing team, who had accompanied the patient through every difficult moment of treatment, gathered with the patient’s family and friends outside the ward of the cancer center and prepared a special “discharge commemorative ceremony” for the patient to congratulate her on successfully completing CAR-T therapy.

A Foreign Mother of Three Diagnosed in Shanghai with “Primary Refractory” Lymphoma

Lyn comes from Singapore, is 40 years old, is a mother of three, and has lived in Shanghai for 15 years. Leading a healthy life, Lyn enjoys gathering with friends and has always maintained a fitness habit. In mid-2022, Lyn suddenly felt severe pain in the shoulder, neck, and upper limbs and could not sleep well all night. At first, Lyn thought it was a stiff neck, but after some time the symptoms became increasingly severe and even affected breathing. Lyn went to the emergency department of Shanghai Jiahui International Hospital for examination, where a huge mass 15 cm in diameter was found in the mediastinum. The compression from the large mass not only caused limb pain but also affected the nearby heart, great vessels, and lungs, leading to superior vena cava syndrome (SVCS), at one point causing difficulty breathing and posing an immediate life threat. The Jiahui hematology-oncology team quickly confirmed the diagnosis of “primary mediastinal large B-cell lymphoma” through biopsy pathology. This is a relatively rare lymphoma subtype, occurring mostly in young people, especially women.

After rapid confirmation of the diagnosis, the Jiahui hematology-oncology team immediately conducted an MDT multidisciplinary discussion and quickly formulated a comprehensive intensified treatment plan for Lyn. Lyn subsequently underwent comprehensive treatments including chemotherapy combined with targeted therapy and consolidation radiotherapy. Unfortunately, Lyn was insensitive to both chemotherapy and radiotherapy; the lymphoma shrank by half and then stopped shrinking, and soon began to progress. Lyn’s condition belonged to “primary refractory” lymphoma; patients who fail to achieve complete remission through standard chemoradiotherapy or who relapse and progress soon after treatment generally have a poor prognosis. Therefore, after full evaluation by the Jiahui hematology-oncology team and in accordance with international and domestic guideline recommendations, the team unanimously concluded that Lyn urgently needed more effective new treatment. The CDE website announced that CAR-T cell immunotherapy was officially approved in China for second-line treatment of adult large B-cell lymphoma, once again igniting Lyn’s hope.

CAR-T therapy, namely “chimeric antigen receptor T-cell therapy,” is a major breakthrough in individualized cellular immunotherapy for human cancer. It mainly involves collecting the patient’s T cells, performing in vitro genetic engineering modification to enhance the ability of T cells to specifically recognize tumors; subsequently, a large number of expanded “armed” T cells (i.e., CAR-T cells) are infused back into the patient to precisely kill tumor cells, and they can also form immune memory T cells, thereby achieving specific and durable antitumor effects.

Currently, the approved indications for CAR-T in China are lymphoma and myeloma. Because different patients have individualized particularities, and CAR-T therapy involves multiple key steps such as patient screening, bridging therapy, adverse reaction management, and long-term follow-up, this therapy places extremely high demands on the professionalism of the hematology-oncology team and the comprehensive diagnosis and treatment capabilities of multiple departments. Therefore, it needs to be carried out in medical centers with rich experience in hematologic tumor diagnosis and treatment and with multidisciplinary comprehensive construction.

Should they choose Shanghai, return to Singapore, or go to the United States for treatment? After careful consideration, Lyn’s family ultimately decided to undergo this internationally advanced medical therapy at Shanghai Jiahui International Hospital. Lyn’s husband shared that there were multiple factors behind this decision: first, considering the children’s schooling in Shanghai; second, the cost of CAR-T treatment abroad is far higher than in China and the waiting period is at least 3–6 months; third and most importantly, their trust in the clinical comprehensive strength and comprehensive medical support of Shanghai Jiahui International Hospital. From the first visit to the emergency department, the professionalism and meticulous care of the Jiahui team left a deep impression on Lyn’s family, and staying at Jiahui allowed them to enjoy an internationally advanced diagnosis and treatment experience in a familiar city. Facts proved that the decision at that time was very correct. The Jiahui International Cancer Center quickly launched the CAR-T clinical process, hoping to seize the best treatment timing for Lyn.

CAR-T Initiation: Everything Advanced Intensely but Orderly

As the first international hospital in Shanghai able to carry out CAR-T therapy, Shanghai Jiahui International Hospital attached great importance to this project. For this treatment, departments including the cancer center, cardiovascular medicine, neurology, ICU, respiratory medicine, gastroenterology, nephrology, imaging, laboratory medicine, and pharmacy, as well as the cancer center nursing team, collaborated closely, repeatedly conducting multiple rounds of training and scenario simulations in the early stage and promptly updating the patient’s condition.

After preliminary bridging therapy, infection screening, and pre-collection confirmation, the Jiahui hematology team collected Lyn’s cells and successfully completed the infusion of CAR-T cells.

After completion of the infusion, the Jiahui multidisciplinary team stood ready and closely monitored changes in Lyn’s various physical indicators and symptoms. On the 7th day after infusion, Lyn developed CRS symptoms such as fever, hypotension, and vomiting. The Jiahui medical and nursing team promptly carried out treatment according to the emergency plan previously formulated, bringing the condition under control in a timely manner. After CAR-T cell infusion, the “T-cell special forces” entering the body expanded well, and the patient’s pain symptoms caused by the tumor were relieved. After clinical evaluation confirmed stable condition, Lyn smoothly “exited the unit,” returning from the separately set CAR-T dedicated isolation ward to the general oncology ward. Lyn was discharged smoothly. Although long-term monitoring and subsequent treatment were still needed afterward, the most difficult hurdle had been safely passed.

Cutting-Edge Therapy Lands in China, Multidisciplinary Professional Team Provides Support

For Lyn, Shanghai is a city of different significance. During the 15 years Lyn and family lived in Shanghai, they not only witnessed the gradual improvement of Shanghai’s overall international image but also personally experienced that the application of new medical technologies in Shanghai is advancing with great strides toward the global frontier level of Europe and the United States. It is understood that Lyn was the first CAR-T patient at Shanghai Jiahui International Hospital and also the first foreign patient in China to complete axicabtagene ciloleucel CAR-T therapy. The successful implementation of this therapy at Shanghai Jiahui International Hospital cannot be separated from Lyn’s trust in and recognition of domestic medical quality, and it further proves Jiahui’s comprehensive strength in the field of international medicine.

It is reported that the Jiahui International Cancer Center of Shanghai Jiahui International Hospital has completed multiple CAR-T training certifications and has been authorized for treatment certification and carried out clinical application of CAR-T cell therapy. In terms of cost, CAR-T expenses mainly include two parts—drug costs and non-drug costs. The total treatment cost of this therapy in China is far lower than in the United States and other European and American countries, and commercial insurance payment has been opened, with other payment methods also to be implemented. At present, CAR-T treatment services are jointly linked with the international diagnosis and treatment platform and Shanghai’s local high-quality medical resources to provide patients in need with CAR-T-related diagnosis and treatment services, including outpatient consultation, screening and evaluation, T-cell collection, CAR-T cell infusion, and adverse reaction monitoring and management. With reference to international CAR-T clinical application guidelines, Jiahui has formulated standard service processes and a quality control system to safeguard customized treatment for patients; at the same time, the cancer center, cardiovascular medicine, neurology, ICU, respiratory medicine, gastroenterology, nephrology, imaging, laboratory medicine, and pharmacy departments, as well as the cancer center nursing team, form a CAR-T multidisciplinary clinical professional team. The hospital is equipped with advanced T-cell extraction equipment and CAR-T dedicated wards, fully ensuring patient monitoring needs and comfort experience in both hardware and software.

Endocrine

Man lands in ICU with sky-high blood lipid levels after daily nut consumption

Man lands in ICU with sky-high blood lipid levels after daily nut consumption

Mr. Fang (a pseudonym), 41, never imagined that simply eating an extra handful of nuts would land him in the intensive care unit (ICU) and necessitate emergency interventions, including hemofiltration. The culprit behind this crisis was acute pancreatitis triggered by hyperlipidemia—a condition brought on by a high-fat intake—which, compounded by his existing underlying health issues, made his situation exceptionally perilous.

On the day of the incident, shortly after consuming a large quantity of nuts, Mr. Fang began experiencing persistent upper abdominal pain. His family rushed him to Xi’an Gaoxin Hospital, where CT scans and amylase level tests confirmed a diagnosis of acute pancreatitis. Further examination revealed that his triglyceride levels had skyrocketed to 82.40 mmol/L (the normal range is typically <1.7 mmol/L). He was also suffering from diabetic ketoacidosis and hyperglycemia. Given his medical history—which includes coronary heart disease (with prior coronary stent placement) and type 2 diabetes—his case presented a complex scenario of multiple pre-existing systemic conditions combined with an acute, severe illness.

Physicians in the Department of Gastroenterology at Xi’an Gaoxin Hospital identified the condition as “hyperlipidemia-induced pancreatitis”—a type often triggered by overeating or the excessive consumption of high-fat foods. With his triglyceride levels dangerously high, immediate lipid-lowering intervention was essential to prevent the pancreatic inflammation from worsening and becoming life-threatening. Because medication alone would not act quickly enough, Mr. Fang was transferred to the ICU for hemofiltration—a critical procedure used to rapidly clear triglycerides from the bloodstream. After three days of intensive care, his triglyceride levels plummeted from an off-the-charts 82.40 mmol/L to 2.99 mmol/L. His ketoacidosis was resolved, and his abdominal pain subsided, allowing him to be moved back to a general ward.

Just as it seemed he was on the mend, however, Mr. Fang attempted to take a sip of water—only for the abdominal pain to flare up once again, accompanied by a high fever. A follow-up CT scan revealed that Mr. Fang’s pancreatitis had progressed to Balthazar grade D. There was increased peripancreatic exudation, the inflammation had spread to the adjacent intestines, and a secondary infection had developed. The gastroenterology team promptly adjusted his treatment plan. With careful management, Mr. Fang’s abdominal pain was brought under control; he was eventually able to resume eating without any recurrence of pain and was successfully discharged.

Following his discharge, Mr. Fang has strictly adhered to a low-fat diet and consistently taken his lipid-lowering medication. Subsequent outpatient check-ups have shown his triglyceride levels remaining within the normal range, and his condition has stayed stable.

The Department of Gastroenterology at Xi’an Gaoxin Hospital notes that autumn and winter are peak seasons for acute pancreatitis. Individuals with underlying health conditions, in particular, should be wary of the risks posed by overindulging in food. Please keep the following four points in mind:

High-fat diets are “silent killers”:

While high-fat foods—such as nuts, fatty meats, and fried items—may be delicious, consuming them in excess can trigger hyperlipidemia-induced pancreatitis. Those who already have high blood lipid levels should exercise particular restraint.

Higher risk for those with underlying conditions:

Individuals with pre-existing conditions such as diabetes, coronary heart disease, or hyperlipidemia already have more vulnerable pancreatic function and metabolic systems. They should avoid overeating, stick to a light, low-fat diet, and regularly monitor relevant health indicators.

Do not “tough out” abdominal pain:

Sudden, persistent upper abdominal pain—accompanied by symptoms like bloating or nausea—could be a sign of acute pancreatitis. Seek medical attention immediately; delaying treatment can lead to a rapid deterioration of the condition.

Dietary care during recovery:

During recovery from pancreatitis, patients should follow a gradual dietary progression: starting with water, then moving to clear liquids, semi-liquids, and finally soft foods. Do not resume eating or drinking too soon, as this could irritate the pancreas and trigger a recurrence of inflammation.

Although hyperlipidemia-induced acute pancreatitis is a serious and dangerous condition, it can be effectively managed through timely medical intervention, evidence-based treatment, and long-term health management following discharge. Do not let a fleeting craving for food cause irreversible harm to your body. This is especially critical for those with underlying medical conditions, who must take to heart the importance of “controlling one’s diet and following medical advice.”

Digestive Disease Hospital, Xi’an Gaoxin Hospital

The Digestive Disease Hospital at Xi’an Gaoxin Hospital is a specialized team dedicated to the clinical study and treatment of digestive system disorders. The department provides long-term diagnostic and therapeutic services for both common and complex, severe digestive diseases in Xi’an and its surrounding regions. Through years of medical practice, the team has developed a unique clinical approach and accumulated extensive experience in managing a wide range of digestive conditions—from common ailments to complex, life-threatening cases—earning high praise from patients and their families.

Led by President Song Ying, who serves as the head of the Digestive Disease Hospital and the discipline leader, the department comprises two inpatient wards, a day-surgery unit, an endoscopy center, a laboratory, and a gastrointestinal rehabilitation center. There are 160 inpatient beds available. The endoscopy center spans 1,500 square meters and features 10 standard procedure rooms equipped with state-of-the-art technology, supported by a well-structured team of medical professionals. Key specialized procedures offered by the department include endoscopic treatment for acute gastrointestinal bleeding, endoscopic management of esophageal and gastric varices, percutaneous endoscopic gastrostomy (PEG), endoscopic sclerotherapy and band ligation for internal hemorrhoids, and endoscopic resection of gastrointestinal tumors. The Department of Gastroenterology is a key medical discipline in Xi’an and a flagship department within the hospital, boasting robust clinical expertise. It currently serves as the chair institution for four academic organizations: the Digestive Disease Prevention and Treatment Professional Committee of the Shaanxi Healthcare Society, the Gastroenterology and Digestive Endoscopy Professional Committee of the Shaanxi Non-Public Medical Institutions Association, the Digestive Endoscopy Professional Committee of the Shaanxi Research-Oriented Hospital Society, and the Digestive Endoscopy Professional Committee of the Shaanxi Association of Integrated Traditional Chinese and Western Medicine. Furthermore, it acts as a vice-chair unit for both the Esophageal and Gastric Varices Study Group and the Internal Hemorrhoids Collaborative Group under the Chinese Society of Digestive Endoscopy (CSDE). The department is also designated as a training and demonstration base for digestive endoscopy by the Chinese Non-Public Medical Institutions Association, a training center for the sclerotherapy of esophageal and gastric varices under the Chinese Medical Association, a standardized training base for the prevention and treatment of gastrointestinal bleeding in Shaanxi Province, and a governing member institution of the Asia-Pacific Portal Hypertension Alliance.

Specialized Diagnostic and Therapeutic Techniques

Carbon-13 (13C) urea breath test, food intolerance testing, transient elastography (FibroScan) for liver fibrosis, psychological assessment, routine and painless (sedated) gastrointestinal endoscopy, endoscopic chromoendoscopy for early-stage cancer detection, advanced diagnostic imaging (NBI, BLI, and LCI), endoscopic ultrasound (EUS), emergency endoscopic hemostasis, removal of foreign bodies from the digestive tract, endoscopic variceal ligation (EVL) and sclerotherapy for esophageal varices, tissue adhesive injection (glue embolization) for gastric variceal bleeding, endoscopic mucosal resection (EMR) and argon plasma coagulation (APC) for polyps, stent placement for benign or malignant esophageal and biliary strictures, endoscopic retrograde cholangiopancreatography (ERCP), endoscopic sphincterotomy (EST) for stone extraction, endoscopic nasobiliary drainage (ENBD), biliary stent placement, percutaneous endoscopic gastrostomy (PEG), endoscopic placement of enteral nutrition tubes, placement of intestinal obstruction decompression tubes, endoscopic submucosal dissection (ESD), endoscopic submucosal excavation (ESE), endoscopic full-thickness resection (EFTR), submucosal tunneling endoscopic resection (STER), and peroral endoscopic myotomy (POEM).

globalmedpool.com

An Overview of Small, Benign Liver Lesions

An Overview of Small, Benign Liver Lesions

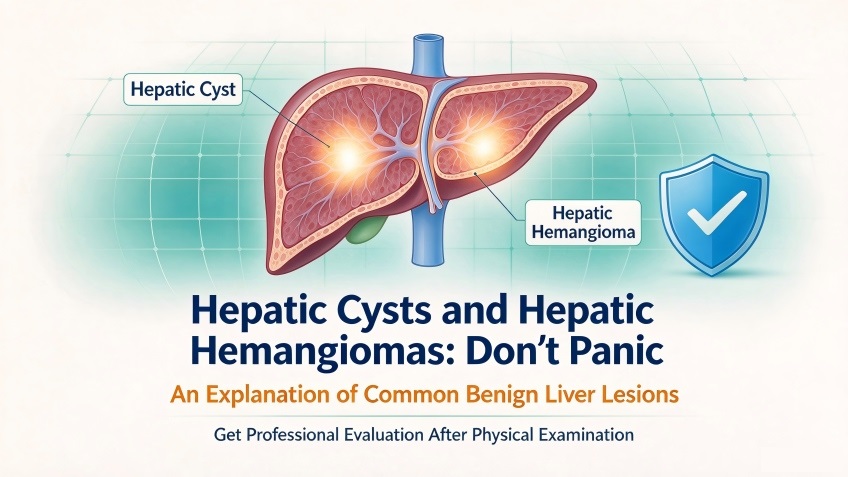
In routine medical check-ups, people are sometimes surprised to find reports of abnormal liver lesions, with “hepatic cysts” and “hepatic hemangiomas” being among the most common findings. These terms can be alarming, often leading to concerns about potential malignancy. The Radiology Department at Xi’an Gaoxin Hospital provides an overview of these two benign liver conditions to help the public better understand these “minor issues.”

 Hepatic Cysts: “Small Fluid-Filled Sacs” in the Liver

A hepatic cyst is a very common benign liver condition. In radiological imaging, it appears as a well-defined, homogeneous, low-density lesion—essentially a small, fluid-filled sac within the liver tissue. The sac contains clear, sterile serous fluid and has no connection to the intrahepatic bile ducts; therefore, it does not interfere with the normal secretion of bile.

Hepatic cysts are categorized as either congenital or acquired. Congenital cysts are generally believed to originate from developmental abnormalities of the intrahepatic bile ducts during the embryonic stage, while acquired cysts are often triggered by factors such as trauma, inflammation, or parasitic infections.

The vast majority of hepatic cysts cause no noticeable discomfort and are typically discovered incidentally during routine check-ups. Small, asymptomatic cysts generally require no specific treatment—periodic follow-up and observation are usually sufficient. If a cyst exceeds 5 centimeters in diameter and begins to exert pressure on surrounding organs, it may cause mild symptoms such as abdominal bloating, a dull ache in the upper right abdomen, or a loss of appetite. When it is necessary to distinguish a hepatic cyst from other liver lesions, CT or MRI scans can provide a clear diagnostic basis. A hallmark of a typical hepatic cyst on imaging is its smooth, well-defined border and uniform density; notably, it does not show “enhancement” (increased brightness) following the administration of a contrast agent—a key feature for identification.

Hepatic Hemangiomas: “Clusters of Blood Vessels” in the Liver

A hepatic hemangioma is the most common benign liver tumor, with cavernous hemangiomas accounting for the vast majority of cases. On diagnostic imaging, these lesions appear as well-defined masses within the liver, composed of a dense network of dilated, tiny blood vessels—resembling a tangled web of vessels. They are soft in texture, grow slowly, and do not invade surrounding healthy tissue.

The exact pathogenesis of hepatic hemangiomas remains not fully understood; however, the prevailing view is that they are linked to congenital vascular developmental abnormalities. Clinical research indicates that hepatic hemangiomas may tend to enlarge during periods of significant hormonal fluctuation—such as puberty or pregnancy—suggesting that hormonal changes may influence the lesions.

Most individuals with hepatic hemangiomas are asymptomatic. For lesions smaller than 5 cm that cause no discomfort, routine follow-up and observation are generally sufficient. If a lesion exceeds 5 cm in diameter, causes symptoms due to compression of adjacent structures, or is located beneath the liver capsule—posing a risk of rupture—it is necessary to seek medical attention so that a physician can determine an appropriate management plan. CT or MRI scans typically reveal characteristic enhancement patterns, which help clinicians distinguish hepatic hemangiomas from malignant liver tumors.

 How to Manage a Diagnosis of Hepatic Cysts or Hepatic Hemangiomas

First and foremost, avoid excessive anxiety. Both hepatic cysts and hepatic hemangiomas are benign lesions characterized by slow growth. There is no reliable evidence to suggest that hepatic hemangiomas carry a risk of malignant transformation, and congenital hepatic cysts also grow very gradually; the vast majority of patients remain entirely asymptomatic throughout their lives.

If such lesions are detected during a medical check-up, the core principle is to follow the recommendations provided by radiologists and relevant specialists. For small lesions, the standard approach is periodic monitoring to track any changes. If a lesion meets the criteria for clinical intervention, a physician will evaluate the situation and determine the most appropriate course of action—there is no need for indiscriminate surgery or medication.

Arthroscopic subacromial balloon implantation

Arthroscopic subacromial balloon implantation

Arthroscopic subacromial balloon implantation

Even buttoning a shirt had become an impossible task—for the past few years, 67-year-old Mr. L had been plagued by persistent shoulder pain. Although he had previously undergone arthroscopic rotator cuff repair on his right shoulder, a subsequent injury left him with restricted movement in that shoulder for the past six months.

An MRI scan revealed a massive rotator cuff tear (defined as a tear larger than 5 cm, or the complete rupture of two or more rotator cuff tendons), accompanied by significant muscle degeneration.

The sports medicine team at Wanying Orthopedics diagnosed Mr. L’s condition as an “irreparable massive rotator cuff tear,” meaning the tissue could no longer be repaired. Following an in-depth multidisciplinary discussion—and noting that the patient had not yet developed osteoarthritis—the team opted for an advanced procedure: the implantation of an InSpace subacromial balloon.

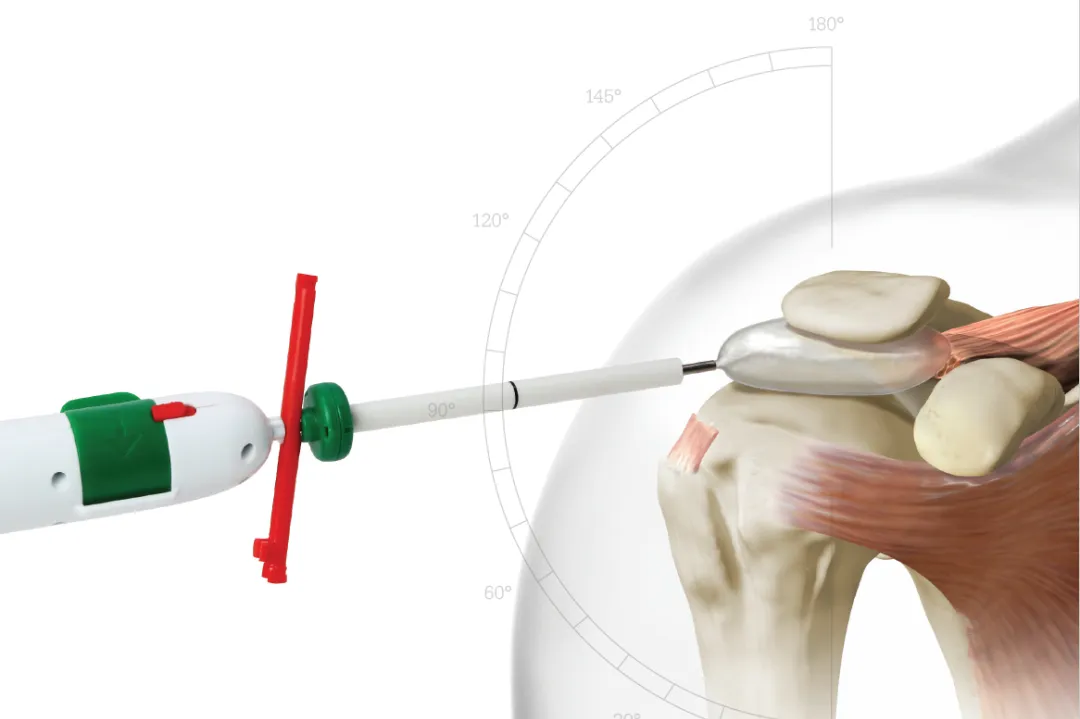
Supported by a skilled anesthesia team, the surgeons completed the balloon implantation in just 30 minutes. By placing a small, fluid-filled balloon between the acromion and the humeral head, they effectively restored the “fulcrum” for shoulder movement, re-establishing the balance of the joint’s force couples. Furthermore, the balloon prevents friction between the acromion and the humeral head, helping to halt further joint degeneration.

The surgery was a success, and Mr. L experienced immediate relief from his shoulder pain. “During the morning rounds, I was actually able to lift my arm to say hello!” he exclaimed. “Seeing such an ‘instant’ result has completely convinced me of the clinical expertise at Wanying Medical.” Mr. L was discharged the following day and will soon begin his post-operative rehabilitation.

Overcoming the Challenge of Age-Related Shoulder Pain
Yaoying Continues to Introduce Innovative Minimally Invasive Treatment Techniques

As the global population ages, rotator cuff injury has become a common clinical shoulder disorder. The condition most frequently stems from the gradual wear and tear of tendon tissue over time; without timely intervention, it often progresses to a massive rotator cuff tear. Such tears result in shoulder weakness and pain, hindering the performance of many daily activities—such as combing one’s hair or getting dressed—and causing nighttime pain severe enough to disrupt sleep.

Pain Points of Traditional Treatments

⚠️ Significant Trauma: Open surgery requires cutting the deltoid muscle, necessitating a long period of postoperative immobilization.
⚠️ High Risk: The rate of re-tearing following surgery for massive tears exceeds 40%.

Advantages of InSpace Balloon Technology

✔️ Innovative “Water Balloon” Technology: A biodegradable balloon is implanted to act as a cushion, replacing the function of a torn tendon and reducing friction.
✔️ Millimeter-Level Precision: Precise, arthroscopic placement avoids damage to nerves and blood vessels, with no disruption to the bony structures of the shoulder joint.
✔️ Rapid Recovery: Patients are typically discharged the day after surgery, with a recovery period 50% shorter than that of traditional surgery.
✔️ Minimally Invasive: The procedure is performed through three 5mm incisions, with blood loss of less than 10ml.
✔️ High Safety Profile: Since receiving its CE mark in 2010, the InSpace bioabsorbable shoulder balloon has been used to successfully treat over 28,000 patients across North America, the European Union, and other regions.
✔️ Reversible: The balloon degrades naturally over two years, leaving the option open for future surgical interventions.

Who is a candidate for the InSpace subacromial balloon implant procedure?

  • Patients with massive, irreparable rotator cuff tears—specifically those with large tears (>5 cm) that cannot be repaired through conventional surgical techniques.
  • Patients with mild to moderate glenohumeral osteoarthritis; the balloon implant can help alleviate pain caused by arthritis and improve shoulder function.
  • Patients aged 65 and older; compared to traditional surgery, the InSpace balloon implant procedure can offer faster functional recovery and pain relief.

Please note: Determining whether the InSpace balloon implant procedure is appropriate for you requires an in-person consultation at a hospital. A physician will conduct a comprehensive assessment based on your specific medical condition, overall physical health, and other relevant factors, and will then work with you to discuss and determine the most suitable treatment plan.

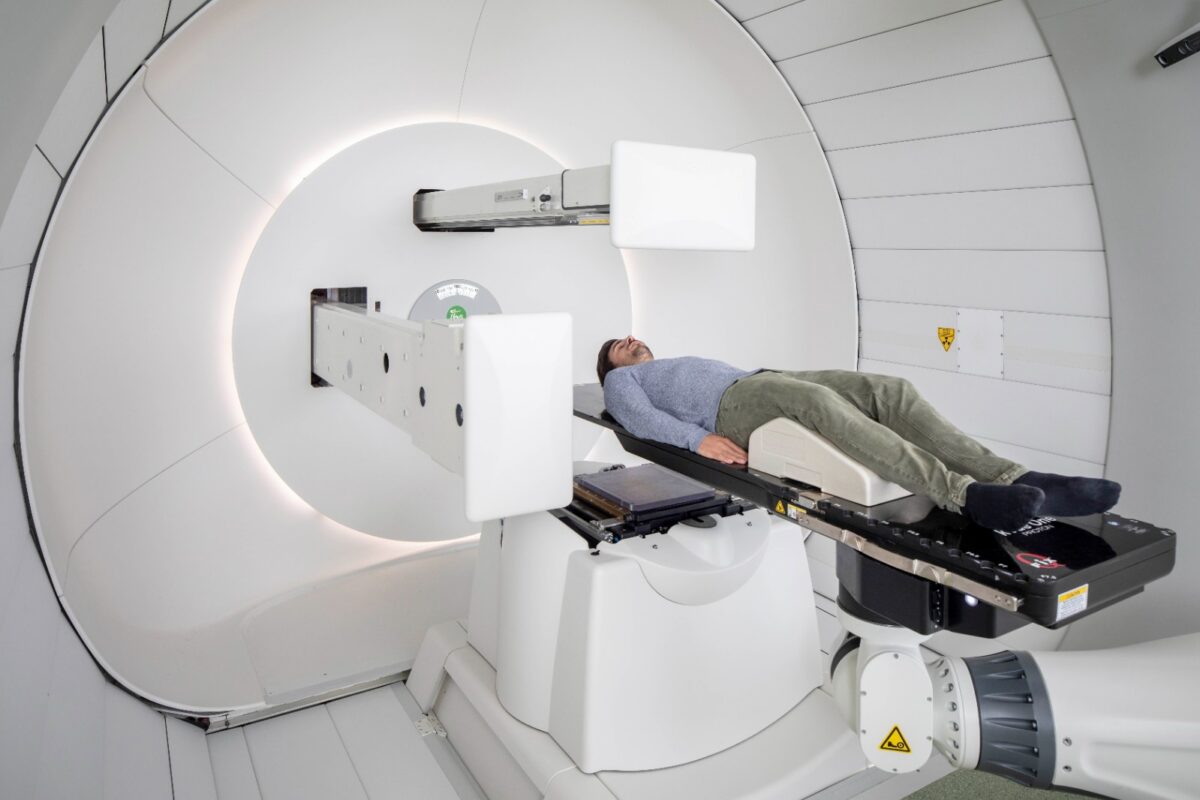
Proton Therapy: An Excellent Treatment Option for Giant Hepatic Hemangiomas

Proton Therapy: An Excellent Treatment Option for Giant Hepatic Hemangiomas

Proton Therapy: An Excellent Treatment Option for Giant Hepatic Hemangiomas

Most hepatic hemangiomas grow slowly and typically do not cause obvious clinical symptoms; they are usually detected during routine health check-ups or abdominal ultrasound and CT scans performed for other conditions.

In some patients, the hemangioma is large enough to compress adjacent organs—such as the gastrointestinal tract—leading to symptoms like upper abdominal discomfort, distension and pain, indigestion, nausea, and vomiting. In very rare instances, the hemangioma may rupture, triggering critical abdominal complications such as intraperitoneal hemorrhage.

Upon detection, the preferred clinical approach is regular follow-up to monitor changes in the tumor’s size and morphology, with timely intervention initiated should any abnormalities arise.

Treatment becomes necessary when the hemangioma exceeds 5 cm in diameter or causes clinical symptoms; when it continues to enlarge, compressing surrounding organs or adversely affecting the cardiovascular system; or when there is a risk of rupture, hemorrhage, or life-threatening complications. Current mainstream treatment modalities include surgical resection, interventional therapy, and radiotherapy.

 46-Year-Old Woman Diagnosed with Giant Hepatic Hemangioma; Blood Transfusion Contraindication Complicates Surgery

Literature reports a case involving the use of proton therapy for a giant hepatic hemangioma. Researchers note that proton therapy is safe for treating hepatic hemangiomas, achieves ideal local control, causes no severe liver damage, and minimizes the risk of long-term adverse effects.

The patient was a 46-year-old woman with normal liver function. Elevated hepatobiliary enzyme levels were noted during a routine check-up, and an abdominal ultrasound revealed a hepatic mass. An abdominal CT scan showed an 80 × 80 mm lesion in the left lobe of the liver; combined with contrast-enhanced imaging, the lesion was confirmed to be a giant hepatic hemangioma.

Imaging also revealed peripheral bile duct dilation, with the bile ducts and blood vessels compressed by the tumor. Physical examination showed a flat, soft abdomen with tenderness in the right costal region. Comprehensive assessment indicated that the giant hepatic hemangioma required prompt intervention.

 Continued Tumor Shrinkage and Sustained Remission for 15 Years After Proton Therapy

Due to religious restrictions preventing blood transfusions—which made surgical resection difficult to perform—the patient was referred for proton therapy. Initial assessment indicated Child-Pugh Class A liver function (suggesting good function or only mild impairment) and no elevation in tumor markers.

The patient underwent proton therapy with a total dose of 28.6 Gy delivered in 13 fractions. Following treatment, the tumor continued to shrink: it measured 50×50 mm after one year, 44×33 mm at 1.5 years, 40×26 mm at two years, and 36×26 mm at three years. Annual ultrasound follow-ups showed continued tumor regression.

An MRI scan 11 years post-treatment revealed the lesion had shrunk to 29×15 mm; the lesion appeared stable and was difficult to identify via ultrasound. Aside from localized atrophy in the irradiated area, the remaining liver structure remained intact, with no hepatic deformity. Follow-up blood tests showed no elevation in hepatobiliary enzymes, and symptoms of abdominal discomfort had completely resolved. The patient achieved a performance status score of 0, maintained a normal lifestyle, and attained clinical recovery. Ultrasound and imaging follow-ups confirmed that the state of remission has been sustained for 15 years.

Complete resolution of liver metastases from esophageal cancer following 30 sessions of proton therapy.

Complete resolution of liver metastases from esophageal cancer following 30 sessions of proton therapy.

Complete resolution of liver metastases from esophageal cancer following 30 sessions of proton therapy.

Proton Therapy for Liver Cancer: 5-Year Local Progression-Free Rate Exceeds 85%

Among men under the age of 60, liver cancer ranks first in terms of cancer incidence and mortality.

Deaths among cancer patients are largely caused by local recurrence and distant metastasis. The liver is the body’s largest solid organ and has a rich blood supply; consequently, primary liver tumors are prone to intrahepatic or extrahepatic metastasis, and the liver is also a common site for metastasis from many other malignancies.

Metastatic liver cancer—also known as secondary liver cancer—refers to tumors formed when malignancies from other parts of the body spread to the liver. During the course of malignant disease, 25% to 50% of primary tumors metastasize to the liver. Statistically, liver metastasis is the second most common form of spread, ranking just behind lymphatic metastasis. Metastases originating from the digestive tract and pelvic region are particularly common, involving sites such as the stomach, small intestine, colon, rectum, gallbladder, pancreas, prostate, uterus, and ovaries; however, metastases from the thyroid, breast, nasopharynx, lungs, and kidneys are also frequently observed.

Proton Therapy for Liver Cancer: 5-Year Local Progression-Free Rate Exceeds 85%

Surgery is the preferred treatment for most early-stage liver cancers, yet the majority of patients are ineligible for surgery at the time of diagnosis. Radiation therapy serves as a crucial treatment option for unresectable liver cancer. Liver cancer cells are relatively sensitive to radiation; however, the low radiation tolerance of normal liver tissue limits the use of X-ray radiotherapy, particularly in patients with multiple liver tumors. Proton therapy allows for the delivery of high radiation doses to the tumor while significantly reducing the dose received by surrounding normal tissues.

Compared to X-ray therapy, proton therapy offers superior protection for normal liver tissue. Studies indicate that proton therapy yields favorable outcomes for primary hepatocellular carcinoma, achieving a 5-year local progression-free rate of over 85%. Additionally, research suggests that proton therapy is associated with a reduction in adverse events. In a Phase II trial, acute toxicity during proton therapy was minimal, consisting only of Grade 1 erythema and mild fatigue; no acute toxicities interfered with the proton therapy.

A 53-year-old male diagnosed with esophageal cancer and three liver metastases

A case of proton therapy for liver metastases from esophageal cancer was previously reported in the journal International Surgery.

A 53-year-old male presented with complaints of heartburn and a choking sensation. Esophagogastroduodenoscopy revealed cancer at the esophagogastric junction and in the upper thoracic esophagus. Additionally, computed tomography (CT) scans showed multiple liver metastases and mediastinal lymph node metastasis. Specifically, there were three liver metastases (measuring 45.5 mm in segment S2, 67.5 mm in S4, and 48.3 mm in S6) and one mediastinal lymph node metastasis. Routine laboratory test results, including tumor marker levels, were normal. Positron emission tomography (PET) showed fluorodeoxyglucose (FDG) accumulation in the liver (segments S2, S4, and S6), the primary tumor sites (esophagogastric junction and upper thoracic esophagus), and a left supraclavicular lymph node. Based on these findings, the patient was diagnosed with Stage IV disease (T3N1M1 [liver] for the lower thoracic esophageal cancer and T3 for the upper thoracic esophageal cancer) and a chemotherapy regimen was planned.

Over 30 proton therapy sessions: Complete elimination of all tumors

The efficacy of chemotherapy was assessed using the World Health Organization (WHO) criteria for response in solid tumors. However, disease progression was observed after four cycles of chemotherapy. Consequently, the treatment plan was modified to combine proton therapy with chemotherapy. Proton beams were delivered via two oblique ports. Initially, the primary tumors, the left supraclavicular lymph node, and the liver metastasis in segment S6 were treated with proton therapy—receiving 31 fractions (total dose: 68.2 Gy) and 30 fractions (total dose: 66 Gy), respectively. Subsequently, chemotherapy was administered. Finally, the liver metastases in segments S2 and S4 were treated with proton therapy, receiving 30 fractions for a total dose of 66 Gy. Approximately two months after the completion of proton therapy combined with chemotherapy, PET scans showed the disappearance of FDG uptake in all liver metastasis sites, the primary tumor, and the mediastinal lymph nodes.

CT and PET imaging confirmed the complete resolution of all target lesions—specifically those in liver segments S2, S4, and S6, as well as the upper mediastinal lymph nodes. Esophagogastroduodenoscopy revealed the resolution of non-target lesions (the primary tumor located at the upper thoracic esophagus and the gastroesophageal junction), indicating a complete remission of the esophageal cancer. No treatment-related acute or late toxicities were observed.

In summary, proton therapy is a highly advanced medical technology that yields excellent results in treating both primary and metastatic liver cancer, offering new hope to cancer patients today.

Raffles Hospital

Opening a lifeline for acute stroke patients

In the race for life, time is of the essence; every second can determine the difference between life and death. Recently, the team led by Professor Chi Luxiang at the Chongqing Raffles Pan-Vascular Disease Management Center executed a dramatic life-saving intervention, successfully performing surgery on Mr. Xie, a 66-year-old patient suffering from an acute stroke, and pulling him back from the brink of death.

Critical Moment: Stroke Strikes, Life Hanging by a Thread

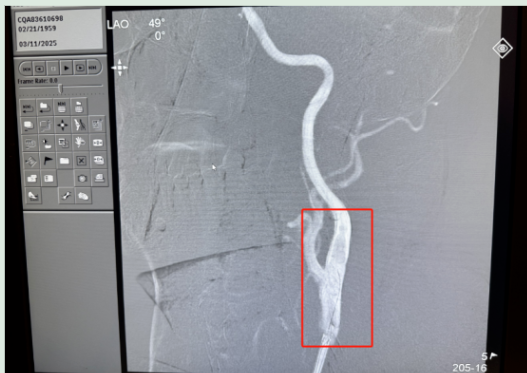
Mr. Xie suddenly experienced limb weakness and slurred speech and was rushed to Chongqing Raffles Hospital. Emergency imaging assessments confirmed a diagnosis of acute ischemic stroke. By this time, the patient had already missed the optimal time window for intravenous thrombolysis, rendering standard thrombolytic therapy unfeasible. With the blood vessel remaining occluded and brain tissue suffering progressive ischemic necrosis, the patient faced an imminent risk of massive cerebral infarction and cerebral herniation—conditions that could prove fatal.

Acute stroke treatment relies on a strict “golden window” for intervention. Once a large vessel is occluded, conservative treatment after this window passes yields a very poor prognosis, with significantly higher rates of disability and mortality. Faced with this complex clinical challenge, Professor Chi Luxiang’s team immediately activated the stroke emergency “green channel.” They rapidly conducted a multidisciplinary consultation to comprehensively assess vascular conditions and the extent of cerebral ischemia, subsequently formulating an interventional surgical plan.

Precision Intervention: Minimally Invasive Surgery Saves the Day

The team decided to perform **thrombus aspiration and carotid artery stenting** for Mr. Xie. This type of minimally invasive neuro-interventional procedure requires no craniotomy—leaving only a tiny puncture wound—but demands exceptional precision and diagnostic skill from the surgical team.

During the procedure, guided by digital subtraction angiography (DSA) equipment, Professor Chi and his team navigated a micro-catheter from the femoral artery into the intracranial space. They precisely reached the site of the occlusion, successfully aspirated and removed the obstructing thrombus, and simultaneously implanted a stent into the narrowed carotid artery to restore blood flow to the brain. The surgery was completed successfully; the occluded vessel was reopened, and blood supply to the brain tissue was rapidly restored.

Following the procedure, the patient was transferred to the Intensive Care Unit (ICU) for close monitoring. Following collaborative management by the critical care, neurology, neurosurgery, and nursing teams, the patient’s limb strength and speech function gradually recovered; the patient was successfully transferred out of the intensive care unit and, after undergoing subsequent rehabilitation, returned to a normal life.

Proton Therapy Precisely Targets "Double Primary Cancers": Prostate Lesion Inactive; Rectosigmoid Junction Cancer Locally Eradicated

Proton Therapy Precisely Targets “Double Primary Cancers”: Prostate Lesion Inactive; Rectosigmoid Junction Cancer Locally Eradicated

Proton Therapy Precisely Targets “Double Primary Cancers”: Prostate Lesion Inactive; Rectosigmoid Junction Cancer Locally Eradicated

Mr. C, now in his sixties—an age when he should have been enjoying his retirement—was diagnosed with both prostate cancer and cancer at the rectosigmoid junction. Faced with this sudden storm of adversity, Mr. C did not hesitate to seek active medical treatment. After consulting various sources, he came to Guangzhou Concord Cancer Center for proton therapy.

Fortunately, the personalized treatment plan tailored by the hospital’s multidisciplinary team yielded inspiring results: the prostate cancer lesion shrank, tumor markers returned to normal levels, and imaging showed no signs of residual activity. Furthermore, surgery confirmed a pathological complete response for the rectosigmoid junction cancer, marking a decisive victory in this battle against dual malignancies.

Diagnosed with double primary cancers: seeking the “globally optimal solution”

During a routine health check-up, Mr. C received an alarming result: his total prostate-specific antigen (TPSA) level had skyrocketed to more than ten times the upper limit of normal. Further examinations confirmed a diagnosis of high-risk, locally advanced prostate cancer that had already invaded the seminal vesicles.

For cases of this nature, surgery often fails to completely eradicate the tumor, and the risk of postoperative recurrence is high. The National Comprehensive Cancer Network (NCCN) guidelines explicitly recommend “external beam radiotherapy combined with long-term androgen deprivation therapy” as a top-tier treatment option for prostate cancer classified as T3b or higher (indicating tumor invasion into the seminal vesicles or beyond).

Given the prostate’s unique anatomical location—in close proximity to the bladder, small intestine, and rectum—traditional photon radiotherapy frequently affects these normal tissues. This can lead to adverse effects such as radiation enteritis, diarrhea, rectal bleeding, or hematuria, severely compromising the patient’s quality of life. With advancements in medical technology, proton therapy has emerged as a highly effective treatment for prostate cancer. Studies indicate that the “Bragg peak” effect of proton therapy can reduce radiation exposure to organs near the prostate by 80%, thereby minimizing radiation to the bladder, intestines, and surrounding healthy tissue; furthermore, men undergoing proton therapy face a significantly lower risk of side effects such as sexual dysfunction and urinary incontinence.

Seeking proton therapy, Mr. C traveled to Guangzhou Taihe Cancer Hospital. Unexpectedly, a comprehensive follow-up examination revealed a second primary cancer: a rectosigmoid junction carcinoma.

Faced with the complex scenario of dual primary cancers—prostate cancer and rectosigmoid junction carcinoma—both located in the pelvic region, the proton therapy team at Guangzhou Taihe Cancer Hospital convened a multidisciplinary discussion involving experts from surgery, medical oncology, radiology, and the endoscopy center. Moving beyond the traditional “one cancer, one treatment” approach, they adopted a strategy of treating distinct diseases simultaneously, proposing an integrated concurrent chemoradiotherapy plan. Taking into account the patient’s multiple underlying medical conditions and personal treatment preferences, the medical team devised a comprehensive treatment plan combining proton therapy and concurrent chemotherapy to precisely target both primary cancer sites. The specific strategy involved administering curative-intent proton radiotherapy combined with endocrine therapy for the prostate cancer. Simultaneously, the radiation field encompassed the tumor at the rectosigmoid junction and its associated lymphatic drainage areas, accompanied by concurrent chemotherapy; the aim was to shrink the rectosigmoid tumor and downstage the disease, thereby creating favorable conditions for subsequent surgery and increasing the likelihood of a successful curative resection.

“In complex cases like this, the key lies in emphasizing an integrated strategy rather than simply layering treatments,” explained Dr. Luo Yingshan from the Department of Radiation Oncology. “We need to balance the timing of treatments for both cancers against the risk of side effects. Precision technologies like proton therapy allow us to effectively cover multiple target areas while better protecting shared organs at risk surrounding the lesions, providing crucial support for achieving the dual goals of curative treatment and the preservation of quality of life.”

Proton therapy creates a surgical window; postoperative pathology confirms ideal therapeutic efficacy.

As the first proton therapy center in South China to enter clinical operation, the Proton Therapy Center at Guangzhou Taihe Cancer Hospital strictly adheres to the radiotherapy guidelines and standard protocols of MD Anderson Cancer Center, dedicated to providing patients with personalized, cutting-edge treatment plans. The center is equipped with the world-leading Varian ProBeam® proton therapy system and led by authoritative domestic experts; the team possesses extensive experience, having managed thousands of clinical cases in the field of proton therapy.

After completing 28 sessions of proton therapy, Mr. C continued his chemotherapy at Guangzhou Taihe Cancer Hospital. Follow-up imaging three months later showed no signs of activity in his prostate lesion. Meanwhile, endoscopic examination revealed no obvious mass at the rectosigmoid junction, though surgery was still required for definitive confirmation.

Following a comprehensive re-evaluation by the multidisciplinary team, it was determined that Mr. C met the criteria for surgery. A surgical team led by Associate Chief Physician Xie Xiaoming performed a “laparoscopic-assisted radical resection of rectosigmoid junction cancer.” The procedure went smoothly with intraoperative blood loss of less than 10 ml, and the patient recovered well postoperatively. Even more encouragingly, postoperative pathology confirmed that the patient had achieved a pathological complete response (pCR).

Associate Chief Physician Xie Xiaoming further explained: “pCR is tantamount to a clinical cure and represents the ideal goal of neoadjuvant or conversion therapy. It indicates a very low risk of tumor recurrence and a favorable long-term prognosis. This also suggests that this comprehensive treatment model—centered on proton therapy—holds broad clinical prospects for similar cases.”

Today, Mr. C is recovering well and gradually returning to his normal life. This case powerfully demonstrates that when facing the complex scenario of double primary cancers—prostate cancer and rectosigmoid junction cancer—located in close proximity within the pelvic cavity, a personalized, integrated treatment plan formulated by a multidisciplinary team, combined with advanced technologies like proton therapy, can effectively control or cure both cancers, thereby delivering genuine survival benefits and ensuring a good quality of life for the patient.

Guangzhou Concord Cancer Hospital

Woman in 50s bled for a year, then diagnosed with two cancers.

Woman in 50s bled for a year, then diagnosed with two cancers.

A female patient in her 50s, who had been experiencing persistent vaginal bleeding for over a year, sought medical attention at a hospital due to sudden abdominal pain. A pelvic MRI revealed a malignant lesion in the cervix. In search of a better treatment plan, the patient and her family traveled to Guangzhou Taihe Cancer Hospital for further diagnosis and treatment.
Based on the pelvic MRI findings from the previous hospital, the initial diagnosis was highly suspected to be cervical cancer. However, after conducting a thorough physical examination, Professor Chen Jianguo, a specially invited senior expert at the hospital, and gynecologic oncologist Lin Weiwei discovered that although the patient’s cervix was significantly enlarged, the bilateral paracervical tissues were soft in consistency—a finding inconsistent with the typical biological behavior and visual characteristics of cervical cancer. They preliminarily determined that the patient’s condition was not conventional cervical cancer and that there was a possibility of misdiagnosis or missed diagnosis.
To accurately determine the cause, the team performed a diagnostic curettage on the patient and conducted a PET/CT scan along with a full suite of relevant auxiliary tests. Imaging results indicated an intrauterine mass, raising a high suspicion of endometrial malignancy. Subsequently, based on the postoperative pathology results from the diagnostic dilation and curettage and immunohistochemistry data, the uterine lesion was definitively diagnosed as endometrial adenocarcinoma. At the same time, a series of tests further revealed that the patient also had ascending colon cancer, constituting a rare case of dual primary malignancies.
According to clinical imaging data, the patient’s PET/CT scan revealed thickening of the intestinal wall in the upper ascending colon, accompanied by localized intussusception and elevated metabolic activity. Clinical data indicate that intussusception in adults is often caused by intestinal tumors; furthermore, the SUV value of this colonic lesion was as high as 19.5—far exceeding the 2.5 threshold for determining malignancy—indicating significant characteristics of a malignant lesion. Subsequently, the patient underwent pain-free gastrointestinal endoscopy, during which a massive mass was observed in the ascending colon near the hepatic flexure. Pathological biopsy results confirmed a villous-tubular adenocarcinoma, classified as a moderately differentiated adenocarcinoma.

Multidisciplinary Combined Surgery: One-Stop Radical Treatment for Two Lesions

In response to the patient’s particularly complex condition—endometrial cancer combined with ascending colon cancer—the hospital immediately activated its multidisciplinary team (MDT) consultation mechanism. Specialists from the gynaecology, radiology, gastrointestinal surgery, pathology, anaesthesia and medical oncology departments jointly discussed a treatment plan.
The expert panel concluded that both malignant tumours met the criteria for surgery and required radical resection. Although a combined operation would increase the surgical difficulty and prolong the duration of the procedure and anaesthesia, it would spare the patient the trauma of a second operation and maximise her long-term prognosis and personal benefit, making it the optimal treatment plan.
After comprehensive consideration of the patient’s condition and treatment risks, it was decided that surgical treatment would proceed first, with a subsequent adjuvant treatment plan to be formulated based on the pathological results and the patient’s recovery. Subsequently, the hospital’s gynaecological oncology and gastrointestinal surgery specialist teams collaborated to perform a combined surgery, providing the patient with a one-stop radical tumour resection.
The operation was led by Professor Chen Jianguo. The gynaecological oncology team first completed a series of procedures via an abdominal approach, including a near-total hysterectomy, bilateral adnexectomy, omentectomy, pelvic lymph node dissection and para-aortic lymph node dissection. The procedure was then taken over by Dr Xu Hui, an Associate Chief Physician in the Department of Gastrointestinal Surgery, who performed a radical resection of the right half of the colon.
To minimise surgical trauma and reduce the burden on the patient’s post-operative recovery, the radical resection of the right half of the colon was performed entirely via the original gynaecological surgical approach. The position of the original incision was relatively high, which partially obstructed the surgical field of view for the colon surgery and significantly increased the difficulty of the procedure. However, to avoid extending the incision further and causing additional tissue damage, the team performed the entire procedure with precision within the existing incision, completing all surgical steps to the highest standards to ensure the best possible post-operative recovery for the patient.
The entire combined surgical procedure was successfully completed, and the patient’s post-operative condition remained stable. The patient’s family expressed high praise for the hospital’s precise diagnosis and meticulous surgical treatment, acknowledging that it was thanks to the hospital’s professional medical team that not only was the cause of the uterine lesion accurately identified, but a hidden malignant tumour in the colon was also promptly detected, enabling the patient to receive comprehensive, efficient and targeted treatment.

The incidence of multiple primary cancers is low, making them highly prone to misdiagnosis and missed diagnosis

In clinical terms, multiple primary cancers are defined as two or more independent primary malignant tumours occurring in the same patient either simultaneously or sequentially; they are primarily classified into two categories: synchronous multiple primary cancers and asynchronous multiple primary cancers. Specifically, if two or more malignant tumours of different cellular origins are detected within a six-month period, this is classified as synchronous multiple primary cancer, and the patient is considered a typical case of synchronous multiple primary cancer.
According to Dr Zhan Xiangbo, Associate Chief Physician in the Department of Gynaecological Oncology at the hospital, the clinical incidence of multiple primary cancers is extremely low; precisely for this reason, misdiagnosis is highly likely to occur in clinical practice. Once a single primary malignant tumour has been confirmed, clinicians often overlook hidden primary tumours in other sites, frequently misinterpreting multiple primary cancers as distant metastases from a single tumour, which in turn leads to deviations in the treatment plan.
Early, accurate diagnosis and standardised combined treatment of multiple primary cancers are key to ensuring effective treatment outcomes and improving survival rates. The hospital’s clinical team comprehensively reviews the patient’s medical records from other hospitals, as well as imaging and pathology reports. They conduct a precise assessment based on the patient’s individual circumstances and arrange supplementary tests as required. Always prioritising the patient’s best interests, the team develops personalised treatment plans for patients with complex tumours using precise, efficient and cost-effective diagnostic and therapeutic approaches, thereby minimising the risk of misdiagnosis or missed diagnoses and ensuring the safety and efficacy of treatment.

Foshan HeYou International Hospital

NOSES Surgery Saves High-Risk Colon Cancer Patient

High-risk colon cancer patient with multiple co-morbidities successfully saved via multidisciplinary minimally invasive NOSES surgery.

The patient presented with a complex clinical picture involving concurrent gastrointestinal bleeding, complete intestinal obstruction, and hemorrhage from a ruptured intestinal tumor, compounded by multiple underlying conditions such as diabetes, hypertension, and severe pneumonia. The patient also had a history of cardiac arrest and prior ICU admission for critical illness. This combination of complex pathology and multiple high-risk factors posed immense challenges at every stage of diagnosis and treatment. A multidisciplinary team led by Professor Zhang Tiemin from the Department of Gastrointestinal Surgery at Heyou Hospital—collaborating with the Departments of Gastroenterology, Anesthesiology, and Critical Care Medicine (ICU), as well as the nursing team—performed a laparoscopic minimally invasive NOSES procedure (Natural Orifice Specimen Extraction Surgery). This approach enabled the resection of the diseased intestinal segment, relief of the obstruction, and control of the bleeding with minimal surgical trauma. Following two weeks of comprehensive, systematic treatment and care, the patient successfully navigated the perioperative period and was discharged in stable condition.

Acute Gastrointestinal Bleeding: Identifying Critical Intestinal Lesions

The patient was transferred to the Department of Gastroenterology for specialized treatment of gastrointestinal bleeding. In patients with multiple underlying conditions, persistent gastrointestinal bleeding can rapidly exacerbate anemia and disrupt circulatory function—potentially leading to shock—thereby necessitating prompt identification of the cause and targeted intervention.
The gastroenterology team immediately conducted comprehensive examinations, revealing a mass measuring approximately 5×6 cm in the large intestine. This mass had caused severe narrowing and complete occlusion of the intestinal lumen, resulting in a classic complete bowel obstruction; furthermore, ulceration and bleeding from the mass were identified as the primary cause of the patient’s gastrointestinal hemorrhage. Given the patient’s critical condition, the department immediately initiated an emergency transfer protocol, moving the patient to the Department of Gastrointestinal Surgery for further life-saving treatment.

Complications from multiple overlapping conditions make surgical intervention extremely high-risk.

After the patient was transferred to the Department of Gastrointestinal Surgery, Professor Zhang Tiemin, the department head, led a comprehensive assessment of the patient’s condition and organized a multidisciplinary consultation. The medical team determined that failure to promptly relieve the intestinal obstruction would lead to a cascade of severe complications—such as intestinal ischemia, necrosis, perforation, and abdominal infection—which could easily trigger septic shock and pose an immediate threat to life.
The patient presented with underlying conditions including diabetes, hypertension, and severe pneumonia, as well as a history of critical care in the ICU and cardiac arrest. Consequently, the patient’s physiological tolerance for anesthesia and surgery was significantly compromised, carrying a high risk of intraoperative circulatory instability, postoperative infection, cardiopulmonary failure, and poor wound healing. Although the patient fell into the “extremely high-risk” category for surgery, conservative treatment had failed to control the intestinal obstruction and persistent bleeding—conditions that also carried a fatal risk—making surgical intervention the only viable life-saving option.
Professor Zhang Tiemin noted that the key to treating such patients lies in relieving the obstruction, resecting the lesion, and controlling bleeding within the shortest possible time, while simultaneously minimizing surgical trauma to ensure the patient safely navigates anesthesia and the perioperative period.

Customized Minimally Invasive Approach: NOSES Surgery Reduces Treatment Trauma

Given the patient’s high-risk, critical physical condition, Professor Zhang Tiemin’s team tailored a minimally invasive laparoscopic NOSES (Natural Orifice Specimen Extraction Surgery) plan. As a cutting-edge technique in minimally invasive gastrointestinal surgery, this procedure eliminates the need for large abdominal incisions or a dedicated opening for specimen extraction; instead, the diseased tissue is removed via the natural anal orifice, leaving only a few tiny puncture wounds on the body surface.
Compared to traditional surgical methods, NOSES offers significant advantages, including reduced trauma, less intraoperative pain, faster postoperative recovery, and a lower incidence of abdominal wall incision complications. For this high-risk patient—who presented with multiple underlying medical conditions and a history of cardiac arrest—the minimally invasive approach effectively minimized intraoperative blood loss, lowered the risk of postoperative infection, and reduced physiological stress, thereby greatly enhancing the safety of perioperative care.
During the procedure, Professor Zhang Tiemin’s team leveraged their extensive experience in minimally invasive tumor surgery to meticulously dissect tissues and precisely manage blood vessels. They successfully performed a complete resection of the diseased intestinal segment and completed intestinal reconstruction while ensuring minimal trauma and blood loss. The surgery proceeded smoothly, with the patient’s vital signs remaining stable throughout. Postoperatively, only four tiny incisions (0.5–1 cm) remained on the abdomen; this approach significantly reduced the physical impact of the surgery, laying a solid foundation for rapid recovery.

Smooth postoperative recovery; long-term adjuvant therapy proceeding in an orderly manner.

Postoperative pathological analysis confirmed a diagnosis of sigmoid colon adenocarcinoma, with the tumor measuring approximately 8 × 7.5 × 3 cm. Under the meticulous monitoring and systematic clinical management of the hospital’s multidisciplinary medical team, the patient experienced no serious postoperative complications—such as infection or secondary hemorrhage—and showed steady improvement in both physical and mental well-being, ultimately making a successful recovery and being discharged. Moving forward, the medical team will formulate a personalized plan based on the patient’s pathological stage and overall health status to systematically administer adjuvant therapy.

Summary of Expert Diagnosis and Treatment, and Cancer Screening Reminders

The successful treatment of this high-risk, critically ill patient with colorectal cancer was made possible by the hospital’s multidisciplinary team, which ensured a rapid response, precise assessment of the patient’s condition, the formulation of a personalized minimally invasive treatment plan, and standardized perioperative management throughout the entire process.
Professor Zhang Tiemin noted that when treating patients with complex, critical tumors, surgical feasibility cannot be determined in isolation. Instead, a comprehensive approach is required—evaluating the tumor’s characteristics, underlying medical conditions, anesthesia tolerance, cardiopulmonary function, immune resilience against infection, and potential for postoperative recovery—to tailor an optimal, personalized treatment plan that ensures safe and highly effective care.
Experts also emphasize that colorectal cancer is a highly prevalent malignancy; in its early stages, it often presents without typical symptoms and is highly insidious. Individuals over the age of 40—particularly those at high risk due to factors such as a family history of colorectal cancer, chronic or recurrent constipation or diarrhea, blood in the stool, chronic enteritis, a history of intestinal polyps, irregular dietary habits, long-term smoking and alcohol consumption, or obesity—should undergo regular gastrointestinal endoscopic screening. Prioritizing early screening, diagnosis, and treatment is crucial for improving clinical outcomes, avoiding severe complications, and reducing mortality associated with the disease.

globalmedpool

The Five-Year CAR-T Marathon of an 11-Year-Old Girl with Acute B-Cell Lymphoblastic Leukemia

Five years after sequential CAR-T therapy, the pediatric patient has achieved clinical cure—a ray of hope after nine years of waiting.

After undergoing sequential CAR-T therapy, the young patient Xiaoxiao achieved clinical remission and was officially declared free of leukemia—the outcome she and her family had awaited for nine years.

In the immediate aftermath of the CD19 CAR-T cell infusion, no one could predict whether this frail, slight girl would successfully weather the ordeal and make a full recovery.

Diagnosis, chemotherapy, discontinuation of treatment, and subsequent disease recurrence.

Xiao Xiao’s complexion deteriorated and she began crying incessantly for no apparent reason, prompting a visit to a local hospital. Bone marrow cytology and immunophenotyping confirmed a diagnosis of acute B-lymphoblastic leukemia (B-ALL); she was just over two years old at the time.

For the next three-plus years, chemotherapy, bone marrow aspirations, and intrathecal injections dominated much of her childhood. Fortunately, repeated bone marrow assessments consistently showed negative results. She completed her chemotherapy regimen, and the family believed the hardest part was over. However, a follow-up bone marrow examination shattered that peace: 25.6% of the cells in her bone marrow were identified as primitive, immature lymphocytes, indicating a full-blown relapse of the leukemia.

To this day, Xiao Xiao’s father vividly remembers the moment he received that follow-up report. The sudden news made him feel, for a time, as though the perseverance of the past few years had been in vain—yet he had no time to give in to despair. He gathered all her medical records and began actively seeking avenues for continued treatment.

Traveling to Beijing amidst the pandemic to seek treatment from Director Pan Jing’s team.

The journey to seek medical treatment across provinces was fraught with obstacles. During a relapse, every day of delay risked a continued increase in tumor burden. Without hesitation, Xiaoxiao’s father took the necessary protective measures and rushed with her from their hometown to Beijing.

At the Department of Hematology-Oncology and Immunotherapy at Beijing Gaobo Hospital, Director Pan Jing’s team meticulously reviewed Xiaoxiao’s entire medical history—spanning her initial diagnosis, the period off medication, and the subsequent relapse—and conducted a comprehensive assessment based on her current physical condition. After thorough consultation with the family, the team determined that Xiaoxiao met the eligibility criteria for CAR-T cell therapy.

“The child’s baseline physical condition is reasonably good; following chemotherapy after the relapse, her tumor burden has decreased, making her a suitable candidate for sequential therapy.” Director Pan’s assessment brought the first sense of relief to Xiaoxiao’s father, easing the anxiety that had been weighing heavily on him. The medical team subsequently devised a treatment plan combining tumor-burden reduction with sequential CD19/CD22 CAR-T cell therapy.

CAR-T is not a single procedure, but a complete, continuous treatment cycle.

The public often mistakenly believes that CAR-T cell therapy consists solely of the cell infusion itself; however, the infusion is merely one component of the entire treatment process.

The comprehensive process begins with a preliminary assessment, during which doctors evaluate the patient’s physical condition, disease progression, and treatment history to determine suitability for CAR-T therapy. This is followed by the formulation and dynamic adjustment of a personalized treatment plan, encompassing key steps such as cell manufacturing and infusion. Post-infusion, patients must manage various risks—including fever, inflammatory responses, infections, and immune reconstitution—while undergoing long-term follow-up to continuously monitor therapeutic efficacy and physical recovery. These stages are interconnected and interdependent; they cannot be viewed in isolation.

For the patient, CAR-T represents a continuous, comprehensive treatment journey rather than a single surgical procedure. The ultimate outcome is rarely determined by the day of infusion alone but is instead shaped by the management of the entire clinical process.

Xiaoxiao first underwent chemotherapy to reduce tumor burden and received FC pre-conditioning, successfully completing the CD19 CAR-T cell infusion. Follow-up assessments showed no abnormal lymphocytes regarding minimal residual disease (MRD) in the bone marrow, and morphological results for both bone marrow and peripheral blood were negative. Subsequently, in accordance with the established plan, she completed the sequential infusion of autologous human-origin CD22 CAR-T cells.

Following the cell infusions, Xiaoxiao experienced fever and a period of bone marrow suppression, and she also contracted COVID-19 during the later stages of the sequential treatment. Amidst the harsh winter of the country’s first major wave of infections, she successfully weathered every challenge. Throughout every fluctuation in her condition, her father remained by her side in the hospital room, keeping watch day and night.

The two cell infusions constitute this comprehensive sequential regimen—a treatment strategy continuously validated in clinical practice by Director Pan Jing’s team. By employing a sequential CD19 CAR-T and CD22 CAR-T approach to treat pediatric relapsed/refractory B-cell acute lymphoblastic leukemia (B-ALL), this regimen significantly reduces both the overall relapse rate and the rate of antigen-negative relapse compared to single-target CAR-T therapies. The interval between the two CAR-T infusions was precisely calculated to ensure the timely administration of CD22 CAR-T while maintaining safety, thereby minimizing the likelihood of the tumor developing immune escape via target antigen loss.

End-to-end medical support and the father who kept a long, steadfast watch.

As cell therapy becomes increasingly widespread, a distinct pattern has emerged: even when the same technology is employed, treatment outcomes and patient experiences vary from person to person. These differences largely stem from the implementation phase—specifically, the adequacy of assessments, the stability of the treatment pace, the timeliness of managing adverse reactions, and the consistency of long-term follow-up care.

While these elements may seem straightforward in isolation, in real-world clinical practice, they often overlap and influence one another. What patients choose is not merely a medical technology, but a comprehensive set of capabilities ensuring a smooth treatment process: a robust risk-stratification system, a stable and fully implemented end-to-end treatment pathway, and extensive clinical experience in managing complex complications.

Director Pan Jing leads a team that performs over 200 CAR-T therapy procedures annually for pediatric patients with relapsed or refractory lymphoblastic leukemia, achieving outcomes that rank among the best internationally. In their clinical work, the team focuses not only on technological innovation but also on doctor-patient communication and the cultivation of trust. Director Pan frequently interacts with the families of young patients in the ward, picking up on subtle yet critical details to dynamically refine treatment plans.

Over the course of five years, a father’s devotion has transcended measurement by mere medical metrics. From carrying his two-year-old daughter back and forth to the hospital, to seeking help far and wide with a thick stack of medical records after a relapse, and finally traveling to Beijing for treatment—through bone marrow aspirations, cell infusions, and the constant monitoring of every fever—he has never once been absent. Along this arduous medical journey, the father, once a young man, has seen his hair turn completely white.

A five-year milestone: reaching the peak of healing.

It has been five years since Xiaoxiao completed her sequential CAR-T therapy. By clinical standards, she is officially free of leukemia and considered clinically cured, no longer requiring routine follow-ups. Her name has been inscribed on the “Peak of CAR-T Cure” roster at the Department of Hematology-Oncology and Immunotherapy at Beijing Gaobo Hospital, signifying sustained complete remission.

Now 11 years old, Xiaoxiao has gradually caught up with her peers in height and weight; she attends school normally and plays with friends on weekends, and her family has regained their smiles.

Xiaoxiao’s father occasionally looks back at old photos from her hospital days—pictures showing a little girl in a face mask and a younger version of himself with dark hair. Contrasting this with the present—where his daughter runs and plays in the living room while his own hair has turned completely white—he feels no regret.

“Let it turn white; it was worth it.”

As Director Pan Jing has noted, for children with blood disorders, the illness is merely a difficult trial in life; once they overcome it, they can still enjoy a healthy childhood. For Xiaoxiao’s family, this milestone means far more than just the label “clinically cured”—it represents the family’s successful journey through a five-year marathon to reclaim their ordinary, happy life.

Shulan (Hangzhou) hospital

Capsule-sized pacemaker helps elderly man with slow heartbeat.

A normal resting heart rate for an adult ranges from 60 to 100 beats per minute; rates that are too fast or too slow are considered abnormal and can compromise heart health. When the heart rate drops below 50 beats per minute, individuals are highly susceptible to symptoms such as dizziness, fatigue, and shortness of breath. Sudden, unexplained fainting may occur, and in severe cases, the condition can trigger cardiac arrest or lead to sudden death, posing a critical risk.
Mr. Xu (pseudonym), an octogenarian, had long suffered from bradycardia (abnormally slow heart rate). At its lowest, his heart rate was merely 32 beats per minute—far below the normal range and effectively half the speed of a healthy heart. Seeking a solution to his cardiac issues, Mr. Xu visited Shulan (Hangzhou) Hospital. After careful research and comparison, he opted for the implantation of a minimally invasive, convenient leadless pacemaker—a “capsule” device—to restore vigorous function to his aging heart.
Sudden Discomfort Reveals Serious Heart Condition
More than a month prior to his admission, Mr. Xu had begun experiencing significant physical distress, including frequent dizziness and nausea; he even nearly fainted, and his overall physical condition deteriorated rapidly. Upon noticing these alarming symptoms, his family immediately took him to Shulan (Hangzhou) Hospital for an examination.
Detailed tests, including an electrocardiogram (ECG), confirmed that Mr. Xu was suffering from an old inferior wall myocardial infarction, sinus bradycardia, and third-degree atrioventricular block. These findings indicated a severe heart rhythm disorder and significant impairment of cardiac conduction. He faced an imminent, life-threatening risk of cardiac arrest, necessitating urgent hospitalization and intervention; permanent pacemaker implantation was identified as the most effective treatment.
After researching the condition, the family confirmed that pacemaker implantation was the standard, appropriate treatment. However, given Mr. Xu’s advanced age and underlying conditions—such as hypertension and coronary heart disease—his physical tolerance was limited, and the family was deeply concerned about the risks associated with traditional pacemaker surgery. Traditional Pacemakers vs. Capsule Pacemakers: A Clear Comparison of Pros and Cons
【Traditional Pacemakers】
Traditional pacemakers are roughly the size of a matchbox. Implantation requires a skin incision to create a subcutaneous pocket for the device body; leads (wires) are then connected to the device and implanted into the right atrium, right ventricle, or left ventricle to provide pacing.
For elderly patients with low immunity or underlying medical conditions, this procedure involves a large incision and external leads. Post-operative complications—such as pocket infections, lead abrasion, or lead dislodgement—are common, and the recovery period is long, posing various risks.
【Leadless Capsule Pacemakers】
Compared to traditional devices, this new pacemaker represents a “breakthrough technology” in cardiac intervention with significant advantages: it is the size of a small capsule and weighs less than 2 grams. It requires no leads, no skin incisions, and no subcutaneous pockets, thereby eliminating the root causes of post-operative infections and lead-related complications.
The procedure does not require general anesthesia. Doctors create a minimally invasive access point via the femoral vein to precisely implant the miniature capsule pacemaker into the trabeculae of the right ventricle. It utilizes the body’s own local electrical pathways to provide stable pacing, resulting in minimal trauma and high procedural efficiency.
Mr. Xu’s family stated that after comparing the pros and cons, they decisively chose the capsule pacemaker for him. The surgery went smoothly, and he was discharged after just two days of recovery. The family expressed their pleasant surprise that a once-dangerous heart condition could now be resolved easily and safely thanks to advanced medical technology.
Smart Adaptation: Maximizing the Advantages of the Miniature Pacemaker
According to medical staff, the leadless capsule pacemaker is not only minimally invasive and safe but also features powerful smart capabilities, allowing it to precisely adapt to the patient’s heart rhythm. The device autonomously senses the patient’s intrinsic heart rate in real time: when the heart rate exceeds the programmed minimum pacing rate, the device automatically enters a standby sensing mode without delivering active pacing pulses, thereby aligning with the heart’s natural rhythm; conversely, when the heart rate drops below the safety threshold, the device immediately initiates pacing to drive a regular heartbeat, ensuring the heart rate remains within safe limits and maintaining stable cardiac blood flow.
Furthermore, the pacemaker features an MRI-compatible mode, offering exceptional versatility. Should a patient require an MRI scan in the future, this mode can be activated directly without the need to remove the device; this effectively resolves the long-standing issue where patients with traditional pacemakers were unable to undergo MRI examinations, greatly enhancing convenience for future medical care and health check-ups.

https://globalmedpool.com

A massive 20-centimeter abdominal tumor was discovered during the third trimester of pregnancy; a final letter was written before entering the operating room. This high-complexity surgery reveals the human side of medicine.

At 32 weeks of gestation, Afang was eagerly awaiting the arrival of her second child and carefully preparing maternity supplies. She experienced no pain or other abnormal symptoms. However, a routine prenatal check-up upended her peaceful pregnancy — imaging revealed a massive abdominal tumor nearly 20 centimeters in size.

Stunned by the unexpected lesion, Afang was transferred immediately to the Department of Obstetrics, The First Affiliated Hospital of Xiamen University to maximize the safety of her unborn baby.

Faced with this complex, high-risk case of pregnancy combined with a giant abdominal tumor, Deputy Director of Obstetrics Zhou Ying launched a hospital-wide multidisciplinary team (MDT) consultation. Specialists from the Hepatobiliary, Pancreatic and Vascular Surgery, General Surgery, Radiology, Oncology, Neonatology, Anesthesiology and Operating Room, Blood Transfusion Department and other departments gathered to formulate a diagnosis and treatment plan.

Two core challenges confronted the medical team: balancing fetal and maternal safety throughout treatment, and determining the optimal timing for cesarean delivery and tumor resection.

After comprehensive evaluation of the patient’s physical condition, fetal development and all test results, the MDT confirmed the stability of both mother and fetus. A phased plan was adopted: continue pregnancy under close monitoring, with a timely elective cesarean section if needed, to avoid risks brought by premature surgery.

Using contrast-enhanced abdominal CT, CTA and CTV, Chief Physician Huang Dehao from the Department of Hepatobiliary, Pancreatic and Vascular Surgery made a critical assessment of the tumor. The lesion demonstrated benign expansile growth, merely compressing adjacent structures including the pancreatic head, duodenum and mesenteric vessels, without obvious organ invasion or enlarged lymph nodes. The likelihood of carcinoma was low. It was a mesenchymal tumor, most likely a low-grade lesion such as desmoid tumor or gastrointestinal stromal tumor.

To precisely characterize the lesion and define subsequent treatment, the medical team developed individualized management strategies. Tumor biopsy and genetic testing were scheduled to confirm the pathological diagnosis. Meanwhile, the patient was advised to avoid abdominal trauma to prevent tumor rupture. Gestational diabetes and anemia were corrected, and nutritional support was administered to optimize her physical condition ahead of surgery.

02 Three Life-or-Death Decisions: A Pregnant Woman’s Fight Against Adversity

While the suspected low-grade pathology offered hope, the rare combination of giant tumor and pregnancy forced Afang to confront three agonizing decisions, each bearing implications for maternal-fetal safety and her future life.

Decision 1: Full-term delivery or early termination of pregnancy?

Medically, full-term delivery reduces the risk of preterm complications. The medical team initially recommended continuing the pregnancy until term, followed by radical tumor resection after childbirth. However, considering her condition, Afang insisted on an earlier cesarean section. Eventually, a cesarean delivery was successfully performed at 33 weeks + 2 days of gestation, and the newborn was delivered safely.

Decision 2: Forgo treatment or fight the disease actively?

Watching the fragile newborn in the incubator, with another two-year-old child at home, Afang was overwhelmed by fear of surgical risks and worries about her children. She once considered abandoning treatment. The asymptomatic tumor and her two young children plunged her into severe anxiety and distress.

Dr. Huang Dehao repeatedly explained her condition to ease her concerns. He clarified that this tumor was not incurable and that curative radical surgery could achieve clinical remission. With professional counseling and encouragement from the medical team, Afang overcame her mental burden and resolved to receive treatment. Pursuing treatment was not only a chance for her own survival but also an example of courage for her young children.

Decision 3: Radical surgery — trade-off between organ preservation and surgical difficulty?

One month after delivery, Afang completed tumor biopsy and genetic testing. The pathological diagnosis confirmed a low-grade fibroblastic neoplasm, invasive fibromatosis (desmoid tumor). Complete radical resection of the tumor was identified as the optimal treatment.

To tackle this complex lesion and finalize the surgical plan, Professor Jiang Nan, Director of the Hepatobiliary, Pancreatic and Vascular Surgery Department, led a preoperative multidisciplinary discussion. Multiple contingency plans were devised for potential intraoperative emergencies.

Given the tumor’s dense adhesion to the pancreatic head and duodenum, two drastically different surgical approaches were considered:

  • Option 1: Pancreaticoduodenectomy combined with tumor resection. This approach was technically simpler with lower intraoperative risk, yet required extensive organ removal. The patient would face long-term complications from gastrointestinal reconstruction, severely compromising her lifelong quality of life.
  • Option 2: Tumor resection plus partial resection of the pancreatic uncinate process. This demanded extremely high surgical precision and carried elevated intraoperative risks, including life-threatening biliary fistula, pancreatic fistula and duodenal fistula. However, it maximized preservation of native organs and protected the patient’s long-term quality of life.

Upholding the principle of prioritizing the patient’s long-term benefits, the medical team declined the simpler procedure and chose the more technically demanding option that served the patient best.

03 A 6-Hour Precision “Bomb Disposal”, 12 Hours of Vigil for Survival

On December 31, 2024, this high-risk radical abdominal tumor resection commenced. Intraoperative exploration verified that the tumor measured nearly 20 cm in length, originating from the posterior margin of the pancreatic uncinate process. Expansile growth caused the main superior mesenteric vein to be encased and invaded by the tumor, rendering the procedure far more challenging than standard tumor operations.

Two major technical hurdles emerged during surgery. First was delicate tumor dissection. The huge tumor stretched the descending and horizontal segments of the duodenum tightly with minimal dissectable space. Surgeons used fine scissors for meticulous sharp dissection, peeling the tumor away bit by bit while preventing injury to adjacent organs.

Second was management of the involved major vessel. The invaded main superior mesenteric vein serves as the primary drainage vessel for abdominal viscera. A palliative dissection to spare the vein would reduce immediate intraoperative risk yet leave residual tumor, sharply increasing the chance of postoperative recurrence. To achieve complete resection and eliminate recurrence risks, the team made the decisive call to resect the involved main superior mesenteric vein en bloc with the tumor.

To avoid fatal complications such as intestinal congestion, thrombosis and organ necrosis after venous resection, the surgical team designed a refined vascular reconstruction plan based on preoperative 3D reconstruction and imaging data. The vein was transected at a precise site to preserve intestinal collateral vessels. End-to-end anastomosis was performed between the distal superior mesenteric vein and the stump of the Henle trunk. Concurrent procedures including duodenal repair and jejunostomy for enteral nutrition were completed successfully.

The core resection lasted six hours. Including anesthesia and preoperative preparation, the patient remained in the operating room for 12 hours. Fully aware of the surgical risks, Afang wrote her will before entering the operating theatre, proceeding with the procedure in the face of potential death. Outside the operating room, her family endured an agonizing overnight wait.

04 Medical Expertise Carries Human Compassion: Rebirth from Despair Shows the Original Aspiration of Physicians

Thanks to seamless coordination and precise manipulation of the MDT, the demanding surgery was completed successfully. Postoperatively, the medical team implemented a personalized rehabilitation regimen with anticoagulation, parenteral and enteral nutrition, and enhanced recovery protocols to facilitate recovery.

Only a mild pancreatic fistula occurred, which healed fully with adequate drainage. No severe fatal complications such as biliary fistula, duodenal fistula or superior mesenteric venous thrombosis developed. Afang was discharged more than ten days after surgery. Before discharge, she presented a silk banner to the entire hepatobiliary, pancreatic and vascular surgery team to express gratitude for their dedication.

This high-risk, complex case of radical resection of a giant tumor in late pregnancy demonstrates the strengths and humanistic warmth of modern medicine in three aspects:

  1. Powerful multidisciplinary collaboration. Obstetrics, surgery, anesthesiology, radiology, pathology, neonatology and other departments collaborated seamlessly to resolve the complicated pregnancy-associated tumor challenge beyond the capacity of a single specialty, protecting both mother and infant.
  2. Evolving philosophy of precise minimally invasive care. Departing from the traditional model of overtreatment and aggressive organ removal, the team adopted the surgical principle of “minimal effective intervention and maximum functional preservation”, removing the lesion while safeguarding organ function and long-term quality of life.
  3. The sense of responsibility rooted in medical benevolence. Rejecting the safer, easier surgical route, the medical team voluntarily took on the highly demanding procedure to pursue the best long-term prognosis for the patient, embodying the creed of compassionate and skilled medical practice.

Life rarely follows a smooth path, and misfortune can strike suddenly. Afang’s recovery represents the perseverance of a brave mother. It also stands as testimony to physicians guarding lives with sharp scalpels and compassionate hearts. Superb medical skills fight disease, and humane care heals the soul. This is the most touching face of medicine.

Disclaimer: This is a real clinical case for science popularization. Individual conditions vary greatly. Do not self-diagnose based on this article. Seek care at a formal hospital for any health concerns.

Five-year recovery following transplantation for Ph-positive acute lymphoblastic leukemia

Breaking down regional barriers! Two major medical institutions from Tianjin and Beijing are jointly establishing a pancreatic tumor center to tackle the “king of cancers.”

The Fight Against Blood Disease Is Never a Solo Battle: A Story of Doctor-Patient Unity and Family Devotion

The battle against blood diseases is never a solitary fight—it is a prolonged war fought together by doctors, patients, and their families, united in heart and purpose. The lengthy treatment cycles, recurring fluctuations in condition, and rigorous rehabilitation care test not only the patient’s physical endurance but also a family’s original resolve and perseverance. At Gaobo Shanghai Zhanxin/Liquan Hospital, countless families have used love as their armor and trust as their bridge, standing shoulder to shoulder with medical teams against illness. This March, 63-year-old Uncle Xu successfully reached the significant milestone of five-year sustained complete remission (CR5) after transplantation for Ph-positive acute lymphoblastic leukemia, triumphantly completing a seven-year life breakthrough.

A Sudden Serious Illness and a Bumpy Initial Treatment Journey

Looking back to 2019, a peaceful life was completely shattered by an unexplained illness. At that time, Uncle Xu frequently experienced persistent headaches and unexplained low-grade fever, with his overall health steadily declining. After multiple examinations, he was diagnosed in April of that year with Ph-positive B-cell acute lymphoblastic leukemia (Ph⁺ B-ALL). This devastating diagnosis plunged the entire family into shadow.

After diagnosis, Uncle Xu immediately began chemotherapy, but the treatment journey proved far more difficult than anticipated. During chemotherapy, he unfortunately developed severe pulmonary fungal infection, accompanied by pleural effusion and other serious complications. His physical tolerance dropped sharply, and the established treatment plan had to be suspended. The sudden turn of events and the stalled treatment left the family anxious and helpless. Seeking a more precise and systematic treatment plan, the family took Uncle Xu to multiple hospitals before finally arriving at the Hematology Department of Shanghai General Hospital, where a professional hematology team re-evaluated his condition and planned subsequent treatment.

In early 2020, recognizing the team’s professional expertise, Uncle Xu followed Professor Wang Chun’s team to the newly opened Gaobo Shanghai Zhanxin Hospital for specialized treatment. Based on Uncle Xu’s specific condition, physical status, and genetic characteristics, the medical team tailored an individualized comprehensive treatment plan, adopting a precision treatment model combining chemotherapy with targeted therapy, dynamically monitoring leukemia fusion gene changes throughout the process, and precisely controlling the treatment rhythm. After multiple cycles of standardized treatment, Uncle Xu’s condition was effectively controlled, and his various health indicators gradually improved, laying a solid foundation for subsequent treatment.

Relapse in Desperation: Transplantation Builds Hope for Rebirth

Just as his condition was steadily improving and the family saw the dawn of recovery, in August 2020, Uncle Xu suddenly developed facial swelling and pain and general discomfort. The follow-up results brought devastating news—the disease had relapsed. At that time, the disease was progressing rapidly, and conventional treatment could no longer control the lesions. How to stop the deterioration and fight for long-term survival became the core challenge facing both doctors and patient.

After comprehensively evaluating Uncle Xu’s relapse situation, age and physical signs, and previous treatment history, Professor Wang Chun’s team determined that allogeneic hematopoietic stem cell transplantation was the core and critical approach to achieve long-term disease-free survival and completely cure the disease. To provide a safety net for his life, the hospital immediately initiated the matching process. With the support of the China Marrow Donor Program’s resources, a suitable healthy donor was successfully matched for Uncle Xu.

In February 2021, Uncle Xu successfully underwent allogeneic hematopoietic stem cell transplantation. Under the meticulous monitoring of the medical team, he smoothly passed through the critical post-transplant period and was successfully discharged from the sterile ward. For Uncle Xu’s family, who had endured life-and-death trials, the success of the transplant was not only a turning point in his condition but also a new starting point on a long road to recovery. A protracted battle of perseverance and patience had officially begun.

Daily Care and Companionship: Meticulous Nursing Through a Long Recovery

Recovery after hematopoietic stem cell transplantation is a long and rigorous test. After surgery, Uncle Xu experienced various transplant-related complications including oral mucosal damage and recurrent diarrhea. His immune system was extremely compromised, and even the slightest infection could trigger serious risks. The recovery process was full of thorns.

To help the patient recover steadily, the hospital’s medical team followed up throughout the process with dynamic interventions. Based on Uncle Xu’s complications, intestinal function, physical strength, and immune indicators, they continuously optimized the treatment plan, adjusted anti-infection, symptomatic support, and nutritional intervention strategies, helping him step by step repair his bodily functions and rebuild his immune system.

During the years of home-based rehabilitation outside the hospital, his wife Aunt Dai became Uncle Xu’s most solid support. Through seven years of daily companionship, she shouldered all the caregiving responsibilities, strictly following the rehabilitation guidance of the medical team. Day after day, she carried out comprehensive home disinfection, meticulous dietary management, and regular schedule management, precisely avoiding various infection triggers. From food selection and nutritional conditioning with small frequent meals, to daily vital sign monitoring and emotional support, to regular follow-up visits regardless of weather conditions, Aunt Dai built the warmest rehabilitation harbor for Uncle Xu with extreme care and patience, using companionship to withstand the long suffering of illness.

Five Years of Sustained Remission: Doctor-Patient Unity Witnesses the Power of Rebirth

Time speaks not, but perseverance eventually echoes. After years of standardized treatment, meticulous nursing, and long-term follow-up management, Uncle Xu’s physical functions steadily recovered, his immune function was completely rebuilt, and his condition remained stable. He successfully achieved the clinical gold standard of five-year complete remission after transplantation, achieving clinical cure.

At the hospital’s exclusive rehabilitation commemoration ceremony, Uncle Xu solemnly received the rehabilitation badge symbolizing new life. This small badge carries five years of life-and-death perseverance, over seven hundred days and nights of meticulous care, and is engraved with the moving power of doctor-patient unity and fighting leukemia together. At the event, Uncle Xu specially presented flowers to his wife, who had never left his side, using a bouquet of blooms to express gratitude for seven years of unwavering companionship through wind and rain.

Speaking of his journey, Uncle Xu was full of emotion: “From the despair of diagnosis, to the helplessness of relapse, to the rebirth through transplantation and steady recovery—it was Professor Wang Chun’s team’s professional treatment, the nurses’ meticulous care, and my wife’s day-and-night vigilance that helped me overcome each challenge and rediscover hope in life.”

From being ravaged by serious illness to rebirth through nirvana, five years of rehabilitation graduation is not only Uncle Xu’s personal miracle of life but also a powerful testament to the strength of precision diagnosis and treatment for blood diseases. It is the warmest interpretation of doctor-patient trust and family love. In the future, Uncle Xu will carry this love and perseverance to restart a peaceful and beautiful new life, continuing to write his own chapter of rebirth through the years.

BeijingGoBroad

Five Years of Complete Remission Post-Transplant for Ph-Positive Acute Lymphoblastic Leukemia: Rebirth Through Love and Perseverance

Blood disorders often involve long treatment courses and complex care. Throughout the journey, patients rely heavily on the unwavering support and companionship of their families. At Gaobo Shanghai Zhanxin/Liquan Hospital, many families walk this path side by side. Among them are Mr. Xu and his wife, Mrs. Dai.

Recently, 63-year-old Mr. Xu celebrated his five-year “graduation” — a milestone of recovery — at Gaobo Shanghai Zhanxin Hospital. In this special moment, he presented a bouquet of flowers to his wife, Mrs. Dai, who had accompanied him through seven years of treatment, expressing his gratitude for her steadfast devotion.

From an Unexpected Diagnosis to Systematic Treatment

Mr. Xu recalled that in March 2019, he visited the hospital due to persistent headaches and unexplained low-grade fever. In early April, he was diagnosed with Philadelphia chromosome-positive acute lymphoblastic leukemia (Ph+ ALL). During chemotherapy, he developed severe pulmonary fungal infection and pleural effusion, forcing treatment to be interrupted. After seeking care at multiple institutions, Mr. Xu came to the Hematology Department of Shanghai General Hospital, where Professor Wang Chun recommended further evaluation of his treatment plan.

In early 2020, Mr. Xu followed Professor Wang Chun to the then newly established Gaobo Shanghai Zhanxin Hospital to continue his treatment. After a comprehensive assessment, the medical team developed a systematic treatment plan, using chemotherapy combined with targeted therapy to control the disease while closely monitoring changes in fusion genes. After a phase of treatment, Mr. Xu achieved a period of good disease control.

A Critical Choice After Relapse

In August 2020, Mr. Xu developed abnormal symptoms including facial pain and swelling. Examinations confirmed that the disease had relapsed. Given the rapidly progressing condition, the medical team determined that allogeneic hematopoietic stem cell transplantation was an important treatment option to pursue long-term remission.

With the help of the China Marrow Donor Program, Mr. Xu successfully found a suitable donor. In February 2021, he completed allogeneic hematopoietic stem cell transplantation and was discharged from the transplant unit smoothly. For both the patient and his family, this represented new hope — but also a longer road to recovery.

Long-Term Recovery After Transplantation

The post-transplant recovery process was far from easy. Mr. Xu experienced complications including oral mucosal damage and diarrhea, requiring close medical observation and meticulous care. The medical team continuously adjusted treatment and nutritional support plans based on his condition, helping him gradually restore intestinal function and physical strength.

Throughout the recovery process, Mrs. Dai took on the primary caregiving responsibilities. From disinfecting the home environment to managing his diet, she strictly followed the guidance of the medical team to minimize the risk of infection. Through long-term standardized management and regular follow-up visits, Mr. Xu’s condition gradually stabilized, and his immune function steadily recovered.

Five Years of Recovery, Restarting Life

After years of continuous follow-up and health management, Mr. Xu has now reached the five-year post-transplant recovery milestone. At a recovery commemorative ceremony held at the hospital, he received an important badge symbolizing his recovery.

Looking back on his treatment journey, Mr. Xu expressed heartfelt gratitude to the medical team: “From diagnosis to transplantation, and through long-term follow-up, the doctors and nurses have always been by our side. It is their professional treatment and meticulous care that have allowed me to reach this day, step by step.”

For Mr. Xu and his family, this badge not only records a difficult yet determined treatment journey — it also bears witness to the power of doctors and patients working together to overcome illness.

Beijing GoBroad

Beijing Jingdu Children’s Hospital — The lighting at Beijing Jingdu Children’s Hospital

The Eternal Light in the Corridors of Beijing Jingdu Children’s Hospital

The corridors of Beijing Jingdu Children’s Hospital are always lit. The lights are neither bright nor dim, much like the expressions of the medical staff in white coats — not overly joyful, nor overly sorrowful, simply shining calmly, deep into the night and at dawn.

When the son was first admitted, the family was filled with anxiety. They traveled more than eight hours nonstop by ambulance from the ICU in Shenyang to Beijing. The son was critically ill all the way, and their hearts were heavy. Hospitals always bring to mind sickness and suffering, especially children’s hospitals. Those tiny bodies wrapped in oversized patient gowns looked even more fragile. It is still remembered clearly that they arrived at the hospital at around four o’clock in the early morning amid sleet. Dr. Lü Linlin was already waiting downstairs. Her warm smile instantly eased all their exhaustion from the long journey, warming their hearts like winter sunshine.

During each ward round, Dr. Lü would bend down and speak softly to the son. She did not only ask about his condition, but chatted about his favorite cartoons and toys. It made the family feel she was not a distant doctor. She truly loves children and treats patients with the warmth of family.

Director Liu Zhouyang also won their full recognition for his professionalism. No matter how many questions the parents raised, Director Liu answered them patiently. However busy or tired he was, he never grew impatient. He was always positive, encouraging them, pointing out the way forward and filling the family with strength.

The nurses are remarkable. They seem to have a special instinct to sense a child’s unease before tears start flowing. Once, the son trembled with fear before a blood draw. A round-faced nurse pulled a sticker out of her pocket. “Look,” she said, “this is a glowing star for you. It’s asleep now, but it will light up once we finish the blood test.” The son was skeptical, yet he stopped struggling. After the blood draw, the nurse stuck the sticker on the back of his hand. Held up to the light, the star glimmered softly. The son stopped crying and smiled. Standing there, the family felt tears well up in their eyes.

Days in the hospital dragged on. In the daytime, sunlight streamed through the curtains and drew bright lines across the ward floor. When night fell, the corridor lights took over from the sun. The family often watched night-shift nurses make rounds quietly. They walked almost soundlessly, like soft clouds drifting along the corridor.

One night, the son had a persistent high fever and shivered nonstop. Dr. Dili rushed to the ward immediately. She treated the son professionally and taught the family how to monitor his condition and what to do right away when chills occurred. The family was deeply touched.

When they first entered the transplant unit, the family struggled to adapt. The son’s crying made the parents anxious, irritable, emotionally unstable and unable to sleep. They would pace back and forth inside the unit. Dr. Lü Linlin and Dr. Meng Shuangshuang always comforted them, talked with them and helped relieve their stress as family members. Dr. Meng’s cheerful personality inspired them. Gradually, they became less anxious and negative, and their mood improved.

During every ward round in the transplant unit, the parents asked Director Liu, Dr. Lü and Dr. Meng many questions and described all the son’s symptoms. Their replies were reassuring, strengthening the family’s faith that the son would recover.

Nurses in the transplant unit are also very kind. Despite their heavy workload, they work in orderly fashion under Head Nurse Yang Xinxin. They treat every child as their own, speaking gently to them. When children cry inconsolably, they are more patient than the parents are. They soothe and encourage the kids: “We will fight this illness. We will beat it!”

The nurses comfort children and give them small gifts and toys. The family’s eyes grew moist, yet their hearts were filled with warmth. When the son fell asleep, a nurse spotted the family, smiled softly and put her finger to her lips. At that moment, the family understood why the lights in this hospital never go out. They shine for these night watchers, for those gentle souls who stay awake in the dark.

On the day the son was discharged, the sunshine was beautiful. Doctors and nurses came to say goodbye. As they walked out of the hospital gate, the son suddenly turned back. “What is it?” the parent asked. “That light,” he said, pointing to a window upstairs. “It’s still on.”

Yes, the light keeps shining. It burns for the next sick child, for the next sleepless night. Not all lights in Beijing Jingdu Children’s Hospital will ever go out. Like a steady lighthouse in the vast ocean, it guides lost ships, brings light to dark dawns, and illuminates the hearts of every patient family.

Beijing GoBroad

Beijing Jingdu Children’s Hospital — The Road to Rebirth: A Lifesaving Relay for a Child with Ultra-Severe Aplastic Anemia

Ten Years: 3,650 Days, 87,600 Hours

Time flows quietly amid the tick of stethoscopes. Over the ten years since Beijing Jingdu Children’s Hospital was founded, it has walked hand in hand with countless families. It safeguards children’s health with expertise and warms their growth with compassion. The laughter in hospital wards, heartfelt conversations in consulting rooms, and tears of joy during recovery have all turned into precious memories, etched deep in the corridor of time.

Today, let this album of memories be opened, and a story shared by a patient’s family be read.

This is an ordinary family. Their son was just like any other child — innocent, lovely and well-behaved. They had no grand wishes, only hoping he would stay healthy and grow up quickly. Yet fate took their happiness away.

In October 2022, their nine-year-old son was diagnosed with very severe aplastic anemia. The family plunged into despair, teetering on the brink of loss. After his diagnosis, they traveled back and forth between Tianjin and Harbin. He received ATG therapy and traditional Chinese medicine treatment, requiring constant transfusions of red blood cells and platelets. Sometimes they rushed from hospital to hospital just to secure platelet transfusions. Seeing the bleeding spots all over his body while unable to get platelets, the parents felt as if their hearts were being cut with a knife. They wished they could take his suffering upon themselves. Back then, they felt helpless, with nowhere to turn.

More than a year passed, yet the son’s condition did not improve — it grew worse. His platelet count would drop to single digits every four or five days. Transfused platelets triggered severe allergic reactions: his whole body broke out in an itchy rash accompanied by fever. Bone marrow transplantation became the only option. Through a friend’s recommendation, they came to Beijing Jingdu Children’s Hospital.

They chose Jingdu Children’s Hospital for two reasons: it had an excellent reputation and skilled medical team, plus available isolation beds. Their son could enter the transplant unit just one week after admission, which was critical for his urgent transplant. They were admitted to Ward 8. Dr. Gao Chongfeng, a young and approachable male doctor, received them. Their attending physician was Dr. Lü Linlin, a kind and accomplished female doctor. Their brief interactions with them greatly boosted their confidence that the transplant would succeed. They always spoke gently and cared deeply about how the family felt.

The family was terrified about bone marrow transplantation. Before their son entered the transplant unit, the parents went to see Director Liu Zhouyang. Director Liu patiently explained why transplantation was necessary, what complications might arise during treatment and how they would be managed. He explained everything in great detail and answered all their questions tirelessly, completely easing their fears. They had never received such thorough care at other hospitals. It was remembered how fortunate they were to meet such a thoughtful doctor.

Pre-transplant examinations for the son and the father went smoothly. The son entered the transplant unit with his mother by his side, while the father began preparations to donate bone marrow. He received two mobilization injections and one blood test every day. Over more than a year of anxiety and stress, his weight dropped from over 80 kilograms to 70 kilograms. He barely slept each night. On the day of the bone marrow donation, he fainted at the nurses’ station, startling the nurses. Thankfully, he regained consciousness quickly. All he could think about was not delaying the donation for his son. When Dr. Lü learned he had fainted, she checked on him with great concern. During the bone marrow collection procedure, she suggested the anesthesiologist put him under general anesthesia. He slept through the whole process and woke up when the collection was finished. The family remains deeply grateful to Dr. Lü for her thoughtfulness and care for family caregivers. To be honest, they had grown accustomed to poor attitudes from medical staff at other hospitals while seeking treatment. But here at Jingdu, every doctor and nurse they met was kind and courteous. This is the humanistic care of Jingdu Children’s Hospital.

While in the transplant unit, their son received meticulous care from the nurses. They were highly professional and thorough. They sorted out all his medications and handed them directly to the mother, leaving the family with no extra worries. After transplantation, their son recovered well. His blood cell counts gradually rose. They no longer had to scramble from hospital to hospital begging for blood transfusions. The feeling was indescribable — a joy of surviving a disaster.

More than a month after entering the unit, their son was discharged from the transplant unit and moved to a regular room in Ward 8. As they counted down to their homecoming and imagined family reunion, he developed a complication: thrombotic microangiopathy (TMA). His blood cell counts plummeted again, and he needed blood and platelet transfusions once more. It felt like the sky had fallen. The parents could barely eat for days. At this difficult time, Director Liu and Dr. Lü explained the complication and treatment plan to them, encouraging them not to lose hope and telling them their son would recover.

President Sun Yuan led directors and doctors on ward rounds every Tuesday. She checked on every child’s condition, discussed treatment plans with the medical team and closely monitored disease progress. For their son’s case, President Sun, Director Liu and Dr. Lü developed an effective treatment plan. As treatment continued, their son’s condition improved. Bleeding spots on his body faded away. Dr. Lü, their attending physician, and Dr. Meng Shuangshuang, the resident doctor, kept a close eye on him. The boy often had nosebleeds, and the two doctors would rush to the ward immediately. They used gelatin sponges to stop the bleeding and pressed his nasal alae nonstop, sometimes for over twenty minutes until bleeding fully stopped, even when their arms grew sore. The family felt guilty for troubling them, yet they never complained or showed impatience. Under the dedicated care of the medical team, their son kept getting better. Seeing him recover, the president, directors, attending and resident doctors all wore relieved smiles.

It has been over a year since the transplant. Their son’s blood work is mostly normal, and his physical strength continues to improve.

The medical staff at Jingdu Children’s Hospital are the saviors of this family. They gave their son a second life. This hospital boasts not only outstanding medical expertise but also heartfelt service. The family feels so lucky to have met such a wonderful medical team and grateful that they chose Jingdu Children’s Hospital.

Single Port Gynecologic Surgery in China | Wenzhou Award

Wenzhou People’s Hospital Wins National Award for Single-Port Gynecologic Surgery

Wenzhou People’s Hospital Wins National Award for Single-Port Gynecologic Surgery

On July 31, 2026, Dr. Dong Xiaoxia, Chief Physician of the Department of Gynecology at Wenzhou People’s Hospital and Wenzhou Maternal and Child Health Hospital, won third prize in the national final of the Single-Port Gynecologic Endoscopic Surgery Video Competition.

The award recognizes Dr. Dong’s precise surgical technique, standardized minimally invasive procedures, well-structured academic presentation and strong commitment to patient safety.

The achievement also highlights the growing expertise of Wenzhou People’s Hospital in single-port gynecologic surgery in China, minimally invasive treatment, pelvic floor reconstruction and enhanced recovery after surgery.

A National Platform for Gynecologic Surgical Excellence

The competition was part of the Gynecologic Single-Port Surgery Technology Promotion Program and included preliminary rounds, national semifinals and a final competition.

It was established to provide a national academic exchange platform for gynecologic surgeons and to promote the standardized, high-quality development of single-port endoscopic surgery.

Participants included experienced gynecologic surgeons from leading tertiary hospitals across China. The judging panel consisted of nationally recognized specialists in gynecology and minimally invasive surgery.

Each surgical video and presentation was evaluated according to several criteria, including:

  • The complexity of the surgical case
  • Clarity of anatomical structures during surgery
  • Standardization and precision of surgical techniques
  • Protection of surrounding blood vessels and organs
  • Implementation of enhanced recovery after surgery
  • Logical structure and clarity of the video presentation

Precise, Minimally Invasive and Safe Surgery

With guidance from Professor Li Renliang, Head of the Department of Gynecology, and support from the entire medical team, Dr. Dong Xiaoxia was selected to represent the department in the national competition.

She submitted three carefully selected surgical videos covering several advanced single-port procedures, including:

  • Transumbilical single-port total hysterectomy
  • Transvaginal natural-orifice endoscopic surgery
  • Extraperitoneal sacrocolpopexy for pelvic organ prolapse

The videos clearly demonstrated detailed anatomical identification, controlled tissue separation and advanced single-port endoscopic skills.

One of the cases involved a complex vascular variation. During the procedure, Dr. Dong carefully identified the abnormal vascular anatomy and completed the operation while minimizing the risk of injury to nearby blood vessels.

Her performance reflected the department’s commitment to three important principles:

Precision, minimally invasive treatment and patient safety.

Advanced Gynecologic Care at Wenzhou People’s Hospital

The Department of Gynecology at Wenzhou People’s Hospital is a nationally recognized specialty and a regional center for gynecologic diseases in southern Zhejiang Province.

It is also a key provincial and municipal discipline, a standardized residency training center and a recognized medical specialty in Wenzhou.

Single-port laparoscopic surgery is now widely used within the department and covers most surgical treatments for benign gynecologic diseases. It has become one of the department’s preferred minimally invasive approaches for suitable patients.

The department is also actively developing robotic gynecologic surgery.

Its medical team has completed several innovative procedures, including:

  • China’s first single-port robotic repair of a cesarean scar diverticulum
  • The world’s first gasless transvaginal single-port robotic ovarian teratoma cystectomy

These achievements reflect the department’s accumulated experience in minimally invasive gynecologic surgery and its growing influence in the region.

Comprehensive Cervical Cancer Prevention and Treatment

Wenzhou People’s Hospital established the first integrated cervical cancer prevention and treatment clinic in Wenzhou.

The clinic combines:

  • Cervical cancer health education
  • HPV vaccination
  • Precision cervical cancer screening
  • Artificial intelligence-assisted colposcopy
  • Multidisciplinary cancer treatment
  • Digital follow-up and referral management

In 2024, the clinic was recognized as a municipal model under the Healthy Wenzhou Action Program.

The gynecologic oncology team provides standardized and individualized treatment for cervical cancer and other gynecologic tumors.

For suitable patients with early-stage cervical cancer, the team may provide fertility-preserving surgery. Other available approaches include nerve-sparing radical surgery, chemotherapy, radiotherapy, immunotherapy and targeted therapy.

Postoperative rehabilitation services also include nutritional support and psychological guidance, helping patients improve both treatment outcomes and quality of life.

Specialized Pelvic Floor Rehabilitation

The department has been providing pelvic floor rehabilitation services since 2008 and was one of the early medical institutions in China to introduce systematic pelvic floor treatment.

Its services cover conditions such as:

  • Pelvic organ prolapse
  • Female urinary incontinence
  • Vaginal relaxation
  • Postpartum pelvic floor dysfunction
  • Female sexual dysfunction
  • Chronic pelvic pain

In 2023, the hospital became the only pelvic floor dysfunction rehabilitation training base of the Chinese Association of Rehabilitation Medicine in southern Zhejiang.

In 2024, it received approval to establish the Wenzhou Pelvic Floor Rehabilitation Specialty Center.

Expert Introduction: Professor Li Renliang

Professor Li Renliang is Director and Chief Physician of the Department of Gynecology at Wenzhou People’s Hospital and Wenzhou Maternal and Child Health Hospital.

He is also the leader of the hospital’s nationally recognized gynecology specialty and has participated in academic organizations related to gynecologic oncology, endometriosis, reproductive tract reconstruction and uterine diseases.

Professor Li specializes in the diagnosis and treatment of complex gynecologic diseases, including:

Benign and malignant gynecologic tumors

  • Pelvic floor dysfunction
  • Endometriosis
  • Cervical cancer
  • Ovarian cysts
  • Cesarean scar diverticulum

His surgical expertise includes single-port laparoscopy, robotic gynecologic surgery, fertility-preserving cervical cancer surgery, nerve-sparing surgery and sentinel lymph node procedures.

He has published more than 20 academic papers, including eight SCI-indexed studies.

Expert Introduction: Dr. Dong Xiaoxia

Dr. Dong Xiaoxia is a Chief Physician in the Department of Obstetrics and Gynecology at Wenzhou People’s Hospital and Wenzhou Maternal and Child Health Hospital.

She has extensive clinical experience in the treatment of:

  • Uterine prolapse
  • Female urinary incontinence
  • Vaginal relaxation
  • Uterine fibroids
  • Ovarian cysts
  • Endometriosis
  • Chronic pelvic pain
  • Reproductive tract abnormalities
  • Female sexual dysfunction

She specializes in pelvic floor reconstruction, laparoscopic surgery, hysteroscopic surgery and single-port endoscopic procedures.

Dr. Dong holds ten utility model patents and has published more than ten SCI-indexed and Chinese core journal articles.

Her success in the national competition demonstrates both her individual surgical expertise and the strength of the gynecologic medical team at Wenzhou People’s Hospital.

Minimally Invasive Gynecologic Treatment in China

For international patients seeking gynecologic diagnosis, minimally invasive surgery or pelvic floor treatment in China, selecting an experienced multidisciplinary medical team is an important part of treatment planning.

Depending on the patient’s condition, treatment may involve single-port laparoscopy, hysteroscopy, transvaginal natural-orifice surgery, robotic surgery, pelvic floor reconstruction or comprehensive gynecologic oncology care.

Global Med Pool helps international patients communicate with hospitals in China, prepare medical records, request preliminary medical evaluations and coordinate treatment arrangements.

Treatment options and surgical eligibility must always be determined after evaluation by qualified physicians.

Source: Department of Gynecology, Wenzhou People’s Hospital. Original hospital announcement published on August 3, 2026.

Best Hepatitis B Treatment in China| Wenzhou People’s Hospital

Hepatitis B Treatment in China: A Day at Wenzhou People’s Hospital’s Clinical Cure Clinic

Hepatitis B Treatment in China: A Day at Wenzhou People’s Hospital’s Clinical Cure Clinic

Hepatitis B treatment in China is increasingly focused not only on controlling the virus, but also on providing patients with long-term disease management, emotional support and a clearer path toward a healthier life.

At the Hepatitis B Clinical Cure Clinic of Wenzhou People’s Hospital and Wenzhou Maternal and Child Health Hospital, healthcare professionals work closely with patients throughout their treatment journey. From medication guidance and liver monitoring to regular follow-up calls, the clinic demonstrates how professional medical care and human compassion can work together.

Hepatitis B Care Is About More Than Test Results

When hepatitis B is discussed, attention often turns to viral load, liver enzyme levels, hepatitis B surface antigen and liver stiffness.

However, behind every medical result is a patient who may be worried about disease progression, family relationships, social discrimination or the possibility of returning to a normal life.

The hospital’s clinical cure clinic therefore focuses on both medical indicators and the patient’s overall experience. Nurses and physicians help patients understand their condition, follow treatment plans and manage the emotional challenges that may arise during a long course of care.

Supporting Patients Through Long-Term Treatment

For many patients, the clinical management of chronic hepatitis B is not a short process. Treatment and monitoring may continue for more than a year and, in some cases, for several years.

When patients begin a treatment plan involving long-acting interferon or other antiviral approaches, nurses provide detailed guidance on medication use, injection techniques, sterile procedures and important precautions.

Many patients may be administering a subcutaneous injection for the first time. Step-by-step nursing instruction can help them feel more confident and reduce anxiety about continuing treatment at home.

The medical team also recognizes that encouragement matters. A simple explanation or supportive conversation may help patients remain engaged with a long-term treatment plan.

Helping Patients Understand Liver Test Results

Medical reports can be difficult to understand, especially when they include unfamiliar abbreviations and numerical values.

At the clinic, nurses explain liver elastography results in accessible language. Two commonly discussed measurements include:

CAP Value

The controlled attenuation parameter, or CAP value, is used to assess the amount of fat in the liver.

Liver Stiffness Measurement

The liver stiffness value helps doctors evaluate changes associated with liver fibrosis.

Rather than simply giving patients a report, nurses compare current and previous results and explain what the changes may indicate. This helps patients understand their progress and participate more actively in their own healthcare decisions.

A reduction in liver stiffness may be an encouraging sign, but all results must be interpreted by qualified medical professionals together with laboratory tests, imaging findings and the patient’s overall condition.

Follow-Up Care Beyond the Hospital

The clinic’s work does not end when a patient leaves the consultation room.

According to the hospital’s report, nurses contact some patients approximately every four weeks to ask about medication adherence, sleep, side effects and general well-being.

The follow-up team monitors indicators such as:

  • Liver enzyme levels
  • White blood cell counts
  • Hepatitis B surface antigen levels
  • Viral load
  • Treatment-related reactions
  • Emotional and social concerns

These conversations allow the care team to identify difficulties early and provide additional guidance when necessary.

Addressing Misunderstanding and Hepatitis B Discrimination

Some people living with hepatitis B experience misunderstanding within their families, workplaces or communities.

Fear is often caused by limited knowledge about how hepatitis B is transmitted and managed. Patients may therefore need accurate medical information as well as support in communicating with relatives.

The clinic encourages patients and their families to learn from scientific medical guidance rather than relying on fear or misinformation. Healthcare professionals also support patients in rebuilding confidence and maintaining normal social and family relationships.

Reducing hepatitis-related discrimination is an important part of helping patients return to daily life.

A Clinical Cure Clinic Established in 2023

The Hepatitis B Clinical Cure Clinic led by the Department of Infectious Diseases at Wenzhou People’s Hospital and Wenzhou Maternal and Child Health Hospital was officially established in May 2023.

The clinic provides standardized diagnosis and treatment, individualized disease management and whole-course follow-up services for people living with chronic hepatitis B.

The concept of a “clinical cure” generally refers to achieving specific medical outcomes assessed by specialists, which may include sustained hepatitis B surface antigen loss in eligible patients.

However, clinical cure cannot be guaranteed for every patient. Treatment suitability, expected outcomes and possible risks depend on the individual’s condition and must be evaluated by an experienced medical team.

Medical Care With Both Science and Compassion

For patients, receiving an encouraging test result can represent much more than a change in a laboratory value. It may mean renewed confidence, improved family relationships and hope for a healthier future.

The work of the Hepatitis B Clinical Cure Clinic shows that high-quality healthcare involves more than medication. It also requires clear communication, continuous monitoring, individualized management and respect for every patient.

Hepatitis B Treatment in China for International Patients

International patients considering hepatitis B evaluation or liver disease treatment in China may face additional challenges, including language differences, medical record preparation, hospital selection and appointment coordination.

Global Med Pool can assist international patients with:

  • Matching patients with suitable hospitals and specialists in China
  • Organizing and translating medical records
  • Coordinating consultations and hospital appointments
  • Supporting communication with medical teams
  • Providing assistance during the medical journey in China

Treatment recommendations are made by qualified doctors after reviewing the patient’s medical history, examination results and current health condition.

Contact Global Med Pool to learn more about hepatitis B treatment in China and international medical coordination services.

Source: Adapted from a report published by the Department of Infectious Diseases of Wenzhou People’s Hospital and Wenzhou Maternal and Child Health Hospital on July 28, 2026.

Medical disclaimer: This article is for general informational purposes only and does not replace professional diagnosis or individualized medical advice.

Shulan Original Brain Function Map

A Stroke Changed Her Everyday Life

Personalized Brain Mapping Brings New Precision to Stroke Rehabilitation at Shulan Hangzhou Hospital

One evening approximately six months before seeking further treatment, an elderly woman referred to here as Mrs. Chen suddenly became dizzy and collapsed.

She was subsequently diagnosed with an ischemic stroke.

Although emergency treatment helped stabilize her condition, the neurological effects of the stroke continued to affect almost every part of her daily life.

Her right arm could not be lifted normally, and her right hand was unable to grip everyday objects. She walked unsteadily and frequently depended on family members for support. Simple activities such as dressing, eating, and moving around the home became difficult.

Her speech also became less clear, creating additional barriers when communicating with her family.

For Mrs. Chen and those caring for her, the period following the stroke was not only physically demanding but also emotionally challenging.

Stroke Aftereffects Extend Beyond Paralysis

Many people associate stroke rehabilitation mainly with hemiplegia or weakness on one side of the body. However, the effects of a stroke can be much more complex.

Depending on the location and extent of the brain injury, patients may experience:

  • Weakness or paralysis of an arm or leg
  • Numbness or abnormal sensations
  • Impaired balance and coordination
  • Difficulty speaking or understanding language
  • Problems with swallowing
  • Reduced hand dexterity
  • Memory or attention difficulties
  • Fatigue, anxiety, or depression

Every patient presents a different combination of symptoms. For this reason, a rehabilitation program that is effective for one person may not be equally suitable for another.

This individual variation is one of the greatest challenges in post-stroke rehabilitation.

Why Stroke Rehabilitation Can Be Difficult

Movement is controlled by an extensive neurological network involving the cerebral cortex, deeper brain structures, the spinal cord, peripheral nerves, and muscles.

When a stroke damages part of this network, the problem may not be limited to a single muscle or limb. Communication between different brain regions can also become disrupted.

As a result, several functions may be affected simultaneously, including:

  • Voluntary movement
  • Postural control
  • Balance
  • Coordination
  • Fine motor skills
  • Speech and language processing

Conventional rehabilitation remains an essential part of stroke recovery. Physical therapy, occupational therapy, speech therapy, swallowing training, medication management, and secondary stroke prevention can all play important roles.

However, some patients continue to experience significant functional limitations despite undergoing standard rehabilitation.

For these patients, doctors may consider whether additional technologies could be used alongside conventional treatment.

The Importance of Identifying the Right Brain Target

In recent years, non-invasive brain stimulation technologies, including transcranial magnetic stimulation and transcranial electrical stimulation, have increasingly been studied as supplementary approaches for selected neurological and psychiatric conditions.

These technologies are designed to modulate the excitability and activity of specific brain networks without surgery.

One of the most important clinical questions is:

Which area of the brain should be stimulated?

The position and organization of functional brain networks can differ from one person to another. A target based only on a standard anatomical template may not precisely represent an individual patient’s functional brain organization.

This is where personalized brain mapping may offer additional value.

Creating an Individualized Brain Function Map

Near the end of the previous year, Mrs. Chen and her family visited Shulan Hangzhou Hospital to explore further rehabilitation options.

The medical team performed functional magnetic resonance imaging and individualized brain function analysis.

Using these imaging results, doctors created a personalized map of Mrs. Chen’s functional brain networks. The map was then used to help identify potential intervention targets related to her symptoms and neurological condition.

Rather than relying only on a generalized brain template, the medical team could evaluate the patient’s individual network organization and functional connectivity.

This approach may help move neuromodulation planning from experience-based target selection toward more individualized and image-guided treatment.

Reported Improvements During Rehabilitation

Mrs. Chen subsequently received a multidisciplinary rehabilitation program that incorporated individualized neuromodulation planning under medical supervision.

After approximately three months, her family reported several encouraging changes.

Her speech became clearer, making communication with family members easier. The range of movement in her right arm gradually improved, and she regained more control over forearm rotation.

Her affected leg also became stronger. Her walking posture appeared more stable, and she was eventually able to walk for short distances without continuous physical assistance from family members.

These changes represented meaningful progress for Mrs. Chen and her caregivers.

However, stroke recovery varies considerably between patients. One individual’s experience should not be interpreted as a guaranteed outcome for others. Treatment decisions must be based on the patient’s diagnosis, imaging findings, physical condition, rehabilitation stage, and medical history.

What Is Individualized Functional Brain Parcellation?

Individualized functional brain parcellation is an imaging-based method used to identify functional brain regions and networks within an individual patient’s own brain anatomy.

The process commonly uses resting-state functional magnetic resonance imaging, also known as resting-state fMRI.

Instead of assuming that every patient has identical functional boundaries, the technology analyzes the organization of brain networks at the individual level.

The resulting map can be described as a personalized brain function fingerprint.

It may allow doctors and researchers to:

  • Identify individual differences in functional brain organization
  • Evaluate connectivity between different brain regions
  • Study abnormal neurological circuits associated with symptoms
  • Select potential targets for non-invasive neuromodulation
  • Improve the personalization of neurological rehabilitation planning

The technology is intended to support clinical decision-making. It does not replace neurological examinations, conventional imaging, rehabilitation assessments, or multidisciplinary medical judgment.

How Does Functional MRI Detect Brain Activity?

Functional MRI does not directly record electrical signals from individual neurons.

Instead, it measures changes associated with blood oxygen levels in different areas of the brain. This is commonly known as the blood-oxygen-level-dependent signal, or BOLD signal.

When a brain region becomes more active, local blood flow and oxygen use change. Functional MRI detects these changes and helps researchers estimate patterns of functional activity and connectivity.

Doctors can then analyze how different regions of the brain interact and whether certain functional networks appear disrupted.

For stroke patients, this information may help identify brain regions associated with motor control, language, attention, balance, or other affected functions.

How Are Neuromodulation Targets Selected?

The selection of a neuromodulation target is not determined by a single scan result.

Doctors may consider several factors, including:

  1. The location and extent of the stroke
  2. The patient’s neurological symptoms
  3. Functional MRI findings
  4. Connectivity between different brain regions
  5. The reliability of the identified functional network
  6. The physical characteristics of the stimulation technology
  7. The patient’s rehabilitation goals and overall medical condition

By combining brain imaging with clinical assessment, the medical team can develop a more individualized intervention strategy.

Potential Clinical and Research Applications

Personalized brain mapping and image-guided neuromodulation have been investigated in several neurological and psychiatric fields.

Potential clinical or research applications include:

  • Post-stroke motor dysfunction
  • Post-stroke aphasia
  • Depression
  • Parkinson’s disease
  • Alzheimer’s disease
  • Chronic pain
  • Post-traumatic stress disorder
  • Selected neurodevelopmental conditions

The level of evidence, regulatory status, and clinical suitability differs between conditions. Some applications remain experimental or are available only in specialized clinical or research settings.

Patients should consult qualified specialists before considering these technologies.

Who May Not Be Suitable?

Functional MRI and non-invasive brain stimulation have different safety requirements.

MRI-related considerations

MRI may not be suitable for certain patients with implanted electronic devices or magnetic metal components, including some:

  • Cardiac pacemakers
  • Cochlear implants
  • Aneurysm clips
  • Neurostimulators
  • Metallic foreign bodies

Not all implants are prohibited. Some modern devices are MRI-conditional, meaning scanning may be possible under specific conditions. The radiology team must verify the exact implant model before examination.

Brain stimulation-related considerations

Patients with a history of epilepsy, seizures, certain brain injuries, or medications that affect seizure thresholds may require additional assessment before transcranial magnetic stimulation.

Pregnant patients and people with severe or unstable cardiovascular conditions should also receive an individualized medical evaluation.

A complete medical history and formal safety screening are essential before treatment.

A More Personalized Direction for Stroke Rehabilitation

Stroke rehabilitation is rarely a simple or rapid process.

For many patients, progress depends on early medical treatment, consistent rehabilitation, family support, secondary stroke prevention, and long-term follow-up.

Personalized brain mapping does not replace these foundations. Instead, it may provide doctors with additional information about how an individual patient’s functional brain networks are organized.

When appropriately combined with rehabilitation medicine and non-invasive neuromodulation, this approach may help selected patients receive more precisely targeted care.

Mrs. Chen’s experience offers hope to families facing the difficult consequences of stroke. More importantly, it highlights a broader development in neurological rehabilitation: treatment is gradually moving from standardized protocols toward strategies informed by each patient’s unique brain networks and functional needs.

Stroke Rehabilitation at Shulan Hangzhou Hospital

Shulan Hangzhou Hospital provides multidisciplinary medical services for patients with complex neurological and rehabilitation needs.

Depending on the patient’s condition, assessment and treatment may involve specialists in:

  • Neurology
  • Rehabilitation medicine
  • Medical imaging
  • Neurosurgery
  • Physical therapy
  • Occupational therapy
  • Speech and swallowing therapy
  • Non-invasive neuromodulation

International patients considering stroke rehabilitation in China should prepare relevant medical records, including brain MRI or CT scans, hospital discharge summaries, medication lists, rehabilitation records, and recent neurological assessments.

A preliminary medical review can help determine whether further evaluation at Shulan Hangzhou Hospital may be appropriate.

Medical Disclaimer

This article is provided for general health education only. It does not constitute medical advice, diagnosis, treatment recommendations, or a guarantee of clinical results.

The patient story described above represents an individual experience. Recovery outcomes vary according to the type and severity of stroke, treatment timing, rehabilitation participation, age, underlying medical conditions, and many other factors.

Patients experiencing symptoms of stroke, including sudden facial weakness, arm weakness, speech difficulty, severe dizziness, loss of balance, or sudden vision changes, should seek emergency medical assistance immediately.

Treatment and rehabilitation decisions must be made by qualified healthcare professionals following an in-person medical assessment.

Source material provided by:

International Health Care Center, Shulan Hangzhou Hospital
Contributors: Zhou Sijia and Wang Xuanying

Wenzhou Annual Academic Conference on Psychosomatic Medicine Successfully Held

Wenzhou People’s Hospital Hosts 2026 Psychosomatic Medicine Conference

Wenzhou People’s Hospital hosted the 2026 Wenzhou Psychosomatic Medicine Annual Conference from June 27 to 28, 2026.

The event also included the 8th Jiangnan Psychosomatic Forum. More than 100 medical experts attended the conference. They came from Zhejiang Province and other regions of China.

The Wenzhou Medical Association organized the event. Meanwhile, Wenzhou People’s Hospital served as the host institution.

The conference focused on new developments in psychosomatic medicine. It also promoted cooperation between clinical medicine, psychology and patient care.

Advancing Psychosomatic Medicine in Wenzhou

Psychosomatic medicine studies the relationship between physical health and psychological wellbeing.

Stress, anxiety, depression and sleep problems can affect physical symptoms. Therefore, doctors often need to consider both physical and emotional factors.

For example, some patients experience chest discomfort, digestive problems or chronic pain. However, medical tests may not fully explain their symptoms. Psychological stress may increase the discomfort.

As a result, effective care may require several medical departments. Physicians, psychologists, nurses and other specialists can work together.

During the conference, experts discussed new clinical guidelines and research developments. In addition, they shared practical experience from different hospitals.

These discussions aimed to improve psychosomatic care in Wenzhou. They also supported more standardized diagnosis and treatment.

Hospital Leaders Highlight Integrated Care

Chen Xiaoshu chaired the opening ceremony. He serves as Chair of the Psychosomatic Medicine Branch of the Wenzhou Medical Association.

Ruan Guomo, Party Secretary of Wenzhou People’s Hospital, welcomed the attending experts.

He reviewed the development of psychosomatic medicine in Wenzhou. Moreover, he explained its role in connecting physical treatment with psychological support.

Ruan also introduced the hospital’s recent work. Wenzhou People’s Hospital continues to develop integrated care, professional training and medical research.

Professor Liu Yuanyuan also addressed the conference. She serves on the standing committee of the Chinese Medical Association’s psychosomatic medicine branch.

She explained that the Jiangnan Psychosomatic Forum has developed over eight sessions. Today, it provides an important platform for academic communication.

Furthermore, the forum encourages cooperation between psychology and clinical medicine.

Eleven Academic Forums Cover Key Medical Topics

The conference included one main forum and ten specialized forums.

Together, the eleven academic sections covered:

  • General psychosomatic medicine
  • Psychocardiology
  • Cognitive health
  • Pain and psychosomatic nursing
  • Traditional Chinese medicine
  • Digestive psychosomatic medicine
  • Balint group practice
  • Sleep and psychological health
  • Child and adolescent psychosomatic medicine
  • Psychosomatic case studies
  • Attention-deficit/hyperactivity disorder

Each forum focused on practical clinical needs.

For instance, the psychocardiology forum examined links between emotional health and cardiovascular conditions. The digestive forum explored connections between stress and digestive symptoms.

Meanwhile, the sleep forum discussed psychological factors behind sleep disorders. The child and adolescent forum focused on younger patients.

Experts also discussed chronic pain, cognitive problems and ADHD. Therefore, the program reflected the wide scope of modern psychosomatic medicine.

Promoting Multidisciplinary Patient Care

Modern psychosomatic care does not separate the mind from the body.

Instead, doctors assess the patient’s physical symptoms, emotional state and social environment. They can then create a more complete treatment plan.

This approach may help patients with complex or recurring symptoms. It can also improve communication between medical departments.

In addition, multidisciplinary care may reduce unnecessary examinations. It may help patients understand the factors that affect their condition.

The conference encouraged specialists to strengthen this type of cooperation. As a result, patients may receive more coordinated medical support.

Honoring a Pioneer of Psychosomatic Medicine

The conference included a special memorial session for Professor He Jincai.

Professor He played an important role in developing psychosomatic medicine in Wenzhou. A video presentation reviewed her life and medical career.

Her husband, Han Jianhai, also shared his memories during the event.

The session highlighted Professor He’s academic contributions. At the same time, it reflected the humanistic values of psychosomatic medicine.

Her work continues to influence medical professionals in the region.

Strengthening Regional Medical Cooperation

Zhang Xiuhua announced the establishment of the fourth committee of the Psychosomatic Medicine Branch.

The conference also presented appointment certificates to the incoming chair and deputy chairs.

The new committee will support regional cooperation. Moreover, it will promote professional training and standardized clinical practice.

Participating experts said they would continue sharing knowledge after the conference. They also planned to strengthen cooperation between hospitals and medical specialties.

Therefore, the event created opportunities for long-term academic development.

Supporting Mental and Physical Health

The 2026 Wenzhou Psychosomatic Medicine Annual Conference showed the growing importance of integrated healthcare.

Mental health can influence physical health. Likewise, long-term physical illness can affect a patient’s emotional wellbeing.

For this reason, hospitals need coordinated treatment models.

Wenzhou People’s Hospital continues to explore patient-centered psychosomatic care. It also supports medical education, clinical research and multidisciplinary cooperation.

Through these efforts, the hospital aims to improve the quality of care for patients in Wenzhou and surrounding regions.

Medical Support for International Patients in China

International patients may need help when seeking medical care in China.

Our team can assist with hospital matching and appointment coordination. In addition, we can help prepare medical records and arrange translation support.

We can also assist patients with communication before and during their hospital visit.

Contact us to learn more about Wenzhou People’s Hospital and available medical services in China.

Shulan joint replacement surgeon

After Hip Replacement Surgery, She Walked Out of the Operating Room Steadily

Joint replacement surgeon

For many patients, the words hip replacement surgery may bring to mind significant surgical trauma, blood loss, prolonged bed rest and a lengthy rehabilitation process.

Patients may feel anxious before surgery, while their families worry about postoperative care, mobility and the time required for recovery.

Today, however, advances in precision minimally invasive surgery and the implementation of Enhanced Recovery After Surgery, or ERAS, are changing the traditional experience of joint replacement.

At Shulan (Jinan) Hospital, a patient recently demonstrated this new approach to hip replacement recovery by walking steadily out of the operating room after surgery.


A New Milestone in Hip Replacement Recovery

On April 30, the Orthopedics Department at Shulan (Jinan) Hospital successfully completed a right total hip arthroplasty using the Direct Anterior Approach, or DAA, with the patient positioned in the lateral decubitus position.

The patient remained stable throughout the operation and tolerated the procedure well.

After fully recovering from general anesthesia, she did not require transportation on a stretcher or assistance from family members. With the support of a walker, she was able to stand, walk independently and steadily leave the operating room.

This achievement represented an important milestone in the hospital’s approach to rapid recovery after hip replacement surgery.


Precision DAA Hip Replacement Surgery

For this procedure, the orthopedic team selected the minimally invasive DAA rather than a traditional conventional surgical approach.

During the operation, the team used high-definition intraoperative fluoroscopic positioning and refined, layered anatomical dissection. These techniques supported accurate positioning and reflected the hospital’s commitment to precision orthopedic care.

The DAA procedure formed an important part of the treatment plan. However, the patient’s ability to begin walking shortly after surgery was not the result of surgical technique alone.

It was also supported by a coordinated recovery system covering every stage of care.


How ERAS Supports Early Walking After Surgery

The orthopedic team followed the principles of ERAS rapid recovery management throughout the patient’s treatment.

ERAS is not a single postoperative rehabilitation exercise. It is a coordinated care model that connects preoperative preparation, intraoperative management and postoperative rehabilitation.

For this patient, the medical team developed an individualized recovery plan based on her condition.

The process included:


    • Individualized assessment and preparation before surgery
    • Precise surgical planning and intraoperative management
    • Standardized anesthesia and recovery procedures
    • Early mobility support after the patient regained consciousness
    • Continuous postoperative observation and rehabilitation guidance

Through this closed-loop approach, each stage of care supported the next, creating the conditions needed for earlier and safer postoperative mobility.


Hip Replacement Is About More Than Replacing a Joint

For patients with serious hip joint disorders, a successful total hip replacement is not simply about removing and replacing the affected joint.

The broader goals of treatment include:


    • Reducing postoperative discomfort
    • Supporting earlier walking
    • Promoting faster functional recovery
    • Reducing the burden of prolonged bed rest
    • Helping patients return to family and social life
    • Supporting the long-term function of the prosthetic joint

The successful combination of the lateral-position DAA procedure and full-cycle ERAS management may help reduce unnecessary time in bed, shorten the recovery process and ease the long-term caregiving pressure placed on family members.

Earlier mobility can also help patients regain confidence after surgery and participate more actively in their rehabilitation.


Reducing the Burden on Patients and Families

A prolonged recovery period can affect more than a patient’s physical health. It may also create emotional, financial and caregiving pressure for the entire family.

By improving surgical precision and organizing the recovery process around the individual patient, the orthopedic team aims to reduce hospitalization time and help patients return to normal daily activities more efficiently.

For this patient, walking out of the operating room was not only a visible sign of postoperative mobility. It also reflected the combined work of surgeons, anesthesiologists, nurses and rehabilitation professionals.


Patient-Centered Orthopedic Care at Shulan Hospital

The case demonstrates how minimally invasive orthopedic technology and ERAS management can work together to improve the experience of hip replacement surgery.

At Shulan (Jinan) Hospital, the Orthopedics Department continues to focus on precision diagnosis, individualized surgical planning and comprehensive postoperative rehabilitation.

The goal is not only to complete the operation successfully, but also to help patients experience less discomfort, regain mobility earlier and return to everyday life with greater confidence.

For patients experiencing persistent hip pain, limited mobility or difficulty performing daily activities, a professional orthopedic assessment can help determine the most appropriate treatment plan.

Recovery after hip replacement surgery varies according to the patient’s condition, surgical plan and rehabilitation progress. Individual results may differ, and treatment decisions should be made after evaluation by qualified medical professionals.

Advanced lung cancer treatment in China

Advanced Lung Cancer Patient Achieves 8-Year Remission After Autologous Lung Transplantation


For many patients diagnosed with locally advanced lung cancer, surgery may no longer appear possible when a tumor has invaded major blood vessels, bronchi, or other critical structures.

However, advances in multidisciplinary cancer treatment are creating new possibilities for carefully selected patients.

In 2018, a 52-year-old patient, referred to as Mr. Wang to protect his privacy, was diagnosed with advanced lung cancer during a routine medical examination. The diagnosis came unexpectedly at a time when he was managing two factories and enjoying a stable family life in Shenzhen.

Eight years after undergoing a complex procedure known as autologous lung transplantation, his latest imaging results showed no definitive evidence of tumor recurrence or metastasis.

A Tumor Involving Critical Pulmonary Structures

Further examinations showed that Mr. Wang had squamous cell carcinoma in the upper lobe of his left lung.

The tumor had already invaded or closely involved several important structures, including:

  • The left main pulmonary artery
  • The left main bronchus
  • The left pulmonary vein
  • Structures around the pulmonary hilum

Under these circumstances, conventional lung cancer surgery carried significant risks. Removing the entire affected area could have resulted in the loss of too much functioning lung tissue, while incomplete removal might not have achieved adequate tumor control.

The medical team therefore organized a multidisciplinary consultation involving specialists from cardiothoracic surgery, oncology, medical imaging, anesthesiology, respiratory and critical care medicine, pathology, and nuclear medicine.

Neoadjuvant Therapy Created an Opportunity for Surgery

After reviewing the patient’s condition, the multidisciplinary team decided to begin with two cycles of neoadjuvant chemotherapy.

Neoadjuvant therapy refers to treatment given before surgery. Its purpose is often to reduce the size or extent of a tumor, control the disease, and potentially create better conditions for surgical removal.

Following two treatment cycles, Mr. Wang’s tumor decreased in size and the disease was partially controlled.

This response provided a possible window for surgery. Nevertheless, the tumor remained closely connected to the major vessels and bronchi at the pulmonary hilum. A conventional resection still could not easily achieve both complete tumor removal and preservation of adequate lung function.

The surgical team therefore considered a highly specialized alternative: autologous lung transplantation for advanced lung cancer.

What Is Autologous Lung Transplantation?

Autologous lung transplantation is fundamentally different from a conventional donor lung transplant.

The procedure uses the patient’s own lung rather than a donor organ. During surgery, the affected lung is removed from the body. Surgeons then perform precise tumor resection and reconstruction outside the body before reimplanting the remaining healthy lung tissue.

The process may include:

  1. Removing the affected lung.
  2. Excising the tumor-bearing lobe and involved tissue.
  3. Reconstructing the remaining bronchial and vascular structures.
  4. Reimplanting the preserved healthy lung tissue.
  5. Reconnecting the pulmonary vessels and bronchus.

This technique may allow surgeons to remove tumors that are difficult to treat through conventional resection while preserving more functional lung tissue.

However, it is an extremely demanding operation. It requires advanced thoracic surgical skills, precise vascular and bronchial reconstruction, experienced anesthesiology support, and close perioperative critical care.

Surgery Was Only One Part of the Treatment

Mr. Wang successfully completed the operation after detailed preoperative planning and close cooperation among several medical departments.

However, surgery alone was not considered sufficient.

After the procedure, he continued to receive comprehensive treatment, including chemotherapy and immunotherapy. He remained in stable condition for approximately three years.

In 2021, the disease recurred. The medical team administered additional chemotherapy, and the tumor was brought under control again.

This part of the case is important because it demonstrates that long-term cancer management may involve several treatment stages. Even after major surgery, patients generally require regular follow-up examinations and may need additional systemic treatment depending on their individual condition.

Eight Years Later: Imaging Consistent With Complete Remission

After several years without contact, Mr. Wang recently returned to the Department of Cardiothoracic Surgery at Southern Medical University Shenzhen Hospital for follow-up.

The medical team was encouraged to see him in good general condition eight years after the original diagnosis and operation.

Whole-body imaging showed:

  • No definitive hypermetabolic tumor lesions
  • No clear signs of recurrence
  • No identified distant metastasis
  • Lymph node findings consistent with post-treatment changes

According to the case report, these imaging findings were consistent with a highly satisfactory recovery status and complete tumor remission.

What Can Patients Learn From This Case?

Mr. Wang’s experience does not mean that autologous lung transplantation is suitable for every person with advanced lung cancer.

Eligibility depends on many factors, including:

  • The precise location and extent of the tumor
  • Whether distant metastasis is present
  • The response to preoperative systemic therapy
  • Remaining lung function
  • Cardiovascular health
  • The patient’s overall physical condition
  • The experience of the surgical and multidisciplinary teams

Nevertheless, this case demonstrates that some patients initially considered unsuitable for conventional surgery may still have treatment opportunities after a comprehensive multidisciplinary evaluation.

For complex lung cancer cases, obtaining a second opinion from an experienced thoracic oncology team may help patients understand whether surgery, chemotherapy, immunotherapy, radiotherapy, targeted therapy, or a combined treatment strategy could be considered.

Seeking Advanced Lung Cancer Treatment in China?

Patients considering lung cancer treatment in China may benefit from having their medical records reviewed before traveling.

Our international medical coordination team can assist with:

  • Medical record collection and translation
  • Remote specialist consultation
  • Multidisciplinary case review
  • Hospital and physician matching
  • Treatment appointment coordination
  • Visa and travel guidance
  • Interpretation during medical visits
  • Follow-up communication after treatment

Every patient’s condition is different. Treatment recommendations should only be made after specialists review pathology reports, imaging examinations, previous treatment records, and the patient’s current health status.

Contact us to request a preliminary medical evaluation and learn more about advanced lung cancer treatment options in China.

0c637365 4911 496b bd8e 9d91a257e24f

Eight Years After Autologous Lung Transplantation: A Long-Term Survival Story in Advanced Lung Cancer

For many patients, a diagnosis of advanced lung cancer can feel like the end of the road. However, advances in systemic therapy, complex thoracic surgery and multidisciplinary cancer care are creating new possibilities for carefully selected patients.

A patient treated at Southern Medical University Shenzhen Hospital provides a remarkable example. Eight years after being diagnosed with locally advanced lung cancer, he returned to the hospital in good condition, with follow-up imaging showing no definite signs of recurrence or metastasis.

A Diagnosis That Changed Everything

In May 2018, a 52-year-old patient, referred to here as Mr. Wang, underwent a routine medical examination during a visit to his hometown. A chest CT scan revealed advanced lung cancer.

Further imaging and pathological examinations confirmed squamous cell carcinoma in the upper lobe of his left lung. The tumor had already invaded several critical structures, including the left main pulmonary artery, left main bronchus and left pulmonary vein.

Because the tumor was closely connected to the major blood vessels and airways at the pulmonary hilum, conventional surgical removal carried extremely high risks. Radiotherapy and chemotherapy alone were also unlikely to provide sufficient local control.

Multidisciplinary Treatment Created a Surgical Opportunity

The hospital organized a multidisciplinary team consultation involving specialists from cardiothoracic surgery, oncology, medical imaging, anesthesiology, respiratory and critical care medicine, pathology and nuclear medicine.

Although the cancer was locally advanced, the team believed that treatment might still be possible if systemic therapy could first reduce the size of the tumor.

Mr. Wang therefore received two cycles of neoadjuvant chemotherapy. After treatment, the tumor became smaller and the disease was partially controlled, creating a potential opportunity for surgery.

However, the tumor remained closely attached to the major pulmonary vessels and bronchi. A conventional operation could not completely remove the cancer while preserving enough functioning lung tissue.

The medical team needed a different approach.

What Is Autologous Lung Transplantation?

After extensive evaluation, the cardiothoracic surgery team decided to perform an autologous lung transplantation.

Unlike conventional lung transplantation, this procedure does not involve receiving a lung from a donor. Instead, the patient’s own lung is temporarily removed from the body.

The surgical team then:

  1. Removes the tumor-bearing portion of the lung outside the body.
  2. Resects the affected bronchi and blood vessels.
  3. Reconstructs the remaining healthy lung tissue.
  4. Reconnects the bronchial and vascular structures.
  5. Reimplants the reconstructed lung into the patient.

This approach can make it possible to remove tumors involving complex structures while preserving more healthy lung tissue than a complete pneumonectomy.

However, autologous lung transplantation is an exceptionally demanding procedure. It requires advanced surgical expertise, precise reconstruction of pulmonary vessels and bronchi, experienced anesthesia management and close cooperation between multiple medical departments.

Surgery Was Only One Part of the Treatment

The operation was successfully completed following detailed preoperative planning and close multidisciplinary cooperation.

After surgery, Mr. Wang continued to receive chemotherapy and immunotherapy as part of a comprehensive treatment plan. He remained in stable condition for approximately three years.

In 2021, the cancer recurred. Fortunately, further chemotherapy brought the disease under control again. The hospital later lost contact with him, and the medical team did not know how his condition had developed.

An Unexpected Return Eight Years Later

Recently, Mr. Wang returned to the Department of Cardiothoracic Surgery for a follow-up examination.

Eight years after the original diagnosis and major operation, he appeared in good health. Whole-body imaging showed no definite hypermetabolic lesions and no clear evidence of recurrent or metastatic disease. The imaging findings were considered consistent with complete remission.

His experience demonstrates that even some patients with extremely advanced disease may achieve long-term survival when appropriate systemic treatment, complex surgery and long-term follow-up are successfully combined.

What This Case Means for International Patients

This case does not mean that autologous lung transplantation is suitable for every patient with advanced lung cancer. Treatment decisions depend on many factors, including:

  • Tumor location and pathological type
  • Involvement of major blood vessels and bronchi
  • Response to chemotherapy or immunotherapy
  • Remaining lung function
  • General physical condition
  • Presence of distant metastases
  • Surgical experience of the medical team

For international patients considering advanced lung cancer treatment in China, obtaining a multidisciplinary medical review is an important first step. Specialists can assess whether conventional surgery, systemic therapy, radiotherapy, immunotherapy or a more complex surgical strategy may be appropriate.

Hope Through Individualized Cancer Treatment

Advanced lung cancer remains a serious and challenging disease. Nevertheless, this eight-year survival story shows that an initially inoperable or extremely difficult tumor does not always mean that all treatment possibilities have been exhausted.

Through neoadjuvant chemotherapy, autologous lung transplantation, postoperative systemic treatment and continued disease management, Mr. Wang achieved an outcome that once seemed impossible.

Every patient’s condition is different, but careful evaluation and individualized treatment may reveal possibilities that are not apparent at the time of diagnosis.


CTA

Seeking advanced lung cancer treatment in China?

Our international patient coordination team can assist with medical record preparation, specialist consultations, hospital communication, translation and treatment arrangements in China.

Contact us to request an initial medical case review.

外籍患者赴华就医

Two International Snoring Patients Find Long-Term Sleep Relief With Minimally Invasive ENT Surgery

Chronic loud snoring and nighttime breathlessness are sleep disorders many international expats struggle with daily. For two overseas patients, Mr. Emilio from Italy and Mr. Stephen from Australia, persistent severe sleep apnea ruined their daily energy and long-term physical health. Conservative treatments available in their home countries failed to resolve their airway blockage fundamentally. Their cross-border medical journey to Southern Medical University Shenzhen Hospital demonstrates the value of professional multi-disciplinary sleep assessment, customized minimally invasive airway surgery, and full-cycle international patient support for people seeking reliable snoring treatment outside their home countries.


Growing Demand for Cross-Border Sleep Medical Services in the Greater Bay Area

The Guangdong-Hong Kong-Macao Greater Bay Area has developed rapidly over recent years, attracting countless international enterprises and overseas talents to settle in Shenzhen. As more expats live and work here, there is higher demand for high-quality, standardized medical services that can cater to foreign patients’ unique healthcare needs.
Many international residents struggle with chronic snoring and sleep apnea, yet conservative treatments available in their home countries often fail to deliver lasting relief. Advanced minimally invasive surgical solutions in China’s top-tier public hospitals have become a trusted alternative for global patients seeking long-term sleep improvement.


Two Overseas Patients Suffering From Severe Long-Term Snoring

Mr. Emilio, a patient from Italy, had battled severe obstructive sleep apnea for decades. His loud snoring woke him repeatedly every night with a choking, breathless feeling. Poor sleep quality left him dizzy, fatigued and unfocused throughout the day, and chronic sleep interruptions triggered multiple physical discomforts. He tried a wide range of conservative therapies overseas, but none brought stable, long-lasting improvement.
Similarly, Mr. Stephen from Australia suffered from persistent heavy snoring for many years. After learning about the outstanding expertise of Chief Physician Zhang Xiangmin from the ENT Department of Southern Medical University Shenzhen Hospital via global medical referral channels, he traveled all the way to Shenzhen for specialized treatment.


Full Systematic Sleep Assessment to Locate Airway Blockages

After admission, Chief Physician Zhang’s team provided fully barrier-free multilingual communication for both international patients. A complete set of targeted examinations was arranged for Mr. Emilio and Mr. Stephen, including overnight sleep monitoring, laryngoscopy and full airway evaluation. The ENT team precisely identified the exact sites and root causes of upper airway obstruction triggering their snoring and apnea.


Customized Minimally Invasive Surgery for Individual Airway Conditions

Based on each patient’s unique anatomical condition, the medical team designed personalized minimally invasive snoring correction surgical plans. With advanced surgical equipment and precise endoscopic techniques, surgeons gently released obstructed soft tissue and reconstructed unobstructed breathing pathways. This minimally invasive approach creates tiny wounds, speeds up recovery and delivers stable, long-term therapeutic effects for sleep apnea.alized Treatment: TAI Combined with Immunotherapy

After multidisciplinary discussion, the medical team customized a treatment plan for Ms. Lee:

Transarterial Infusion Chemotherapy, also known as TAI, combined with immunotherapy.

TAI is a treatment method that delivers chemotherapy drugs directly into the arteries supplying the tumor area. Compared with conventional systemic chemotherapy, this approach may help increase the local drug concentration around the tumor while reducing some systemic side effects.

Immunotherapy works differently. Instead of directly attacking the tumor like chemotherapy, it helps activate the patient’s own immune system so immune cells can better recognize and attack cancer cells.

In Ms. Lee’s case, the treatment strategy combined local intervention with systemic immune support.


Smooth Operation & Thoughtful Post-Surgery Rehabilitation Care

Relying on Chief Physician Zhang’s sophisticated surgical skills and decades of clinical experience, both minimally invasive airway surgeries were completed safely and smoothly. After each operation, our nursing team delivered detailed, individualized rehabilitation guidance, covering rest arrangements, diet rules and daily recovery precautions. Within just a few days, both international patients recovered well and were cleared for discharge.


Authentic Feedback From Recovered International Patients

At discharge, Mr. Stephen shared his heartfelt excitement: “I never wake up gasping for breath at night anymore, my snoring is completely gone, and I can sleep soundly all the way until morning. I feel full of energy every single day!” Mr. Emilio also stated that the surgical outcome far exceeded his expectations. His years-long


Global Recognition Validates Our ENT Clinical Strength

International patients traveling across borders to seek snoring treatment, and their unanimous high satisfaction, fully recognize the professional clinical strength of our ENT Department. It also serves as clear proof of our hospital’s complete, mature international medical service system.


Dedicated International Patient Service Channels at Our Hospital

As a high-standard Grade A public general hospital in Qianhai, Southern Medical University Shenzhen Hospital strictly follows international medical service standards for all overseas visitors.


We have built exclusive cross-border medical access for expat and international patients:

  • Multilingual medical staff and professional interpreters to eliminate language barriers
  • Fully optimized full-cycle medical procedures covering online consultation, appointment, examination, surgery and post-operative rehabilitation
  • Complete streamlined medical support that removes all obstacles for patients receiving treatment far from home


FAQ


What is obstructive sleep apnea (severe snoring)?

Obstructive sleep apnea is a sleep disorder caused by collapsed soft tissue blocking the airway during sleep. Sufferers will experience loud snoring, sudden choking wake-ups, daytime fatigue and poor concentration. Long-term untreated apnea raises risks of cardiovascular problems and endocrine disorders. Conservative tools like nasal strips and breathing masks only ease symptoms temporarily, rather than fixing structural blockages.


 Is minimally invasive snoring surgery suitable for all international patients?

Not every patient fits the same surgical plan. Our ENT team will arrange full sleep monitoring and airway endoscopy to check your soft tissue structure, apnea severity and physical health, then customize a minimally invasive plan only after comprehensive evaluation.


How long is the recovery period after minimally invasive airway surgery?

Most patients can be discharged within 3–7 days after the operation. Mild throat discomfort will fade within 2 weeks, and full tissue recovery takes around 1 month. Our nurses will provide detailed diet and rest guidance to speed up rehabilitation.


Do you provide multilingual support for overseas snoring patients?

Yes. We have full-time multilingual medical staff and professional interpreters. All consultation, examination, surgery communication and rehabilitation guidance can be delivered in English and other mainstream languages with zero language barriers.


Can I book a sleep assessment remotely before arriving in Shenzhen?

Absolutely. International patients can submit their sleep symptoms, previous examination reports and medical history via our official consultation channel in advance. Our ENT team will give preliminary professional advice and arrange a reserved appointment for your in-hospital sleep monitoring.


Medical Disclaimer

This article is only for health education and real international patient case sharing. It cannot replace professional face-to-face medical diagnosis and treatment. Individual surgical recovery results vary by physical condition. All overseas patients shall consult qualified ENT specialists to obtain personalized medical advice before deciding on surgical treatment.


企业微信截图

Malaysian Patient with Rare Fallopian Tube Cancer Finds New Treatment Hope at Fuda Cancer Hospital

Abnormal vaginal bleeding is a symptom that should never be ignored. For one Malaysian patient, Ms. Lee, what initially seemed like a gynecological issue eventually led to the diagnosis of an extremely rare cancer: primary fallopian tube squamous cell carcinoma.

Her journey from Malaysia to Guangzhou, China reflects the importance of timely diagnosis, multidisciplinary evaluation, and personalized cancer treatment for international patients.


From Abnormal Bleeding to a Rare Cancer Diagnosis

Ms. Lee first noticed unexplained vaginal bleeding and visited a private doctor in Malaysia. After gynecological examination and cervical conization, her pathology report showed CIN III, also known as severe cervical dysplasia or carcinoma in situ of the cervix.

At that time, her doctor recommended a hysterectomy to prevent further progression. However, because the bleeding had stopped and she did not fully understand the seriousness of the condition, Ms. Lee chose to delay surgery.

Several months later, the bleeding returned. This time, she underwent total hysterectomy with bilateral salpingo-oophorectomy. The postoperative pathology report revealed a more serious condition:

  • Well-differentiated keratinizing squamous cell carcinoma of the cervix
  • Moderately differentiated squamous cell carcinoma in the right fallopian tube
  • Tumor invasion extending to the right ovary
  • Evidence suggesting primary fallopian tube squamous cell carcinoma

Primary fallopian tube carcinoma is already rare, accounting for a very small proportion of female genital tract malignancies. Squamous cell carcinoma of the fallopian tube is even rarer.


Why Fallopian Tube Cancer Is Difficult to Detect Early

Fallopian tube cancer can be difficult to diagnose in its early stages because symptoms are often nonspecific. It may be mistaken for gynecological inflammation, ovarian disease, or other pelvic conditions.

Patients should seek medical attention if they experience symptoms such as:

  • Unexplained abnormal vaginal bleeding or discharge
  • Persistent lower abdominal or pelvic pain
  • Unexplained pelvic mass
  • Abdominal bloating
  • Urinary frequency
  • Unexplained weight loss

Early evaluation is especially important for postmenopausal women or patients with recurrent abnormal bleeding.


Recurrence After Surgery and Chemotherapy

After surgery, Ms. Lee received six cycles of chemotherapy combined with targeted therapy. For a period of time, follow-up examinations showed no obvious tumor recurrence or metastasis.

However, in August and September 2025, two follow-up tests showed elevated CEA tumor marker levels. Further examination found small mesenteric lymph nodes and thickening of the right vaginal wall. Her doctor suspected recurrence.

This was a difficult moment for Ms. Lee. After completing another cycle of chemotherapy, she was physically weak and emotionally uncertain. At that time, a close friend introduced her to a public medical lecture related to cancer treatment in China.

After learning more and comparing different hospitals, Ms. Lee decided to seek further treatment in Guangzhou.


Seeking Treatment at Fuda Cancer Hospital in Guangzhou

In October 2025, Ms. Lee arrived in Guangzhou, China, and was admitted to the Fourth Department of Medicine at Fuda Cancer Hospital.

After admission, the hospital’s multidisciplinary team, also known as an MDT, reviewed her case carefully. Her pathology was re-examined and evaluated in detail. The final assessment was:

Recurrent stage IIIA2 right fallopian tube squamous cell carcinoma after surgery.

One important test result attracted the team’s attention: her PD-L1 immunohistochemistry TPS was ≥ 50%. This suggested that immunotherapy, particularly PD-1/PD-L1-related treatment, might be a potential option after comprehensive evaluation.


Personalized Treatment: TAI Combined with Immunotherapy

After multidisciplinary discussion, the medical team customized a treatment plan for Ms. Lee:

Transarterial Infusion Chemotherapy, also known as TAI, combined with immunotherapy.

TAI is a treatment method that delivers chemotherapy drugs directly into the arteries supplying the tumor area. Compared with conventional systemic chemotherapy, this approach may help increase the local drug concentration around the tumor while reducing some systemic side effects.

Immunotherapy works differently. Instead of directly attacking the tumor like chemotherapy, it helps activate the patient’s own immune system so immune cells can better recognize and attack cancer cells.

In Ms. Lee’s case, the treatment strategy combined local intervention with systemic immune support.


Encouraging Follow-Up Results

After six treatment cycles, Ms. Lee’s follow-up results showed encouraging changes:

  • PET-CT showed no obvious signs of hypermetabolic malignant tumors
  • Tumor remission was observed
  • Tumor markers decreased to normal levels

These results suggested that the treatment was effective. Ms. Lee has continued maintenance therapy and follow-up care to help protect the progress she has achieved.

Her story is not simply about a “miracle.” It is about a patient who continued searching for treatment options during a difficult period and found a personalized approach through multidisciplinary care.


What International Patients Can Learn from This Case

Ms. Lee’s experience highlights several important points for cancer patients and families:

First, abnormal vaginal bleeding should not be ignored, especially when it happens repeatedly or after menopause.

Second, rare cancers often require careful pathological review and multidisciplinary consultation.

Third, for recurrent or complex cancer cases, personalized treatment planning may provide additional options beyond standard therapy.

Finally, international patients seeking cancer treatment in China should look for hospitals with multidisciplinary teams, experience in complex cases, and international patient support services.


About Fuda Cancer Hospital

Fuda Cancer Hospital, located in Guangzhou, China, provides cancer diagnosis and treatment services for both local and international patients. The hospital’s multidisciplinary teams evaluate complex cancer cases and design personalized treatment plans based on each patient’s condition, pathology, imaging results, tumor markers, and overall health status.

For international patients, coordinated medical support can help make the process of consultation, admission, treatment, and follow-up more manageable.


FAQ

What is fallopian tube cancer?

Fallopian tube cancer is a rare gynecological malignancy that starts in the fallopian tubes. Because early symptoms are often unclear, it may be difficult to diagnose at an early stage.

Is fallopian tube squamous cell carcinoma common?

No. Primary fallopian tube carcinoma itself is rare, and squamous cell carcinoma of the fallopian tube is an even rarer subtype.

What symptoms should patients pay attention to?

Patients should pay attention to abnormal vaginal bleeding, abnormal discharge, pelvic pain, abdominal bloating, pelvic mass, urinary frequency, or unexplained weight loss.

What treatment did the patient receive at Fuda Cancer Hospital?

According to the case, the patient received multidisciplinary evaluation followed by transarterial infusion chemotherapy combined with immunotherapy.

Can every patient receive the same treatment?

No. Cancer treatment must be based on the patient’s diagnosis, stage, pathology, biomarkers, imaging results, previous treatments, and overall physical condition. Patients should consult qualified medical professionals before making treatment decisions.

Medical Disclaimer

This article is for health education and case-sharing purposes only. It should not be used as a substitute for professional medical diagnosis or treatment. Individual treatment results may vary. Patients should consult qualified doctors for personalized medical advice.


D39134b9 2b84 454f 86a7 d8ea5be6e63f

Pulmonary Arterial Hypertension Care at Ningbo Medical Center Lihuili Hospital

Pulmonary arterial hypertension, often called PAH, is a serious condition that affects the blood vessels between the heart and lungs. When pressure in the pulmonary arteries becomes abnormally high, the right side of the heart has to work harder to pump blood to the lungs. Over time, this may lead to worsening shortness of breath, fatigue, reduced exercise capacity, and even right heart failure.

For patients and families, PAH can be difficult to recognize in the early stage because its symptoms may look similar to ordinary tiredness, poor recovery after illness, or general heart and lung discomfort. Some patients may experience breathlessness after light activity, difficulty climbing stairs, chest discomfort, dizziness, swelling, or bluish lips caused by low oxygen levels.

In Ningbo, Zhejiang Province, Ningbo Medical Center Lihuili Hospital has built a specialized clinical team focusing on pulmonary arterial pressure abnormalities and pulmonary arterial hypertension. On March 4, 2025, Zhejiang Province announced the first batch of selected “Small but Strong” Clinical Innovation Teams. The Pulmonary Arterial Pressure Abnormality Team of Ningbo Medical Center Lihuili Hospital was the only team in Ningbo to be included in this list.

This recognition highlights the hospital’s long-term work in the diagnosis, treatment, research, and patient management of pulmonary arterial hypertension.

A Multidisciplinary Team for Complex PAH Care

Pulmonary arterial hypertension is not only a lung disease. It often requires close cooperation between different medical specialties because the condition may involve the heart, lungs, immune system, blood vessels, and long-term medication management.

The PAH team at Ningbo Medical Center Lihuili Hospital brings together specialists from several departments, including respiratory and critical care medicine, cardiology, thoracic surgery, interventional radiology, rheumatology and immunology, pharmacy, laboratory medicine, and medical-engineering innovation research.

This multidisciplinary model is especially important for patients whose PAH is related to connective tissue diseases, such as systemic lupus erythematosus, also known as SLE. In these cases, doctors need to manage both the underlying immune disease and the elevated pulmonary artery pressure.

A Patient Story: From Severe Symptoms to Long-Term Management

One patient, referred to as Ms. Hu, began experiencing progressive fatigue and shortness of breath after giving birth. At first, she believed her symptoms were related to poor postpartum recovery. However, rest did not improve her condition. Her breathlessness became worse, she could no longer climb stairs easily, and even simple activities such as going out to buy groceries became difficult.

Her lips also began to appear slightly purple, a possible sign of low oxygen levels.

After medical examinations, Ms. Hu was diagnosed with severe pulmonary arterial hypertension associated with systemic lupus erythematosus and connective tissue disease. This diagnosis meant that her immune disease and pulmonary vascular disease both needed careful management.

At Ningbo Medical Center Lihuili Hospital, a multidisciplinary team led by Dr. Wu Shibo from the Department of Respiratory and Critical Care Medicine worked together with specialists from cardiovascular medicine and rheumatology and immunology. The treatment strategy focused on two key goals: controlling lupus activity and keeping pulmonary arterial hypertension at a lower-risk level.

The team used a combined approach, including medication to control immune activity and targeted therapy to help reduce pulmonary artery pressure. Over time, Ms. Hu’s condition gradually stabilized.

During the following five years, she continued regular follow-up visits and underwent periodic right heart catheterization assessments to monitor pulmonary artery pressure. Based on her test results and clinical condition, the medical team adjusted her treatment plan when needed. Today, Ms. Hu has returned to work and resumed a more normal daily life.

Her case shows the importance of early recognition, specialist evaluation, long-term follow-up, and coordinated care for patients with pulmonary arterial hypertension.

Why Early Diagnosis Matters

PAH can progress quietly. In the beginning, symptoms such as fatigue, shortness of breath, and reduced exercise tolerance may be ignored or mistaken for other health problems. However, untreated or poorly controlled pulmonary arterial hypertension can place increasing pressure on the right side of the heart.

Patients should seek medical evaluation if they experience persistent or worsening symptoms such as:

  • Shortness of breath during daily activity
  • Fatigue that does not improve with rest
  • Difficulty climbing stairs
  • Dizziness or fainting
  • Chest discomfort
  • Swelling in the legs, ankles, or abdomen
  • Bluish lips or skin

These symptoms do not always mean a patient has PAH, but they should not be ignored, especially if they continue or become worse.

Specialized PAH Services at Ningbo Medical Center Lihuili Hospital

According to the hospital’s clinical team, Ningbo Medical Center Lihuili Hospital has developed strong capabilities in pulmonary vascular disease care. The hospital’s PAH team has built a foundation in clinical diagnosis, targeted treatment, patient follow-up, and scientific research.

The team is also working to improve PAH screening, optimize diagnosis and treatment workflows, and explore the use of artificial intelligence to support earlier detection and better patient management.

For patients with complex PAH, especially those with immune-related conditions, multidisciplinary care can help doctors evaluate the disease more comprehensively and design a more individualized treatment plan.

Support for International Patients

For international patients considering medical care in China, pulmonary arterial hypertension treatment requires careful preparation. Patients should prepare previous medical records, imaging reports, echocardiography results, right heart catheterization reports if available, medication history, and any diagnosis related to autoimmune or connective tissue disease.

A coordinated medical service platform can help overseas patients communicate with hospitals, organize medical documents, arrange specialist consultations, and understand the treatment process before traveling.

Pulmonary arterial hypertension is a serious but manageable condition when patients receive timely diagnosis, appropriate treatment, and long-term follow-up. Ningbo Medical Center Lihuili Hospital’s specialized PAH team provides a strong example of how multidisciplinary care can support patients with complex heart, lung, and vascular disease.

Medical Disclaimer: This article is for general health information only and should not replace professional medical advice, diagnosis, or treatment. Patients with suspected pulmonary arterial hypertension should consult qualified medical professionals.

企业微信截图

Targeted Therapy for Hypertrophic Obstructive Cardiomyopathy at Shulan Hospital


Cardiovascular disease treatment is entering a new era. Doctors are no longer limited to symptom control alone. With better diagnosis, genetic testing, and targeted drugs, hospitals can now design more precise treatment plans for complex heart conditions.

At Shulan Hospital, this progress is already helping patients with difficult cardiovascular diseases. One important example is the treatment of hypertrophic obstructive cardiomyopathy, also known as HOCM.

This condition can block blood flow from the heart. It may cause chest discomfort, shortness of breath, low blood pressure, heart failure symptoms, and serious long-term risks. For some patients, conventional medication does not provide enough relief.

Shulan Hospital’s Department of Cardiology has explored a more precise approach. Through targeted therapy and multidisciplinary care, the team helped a patient with severe HOCM regain stability and quality of life.

What Is Hypertrophic Obstructive Cardiomyopathy?

Hypertrophic obstructive cardiomyopathy is a heart muscle disease. In this condition, part of the heart muscle becomes abnormally thick.

The thickened muscle can narrow the left ventricular outflow tract. This pathway allows blood to leave the heart and enter the body. When the pathway becomes blocked, the heart must work harder to pump blood.

Patients may experience fatigue, dizziness, chest tightness, shortness of breath, or symptoms of heart failure. Some patients may also have a family history, because hypertrophic cardiomyopathy can be related to genetic factors.

A key measurement in HOCM is the left ventricular outflow tract pressure gradient. A high gradient means the obstruction is serious. Doctors use echocardiography and other tests to evaluate this problem.

A Complex Case at Shulan Hospital

Mr. Jiang, a 68-year-old patient, had lived with hypertrophic obstructive cardiomyopathy for many years. More than ten years ago, he began to show symptoms of heart failure.

Six years ago, doctors implanted a cardiac resynchronization therapy pacemaker to support his heart function. However, his condition later worsened.

When he came to Shulan Hospital, the cardiology team performed a detailed evaluation. The results showed a serious obstruction. His myocardial thickness reached 26 millimeters. His left ventricular outflow tract pressure gradient reached 112 mmHg.

These numbers showed that his heart had great difficulty sending blood into the body.

Conventional treatment had limited effect. His blood pressure was too low, so doctors could not simply increase the medication dose. The team also considered chemical ablation. However, angiography showed that he did not have a suitable target vessel.

The treatment plan reached a difficult point.

Targeted Therapy Brought New Hope

At that time, a new targeted drug for hypertrophic obstructive cardiomyopathy was about to become available in Hangzhou. After discussion with the patient’s family, the cardiology team decided to try this treatment once it entered the market.

The team used the medication carefully. Doctors started with the minimum effective dose and monitored the patient closely.

One month later, the follow-up results showed clear improvement. His left ventricular outflow tract pressure gradient dropped from 112 mmHg to around 60 mmHg. His peripheral blood pressure also returned to a more stable level.

The patient felt more energetic. His family also noticed a visible change in his daily condition.

After that, Mr. Jiang returned to the hospital every four weeks for follow-up. Doctors used echocardiography, blood tests, and other indicators to monitor his progress. His cardiac function remained stable, and the obstruction improved.

Why Targeted Therapy Matters in Cardiology

Traditional treatment for hypertrophic cardiomyopathy often focuses on reducing symptoms. Doctors may use beta-blockers and other medications to slow the heart rate and reduce the workload of the heart.

Some patients may need septal reduction therapy or surgery. However, these options may carry higher risk, especially for older patients or people with multiple health problems.

Targeted therapy offers another direction. It focuses more directly on the disease mechanism. In hypertrophic cardiomyopathy, certain genetic and protein-level abnormalities can affect heart muscle contraction.

By acting on specific targets, new therapies may help reduce obstruction and improve cardiac function. This does not mean every patient can use targeted drugs. Doctors still need careful diagnosis, risk evaluation, and long-term monitoring.

But for selected patients, targeted therapy may provide new possibilities.

Multidisciplinary Care for a High-Risk Patient

Mr. Jiang’s treatment was complex because he did not only have heart disease. He also had long-term liver disease related to schistosomiasis, which had progressed to cirrhosis.

Cirrhosis increased his risk of esophageal and gastric variceal bleeding. After his blood pressure improved, the pressure in fragile vessels also became a concern.

In April, he had an episode of gastrointestinal bleeding. Doctors controlled the condition with conservative treatment. Later, he developed a more serious bleeding event and hemorrhagic shock.

The situation became critical.

Shulan Hospital quickly organized a multidisciplinary consultation. The team included specialists from cardiology, infectious diseases, interventional vascular surgery, gastroenterology, and anesthesiology.

After careful assessment, the team decided to perform an emergency TIPS procedure. TIPS stands for transjugular intrahepatic portosystemic shunt. This procedure helps reduce portal venous pressure and control variceal bleeding.

The operation carried high risk because the patient had recently improved heart function and was in shock. The team monitored his heart rate, blood pressure, and vital signs throughout the procedure.

After more than two hours, the operation achieved successful hemostasis.

Recovery and Long-Term Management

After surgery, the infectious diseases team created a new anti-infection plan. The goal was to reduce complications related to cirrhosis, weak immunity, and postoperative recovery.

The team also worked to prevent hepatic encephalopathy and cardiac insufficiency. After more than one month of rehabilitation, the patient’s gastrointestinal bleeding was controlled.

This case shows why multidisciplinary care is important. A patient with complex disease rarely needs only one treatment. Heart disease, liver disease, bleeding risk, infection risk, and rehabilitation all affect the final outcome.

For Mr. Jiang, targeted therapy improved the core cardiac problem. Then multidisciplinary care helped him survive a later emergency.

Precision Diagnosis Comes Before Precision Treatment

Targeted therapy does not fit every patient. Before doctors use this kind of treatment, they need a precise diagnosis.

This may include blood tests, cardiac imaging, echocardiography, genetic testing, and specialist evaluation. Doctors need to understand the cause of the disease before they choose a therapy.

In cardiovascular medicine, this approach is becoming more important. Some patients need protein-level targeted drugs. Others may benefit from RNA-level therapies or future gene-level treatments.

This shift may change how doctors manage inherited cardiovascular diseases, familial hyperlipidemia, and certain types of cardiomyopathy.

Shulan Hospital’s Approach to Advanced Cardiovascular Care

Shulan Hospital’s cardiology team focuses on both advanced treatment and whole-person care. The hospital does not only treat one symptom. It evaluates the patient’s full condition and builds a coordinated plan.

For patients with complex heart disease, this approach can be especially valuable. They may need cardiology, imaging, interventional treatment, intensive care, hepatology, infectious disease care, and rehabilitation support.

The case of Mr. Jiang reflects this model. It combines targeted cardiovascular therapy, careful monitoring, emergency intervention, and multidisciplinary cooperation.

Conclusion

Targeted therapy for hypertrophic obstructive cardiomyopathy is changing the future of cardiovascular care. It gives selected patients a new option when conventional treatment is not enough.

At Shulan Hospital, the successful management of a complex HOCM case shows the value of precision medicine. It also shows the importance of multidisciplinary care for patients with multiple high-risk conditions.

For patients with unexplained heart failure symptoms, chest discomfort, shortness of breath, or a family history of cardiomyopathy, early evaluation is important. A timely diagnosis can open the door to more personalized treatment options.

As cardiovascular medicine continues to advance, targeted therapy may help more patients achieve better outcomes and a better quality of life.

16049bec 8db8 40b1 8f61 420db62b45e8

Anti-Aging & Regenerative Medicine in China: Exosome Therapy, Stem Cell Infusions, PRP, Thermage FLX and HIFEM

As global demand for healthy aging, preventive care and non-surgical rejuvenation continues to grow, more international patients are exploring anti-aging and regenerative medicine options in China. These services may include physician-led health assessment, skin rejuvenation, body contouring, cellular therapy consultation, and long-term wellness planning.

At GlobalMedPool, we help international patients connect with trusted medical institutions in China, prepare medical documents, arrange specialist consultations and coordinate the patient journey from initial inquiry to follow-up care.

This article introduces several major anti-aging and regenerative medicine options that patients often ask about: exosome therapy, autologous stem cell infusions, PRP facial rejuvenation, Thermage FLX and HIFEM technology.

What Is Anti-Aging & Regenerative Medicine?

Anti-aging and regenerative medicine focuses on supporting healthy aging, improving appearance-related concerns, and helping patients understand their overall biological condition through medical evaluation. Unlike ordinary beauty services, medical anti-aging should be guided by qualified physicians and based on each patient’s age, medical history, skin condition, metabolic status and treatment goals.

For international patients, a responsible anti-aging plan should begin with medical consultation rather than direct treatment. This is especially important for patients with chronic diseases, autoimmune conditions, cancer history, blood disorders, pregnancy, implanted devices or previous cosmetic procedures.

Why Choose China for Anti-Aging and Regenerative Care?

China has developed strong hospital networks, advanced medical equipment and multidisciplinary clinical resources in major cities such as Hangzhou, Ningbo, Shanghai, Guangzhou and Beijing. Some hospitals and medical groups combine general medicine, dermatology, plastic surgery, health management, rehabilitation and laboratory testing within one coordinated system.

For example, Shulan Hospital in Hangzhou is known as a large private general hospital with international medical positioning, while Ningbo Medical Center Lihuili Hospital is a major Grade III public hospital in Zhejiang with broad clinical specialties. For overseas patients, these hospital resources can support not only aesthetic treatment, but also pre-treatment screening, chronic disease evaluation and follow-up planning.

GlobalMedPool works as a medical coordination platform. Our role is not to replace doctors, but to help patients match with appropriate hospitals, understand treatment options, translate medical records, arrange appointments and coordinate communication before, during and after care.

Exosome Therapy: A Popular but Carefully Evaluated Field

Exosome therapy has become one of the most discussed topics in regenerative medicine and aesthetic wellness. Exosomes are tiny extracellular vesicles involved in cell-to-cell communication. In aesthetic settings, they are often discussed for skin repair, post-laser recovery, hair and scalp care, and general rejuvenation.

However, patients should understand that exosome-based treatments are still an evolving field. Regulations, product quality, clinical evidence and treatment protocols vary by country and institution. Patients should avoid any clinic that promises guaranteed anti-aging effects, disease cures or dramatic results without medical evaluation.

Before considering exosome-related services, patients should ask:

  • What is the source of the exosome product?
  • Is it used topically, with microneedling, or by injection?
  • Is the product approved or permitted under local medical regulations?
  • What evidence supports the intended use?
  • What are the possible risks, side effects and alternatives?
  • Who is responsible for follow-up if complications occur?

A responsible provider should explain both the potential benefits and the limitations clearly.

Autologous Stem Cell Infusions: Personalized but Not for Everyone

Autologous stem cell therapy refers to the use of a patient’s own cells, usually collected from blood, bone marrow or adipose tissue, depending on the clinical protocol. In anti-aging and regenerative medicine, some patients ask about autologous stem cell infusions for vitality, immune support, tissue repair or general wellness.

This area requires strict medical judgment. Stem cell procedures should never be presented as a simple beauty treatment. They involve biological materials, collection procedures, processing standards, sterility control, eligibility assessment and follow-up monitoring.

Patients should be especially cautious if they see marketing claims suggesting that stem cell infusions can reverse aging, cure chronic disease, prevent cancer, treat neurological disease or replace standard medical care. These claims may not be supported by strong clinical evidence.

For international patients, the first step should be a physician consultation and medical record review. Doctors may need to assess blood test results, immune status, infection risk, medication history and previous diagnoses before deciding whether a regenerative medicine consultation is appropriate.

PRP Facial Rejuvenation: Using the Patient’s Own Platelets

PRP, or platelet-rich plasma, is a treatment that uses a concentrated portion of the patient’s own blood. A small amount of blood is drawn, processed in a centrifuge and then applied or injected into the treatment area. In dermatology and aesthetic medicine, PRP is commonly discussed for skin texture, fine lines, acne scars, hair loss and post-procedure recovery.

PRP facial rejuvenation is often attractive to patients who prefer a more natural approach because it uses material from their own body. It may be combined with microneedling, laser treatments or other skin rejuvenation procedures depending on the doctor’s assessment.

Common goals of PRP facial rejuvenation may include:

  • Improving skin texture
  • Supporting collagen-related skin repair
  • Reducing the appearance of fine line
  • Helping acne scar appearance
  • Supporting overall skin brightness and recovery

Still, PRP is not a magic solution. Results vary between patients, and multiple sessions may be needed. Patients with blood disorders, active infections, certain autoimmune conditions or unrealistic expectations may not be suitable candidates.

Thermage FLX: Non-Surgical Radiofrequency Skin Tightening

Thermage FLX is a non-invasive radiofrequency treatment designed to help smooth, tighten and contour the skin. It delivers radiofrequency energy into deeper skin layers to stimulate collagen remodeling. Many patients choose Thermage FLX because it does not require surgery or injections and usually involves little to no downtime.

Thermage FLX may be considered for patients with mild to moderate skin laxity on areas such as the face, eyelids, jawline, neck, arms, abdomen or thighs. Results are usually gradual because collagen remodeling takes time. Some patients may notice early tightening, while more visible improvement may develop over the following months.

Patients should understand that Thermage FLX is not a facelift and cannot produce the same result as surgery. It is better suited for patients looking for subtle, natural-looking tightening rather than dramatic structural change.

A proper consultation should include skin assessment, medical history review and discussion of contraindications. Patients with pacemakers, defibrillators or certain electrical implants may not be suitable for radiofrequency-based treatment.

HIFEM Technology: Muscle Stimulation and Body Contouring

HIFEM stands for High-Intensity Focused Electromagnetic technology. It uses electromagnetic energy to trigger strong muscle contractions that are difficult to achieve through ordinary voluntary exercise. In aesthetic and body-contouring settings, HIFEM technology is often used for abdomen, buttocks, arms, thighs or pelvic floor-related applications, depending on the device and clinical indication.

HIFEM is non-invasive and does not require surgery. It is commonly discussed for patients who want to improve muscle tone, body shape and firmness. Some studies also discuss its role in fat reduction and muscle strengthening.

However, HIFEM should not be marketed as a replacement for healthy diet, exercise or medical weight management. It is usually more suitable for body contouring and muscle stimulation than major weight loss.

Patients should inform the physician if they have metal implants, electronic devices, pregnancy, recent surgery, hernia, severe muscle disease or other medical conditions before treatment.

How GlobalMedPool Supports International Patients

For international patients, anti-aging and regenerative medicine in another country can be confusing. The main challenge is not only choosing a treatment, but choosing a safe and appropriate medical pathway.

GlobalMedPool helps patients with:

  • Initial needs assessment
  • Medical record collection and translation
  • Hospital and specialist matching
  • Appointment coordination
  • Treatment plan communication
  • Travel and local support
  • Interpretation and patient accompaniment
  • Post-treatment follow-up coordination

Our platform can help patients explore anti-aging and regenerative care options at trusted medical institutions in China, including hospitals and medical groups with strong clinical resources such as Shulan Hospital and Ningbo Medical Center Lihuili Hospital.

Who May Be a Suitable Candidate?

Anti-aging and regenerative medicine may be suitable for patients who want to:

  • Improve skin quality and facial aging signs
  • Explore non-surgical skin tightening
  • Support post-procedure recovery
  • Improve body contour and muscle tone
  • Receive a physician-led wellness assessment
  • Combine aesthetic care with broader health management

However, not every patient is suitable for every treatment. The right plan depends on age, medical history, physical condition, skin quality, treatment goals, budget and risk tolerance.

A Responsible Approach to Anti-Aging Medicine

The best anti-aging care is not about chasing every new trend. It is about choosing safe, evidence-informed and personalized options under medical supervision.

Exosome therapy and stem cell-related services require especially careful evaluation because the field is developing quickly and regulations differ across countries. PRP, Thermage FLX and HIFEM may be more familiar in aesthetic medicine, but they still require proper candidate screening and realistic expectations.

Before making a decision, patients should ask for clear information about:

  • Treatment purpose
  • Medical eligibility
  • Expected results
  • Possible side effects
  • Recovery time
  • Number of sessions
  • Product or device source
  • Doctor qualifications
  • Follow-up plan

Start Your Anti-Aging Consultation in China

If you are considering anti-aging or regenerative medicine in China, GlobalMedPool can help you take the first step. Our team will help you organize your medical information, understand available options, connect with suitable medical providers and plan your visit with international patient support.

Contact GlobalMedPool to request a personalized anti-aging and regenerative medicine consultation in China.

Medical Disclaimer: This article is for general informational purposes only and does not provide medical advice, diagnosis or treatment. Exosome therapy, stem cell procedures, PRP, Thermage FLX, HIFEM and other treatments may not be suitable for every patient. Always consult qualified medical professionals before making medical decisions.


Ready to explore anti-aging and regenerative medicine options in China?

GlobalMedPool helps international patients connect with trusted hospitals, arrange specialist consultations, translate medical records and coordinate the full medical journey in China.

Request a personalized consultation today.

 

Image

The only one in the city! This “small but powerful” team specializes in “cancer in heart, lung and vascular diseases”


Lihuili Hospital Pulmonary Arterial Hypertension Team Selected as Provincial Clinical Innovation Team

The Lihuili Hospital pulmonary arterial hypertension team has been selected as one of Zhejiang Province’s first “Small but Strong” Clinical Innovation Teams.

The list was officially announced on March 4, 2025. The Pulmonary Arterial Pressure Abnormality Team of Ningbo Medical Center Lihuili Hospital was the only team in Ningbo to receive this honor.

This recognition highlights the hospital’s long-term work in the diagnosis, treatment and management of pulmonary arterial hypertension, also known as PAH.


What Is Pulmonary Arterial Hypertension?

Pulmonary arterial hypertension is a serious disease caused by abnormally high pressure in the pulmonary arteries.

When pulmonary arterial pressure rises, the heart has to work much harder to pump blood to the lungs. Over time, this may lead to right heart failure and even life-threatening complications.

Many patients experience shortness of breath, fatigue and reduced exercise tolerance. Some patients may also develop bluish or purple lips due to low oxygen levels. For this reason, PAH patients are sometimes called “blue-lip” patients.

Although the name sounds poetic, the disease itself is severe and requires early diagnosis and long-term treatment.


A Multidisciplinary PAH Team in Ningbo

The Lihuili Hospital pulmonary arterial hypertension team is one of the earliest local teams dedicated to PAH diagnosis and treatment.

The team brings together specialists from several departments. These include respiratory and critical care medicine, cardiology, thoracic surgery, interventional radiology, rheumatology and immunology.
It also works closely with pharmacy, laboratory medicine and the medical-engineering innovation research institute.

This multidisciplinary model allows the team to provide more complete care for PAH patients. It also helps improve diagnosis, treatment planning and long-term follow-up.


Expert Leadership and Team Vision

The team is led by Dr. Wu Shibo, Chief Physician of the Department of Respiratory and Critical Care Medicine.

Dr. Wu said the team will use this opportunity to further strengthen multidisciplinary cooperation. The goal is to build a more efficient, professional and innovative clinical team.

The team also hopes to help more patients receive high-quality PAH care locally. This means patients may no longer need to travel outside the province for advanced diagnosis and treatment.


A Patient’s Journey with PAH

Five years ago, Ms. Hu, a young mother, began to feel increasingly tired after giving birth.

At first, she thought her symptoms were caused by poor postpartum recovery. However, rest did not help. Her condition continued to worsen.

She became breathless after light activity. Climbing stairs became difficult. Even simple daily tasks, such as going out to buy groceries, became a burden.

Later, her lips began to turn purple. This made her realize that her condition might be serious.

After a series of medical examinations, Ms. Hu was diagnosed with severe pulmonary arterial hypertension related to systemic lupus erythematosus and connective tissue disease.


Comprehensive Treatment and Long-Term Care

Ms. Hu later came to Lihuili Hospital for treatment.

Under the leadership of Dr. Wu Shibo, several specialists joined her treatment plan. The team included experts from cardiovascular medicine and rheumatology and immunology.

Her treatment focused on two goals. The first was to control lupus activity. The second was to keep pulmonary arterial hypertension at a low-risk level.

Doctors used corticosteroids and immunosuppressants to manage lupus. At the same time, they used targeted drugs to reduce pulmonary arterial pressure.

With this combined treatment, Ms. Hu’s condition gradually became stable.

Over the past five years, she has followed medical advice closely. She has also received regular follow-up examinations and right heart catheterization tests.

Today, Ms. Hu has returned to work. Her daily life has also returned to a normal path.


Building a Stronger Future for PAH Care

The Pulmonary Arterial Hypertension Team at Lihuili Hospital has the only pulmonary vascular sub-specialty ward in Zhejiang Province.

It is also a National Pulmonary Vascular Disease Demonstration Center and a member unit of the Pulmonary Arterial Hypertension Alliance.

In the future, the team will continue to improve PAH diagnosis and treatment. It will focus on better screening, standardized treatment pathways and patient management.

The team also plans to use artificial intelligence to improve the diagnosis rate and treatment rate of PAH patients.

These efforts may help reduce hospital admissions, lower medical costs and improve patients’ quality of life.


Raising Awareness of Pulmonary Arterial Hypertension

Pulmonary arterial hypertension is often difficult to detect in its early stages. Symptoms such as fatigue and shortness of breath may be mistaken for other health problems.

Therefore, public education is very important.

The Lihuili Hospital pulmonary arterial hypertension team will continue to promote health education and patient management. It aims to raise awareness of PAH and help more patients receive timely care.

Through clinical innovation, multidisciplinary cooperation and long-term research, the team hopes to bring new hope to patients with pulmonary arterial hypertension.


88bf2245402e4565de9937b3bb8ab4cb

AI Is Moving Into Chronic Disease Management: From Digital Reminders to Clinician-Supervised Continuous Care

Introduction

For many years, artificial intelligence in healthcare was mainly associated with medical imaging, appointment scheduling, documentation, and administrative automation. But a new wave of clinical AI is moving closer to everyday patient care, especially in chronic disease management.

One recent example is UpDoc, a clinical AI company focused on chronic disease care. According to the FDA’s 510(k) summary, UpDoc’s mobile patient interface is intended for adults with type 2 diabetes as an aid in optimizing insulin management, allowing patients to log blood glucose, meals, symptoms, and medication adherence data while receiving treatment-plan instructions.

This development highlights a broader shift: AI is no longer just a digital assistant. It is gradually becoming part of the infrastructure that supports patients between medical visits.

Why Chronic Disease Management Needs Better Support

Chronic conditions such as diabetes, hypertension, cardiovascular disease, and obesity are not managed in a single appointment. They require long-term monitoring, medication adherence, lifestyle changes, and regular follow-up.

The challenge is that most patients spend only a small amount of time with clinicians. The majority of disease management happens at home, between visits, where patients may need to interpret glucose readings, remember medication schedules, adjust habits, and decide when to contact their care team.

This gap creates an opportunity for digital health tools. If AI systems can safely collect patient-reported data, identify patterns, remind patients to follow clinician-approved plans, and escalate concerns when needed, they may help make chronic care more continuous and proactive.

The Key Shift: AI Under Physician Supervision

The most important point is not that AI is replacing doctors. The more realistic model is clinician-supervised AI.

According to reporting on UpDoc’s FDA-cleared technology, the system is designed to communicate with patients between appointments and adjust medication doses only within limits set by the patient’s clinician. Its initial focus is type 2 diabetes management, with pilot work planned in major health systems.

That distinction matters. In chronic disease care, AI should not act as an independent physician. Instead, it should operate inside a clearly defined treatment plan, with the clinician setting the boundaries and the system helping execute routine follow-up tasks.

Why Diabetes Is a Strong Use Case for Clinical AI

Diabetes management depends heavily on data. Blood glucose readings, medication use, meals, symptoms, exercise, sleep, and weight trends all influence treatment decisions.

Traditional care models often rely on occasional appointments and retrospective review. By contrast, connected devices and mobile applications can create a more continuous picture of the patient’s condition. Continuous glucose monitors, smart insulin tools, mobile apps, and electronic health records can all contribute to a richer data environment.

AI may help turn that data into useful action. For example, it may support patient reminders, identify unusual glucose patterns, prompt follow-up, summarize trends for clinicians, and help patients follow treatment instructions more consistently.

FDA Clearance Does Not Mean AI Can Act Alone

It is important to use precise language. UpDoc’s technology received FDA clearance, not FDA approval. In the medical device world, “cleared” and “approved” are not the same thing.

The FDA maintains resources on AI-enabled medical devices authorized for marketing in the United States, and the agency states that its AI-enabled medical device list is intended to improve transparency for healthcare providers, patients, and innovators.

This regulatory progress is important, but it does not remove the need for clinical governance. AI tools that influence diabetes management must be evaluated for safety, performance, patient understanding, data privacy, workflow integration, and clear responsibility when something goes wrong.

What This Means for Patients

For patients, the biggest potential benefit is support between visits. Many chronic disease complications develop gradually. If a system can detect early warning signs, encourage adherence, and help patients stay aligned with their care plan, it may reduce the “silent gaps” in chronic care.

The American Diabetes Association’s Innovation Fund announced a strategic investment in UpDoc in June 2026, describing the company’s work as clinical AI aimed at chronic disease management and prevention at scale.

For patients with diabetes, this kind of model could eventually mean more timely guidance, fewer unanswered questions, and better continuity of care.

What This Means for Doctors and Healthcare Organizations

For clinicians, AI may help reduce repetitive follow-up work while preserving medical oversight. Many healthcare systems face rising patient volumes, growing chronic disease burdens, and limited clinician time.

A supervised AI system could help collect data, organize patient updates, flag risks, and support routine plan execution. This would allow physicians and care teams to spend more time on complex cases, diagnosis, shared decision-making, and personalized treatment planning.

For hospitals and clinics, the opportunity is not simply to add another app. The real value comes when AI integrates with existing clinical workflows, electronic health records, patient communication systems, and care team protocols.

The Future: AI as Part of Chronic Care Infrastructure

The next stage of healthcare AI will likely be less about flashy standalone tools and more about integrated clinical infrastructure.

Successful systems will need to be:

  • Clinician-supervised
  • Transparent in how they operate
  • Easy for patients to understand
  • Integrated into medical records and workflows
  • Continuously monitored for safety and performance
  • Designed with clear escalation rules when patient risk increases

As AI enters more clinical settings, healthcare organizations will need to balance innovation with patient safety. The future of AI in chronic disease management should not be autonomous medicine. It should be safer, more connected, and more continuous care under professional supervision.

Conclusion

AI is beginning to reshape chronic disease management. In diabetes care, the combination of connected devices, patient-reported data, mobile apps, and clinician-supervised AI may help close the gap between appointments.

The most promising future is not one where AI replaces physicians. It is one where AI helps physicians extend care beyond the clinic, support patients in daily life, and make chronic disease management more continuous, scalable, and responsive.


References

  • FDA 510(k) summary for UpDoc K253281.
  • FDA AI-enabled medical devices page.
  • American Diabetes Association Innovation Fund announcement.
  • WSJ report on UpDoc’s FDA-cleared clinical AI.

Hi, How Can We Help You?
LOADING